Related Experiment Video
Updated: Jul 15, 2026
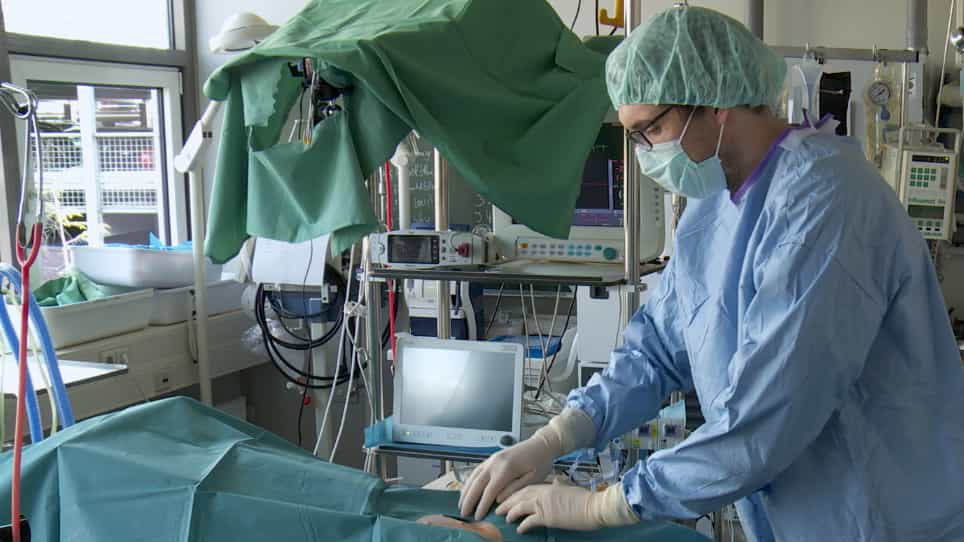
Standardized Hemorrhagic Shock Induction Guided by Cerebral Oximetry and Extended Hemodynamic Monitoring in Pigs
Published on: May 21, 2019
Is resuscitation from hemorrhagic shock limited by blood oxygen-carrying capacity or blood viscosity?
Pedro Cabrales1, Amy G Tsai, Marcos Intaglietta
1La Jolla Bioengineering Institute, La Jolla, California 92037, USA. pcabrales@ucsd.edu

Systemic and microvascular hemodynamic responses to volume restoration from hemorrhagic shock were studied in the hamster window chamber model to determine the significance of blood rheological and oxygen transport properties. Moderated hemorrhage was induced by means of arterial controlled bleeding of 50% of the blood volume. The hypovolemic shock state was maintained for 1 h before resuscitation. The animals were resuscitated by infusion of 25% of blood volume using either fresh plasma or blood and were studied for 90 min. Transfusion was performed with either oxygen-carrying fresh red blood cells (RBCs) or non-oxygen-carrying RBCs whose hemoglobin was converted to methemoglobin (MetHb). Systemic parameters, including cardiac output, vital organ blood flow distribution, microvascular hemodynamics, and capillary perfusion (functional capillary density [FCD]), were measured during the resuscitation period. Fluorescent-labeled microspheres were used to measure organ blood flow (brain, heart, kidney, liver, lung, spleen, and window chamber). The blood viscosities at the end of the 90-min period were 2.4 cP after resuscitation with plasma, and 2.9 to 3.0 cP after blood transfusion (baseline, 4.2 cP). Resuscitation with RBCs with or without oxygen-carrying capacity had greater mean arterial pressure than did the plasma resuscitation group. The FCD was substantially higher for RBC transfusions (0.56% +/- 7% of baseline) compared with plasma (46% +/- 7% of baseline), and the presence of MetHb in the fresh RBC did not change the FCD or the microvascular hemodynamics. Oxygen delivery and extraction levels were significantly lower for resuscitation with plasma and MetHb-loaded RBCs compared with oxygen-carrying RBCs. The curtailed recovery of systemic and microvascular conditions after volume restitution with plasma seems to be due to the decrease in blood viscosity. Conversely, the restoration of blood rheological properties improves resuscitation independently of the restitution of oxygen-carrying capacity.
Systemic and microvascular hemodynamic responses to volume restoration from hemorrhagic shock were studied in the hamster window chamber model to determine the significance of blood rheological and oxygen transport properties. Moderated hemorrhage was induced by means of arterial controlled bleeding of 50% of the blood volume. The hypovolemic shock state was maintained for 1 h before resuscitation. The animals were resuscitated by infusion of 25% of blood volume using either fresh plasma or blood and were studied for 90 min. Transfusion was performed with either oxygen-carrying fresh red blood cells (RBCs) or non-oxygen-carrying RBCs whose hemoglobin was converted to methemoglobin (MetHb). Systemic parameters, including cardiac output, vital organ blood flow distribution, microvascular hemodynamics, and capillary perfusion (functional capillary density [FCD]), were measured during the resuscitation period. Fluorescent-labeled microspheres were used to measure organ blood flow (brain, heart, kidney, liver, lung, spleen, and window chamber). The blood viscosities at the end of the 90-min period were 2.4 cP after resuscitation with plasma, and 2.9 to 3.0 cP after blood transfusion (baseline, 4.2 cP). Resuscitation with RBCs with or without oxygen-carrying capacity had greater mean arterial pressure than did the plasma resuscitation group. The FCD was substantially higher for RBC transfusions (0.56% +/- 7% of baseline) compared with plasma (46% +/- 7% of baseline), and the presence of MetHb in the fresh RBC did not change the FCD or the microvascular hemodynamics. Oxygen delivery and extraction levels were significantly lower for resuscitation with plasma and MetHb-loaded RBCs compared with oxygen-carrying RBCs. The curtailed recovery of systemic and microvascular conditions after volume restitution with plasma seems to be due to the decrease in blood viscosity. Conversely, the restoration of blood rheological properties improves resuscitation independently of the restitution of oxygen-carrying capacity.
Related Concept Videos
 01:27
Oxygen Transport in the Blood
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:20
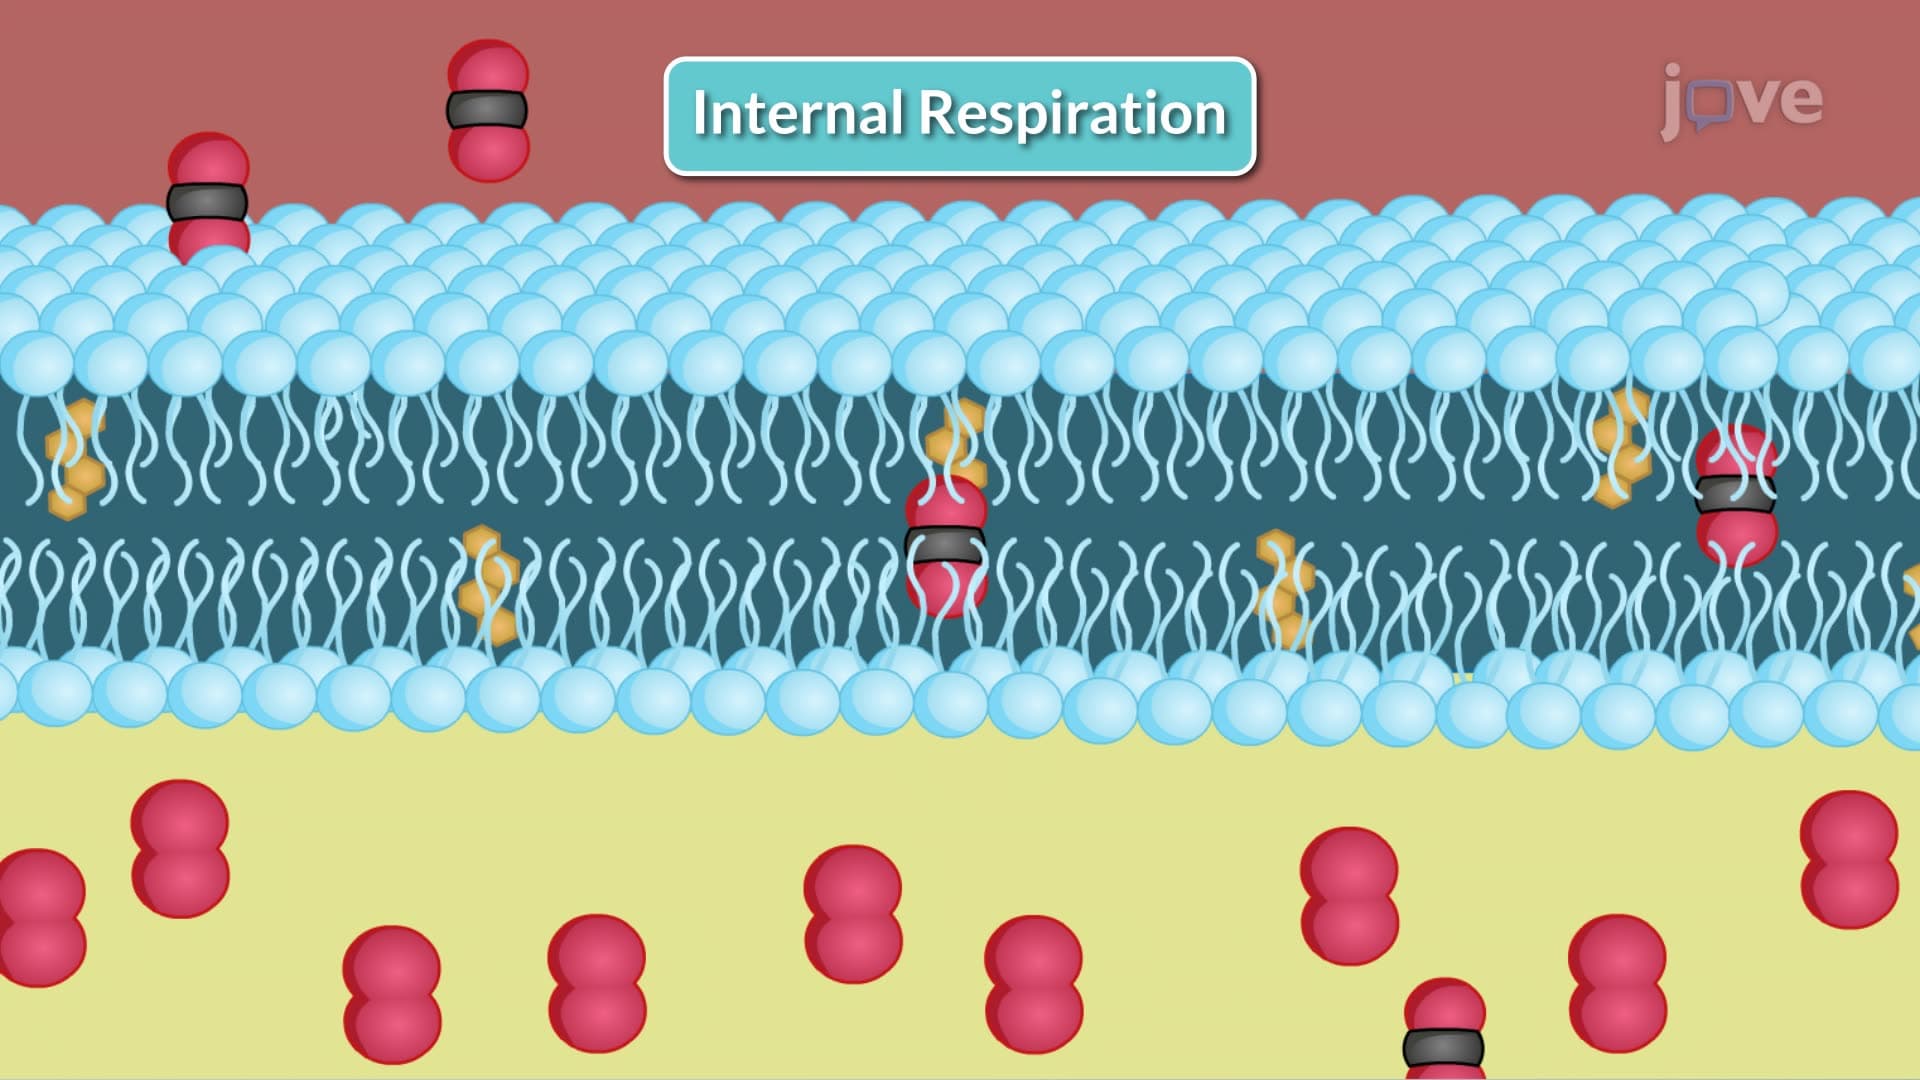
Respiration and Gaseous Exchange
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:20
Vascular Resistance
The primary determinants of vascular resistance are vessel diameter, blood viscosity, and vessel length. Among these, vessel diameter plays the most significant role due to the fourth power relationship described by...
 01:23
Hypoxia
Types of Hypoxia
There are four primary types of hypoxia, each resulting from a different cause:
1. Anemic hypoxia: This type occurs due to insufficient oxygen delivery caused by a lack of red blood cells (RBCs) or RBCs with abnormal or...