Related Experiment Video
Updated: Jul 15, 2026
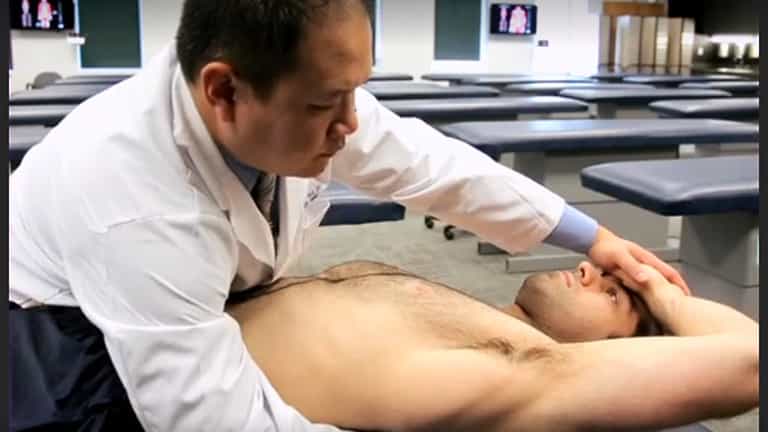
Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Utility of follow-up recommendations for patients discharged with community-acquired pneumonia
Sam G Campbell1, Daphne D Murray, David G Urquhart
1Department of Emergency Medicine, Dalhousie University, Halifax, Nova Scotia, Canada. sgcampbe@dal.ca

Introduction:
The joint Canadian Infectious Diseases Society and Canadian Thoracic Society guidelines for community-acquired pneumonia (CAP) recommend 48-72 hour telephone follow-up of patients discharged from the emergency department (ED). The guidelines provide no evidence supporting this practice, and neither the clinical utility nor the effectiveness of such recommendations has been assessed. Our objective was to assess the utility of a 48-72 hour telephone follow-up protocol for patients discharged from the ED with CAP.
Methods:
This was a retrospective chart audit covering a 2-year period (Jan. 3, 1999 to Jan. 3, 2001) after the introduction of a clinical practice guideline (CPG) that included routine 48-72 hour telephone follow-up of patients discharged from the ED with CAP. Eligible patients were identified in the ED database, rates of referral for telephone follow-up were recorded, and 30-day outcomes (death and readmission) for patients referred versus not referred were compared.
Results:
During the study period, 867 patients were identified as being eligible for the study. The mean age was 55.7 years (range 16-98 yr), and mean pneumonia severity index (PSI) was 68.9 (range 6-187). Despite the CPG, only 148 patients (17.1%) were referred for telephone follow-up. Age, demographics, comorbidity, clinical status and pneumonia severity were similar for referred and non-referred patients. Thirty-day death (2.5%) and readmission rates (3%) were strongly related to PSI score, but did not differ significantly in the 2 comparison groups.
Conclusion:
In this setting, physicians were poorly compliant with a routine telephone follow-up protocol. The likelihood of referral for follow-up did not correlate with pneumonia severity, and follow-up referral did not appear to affect patient outcome. These findings do not support recommendations for routine early follow-up mechanisms beyond those already existing in the community.
Related Concept Videos
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:30
Pneumonia III: Complications and Assessment
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...