Related Experiment Video
Updated: Jul 15, 2026
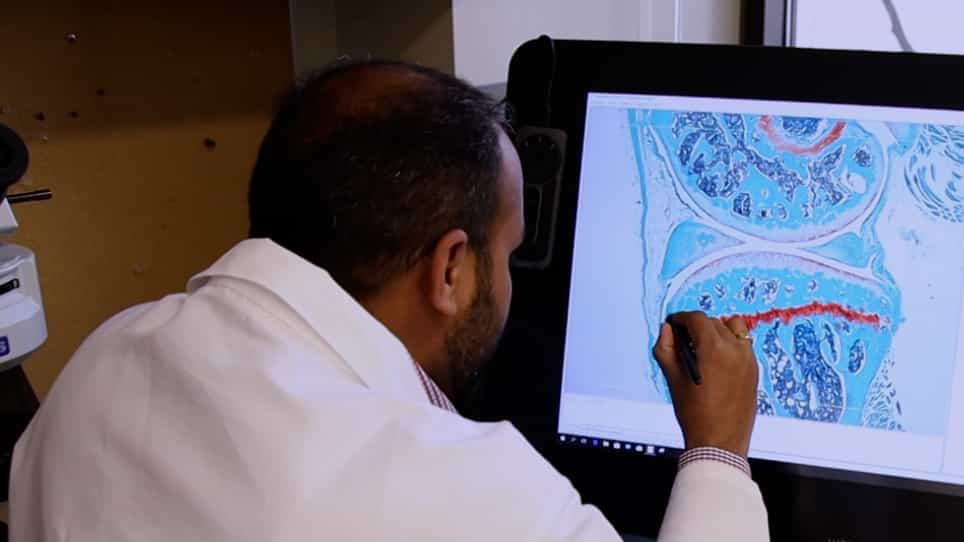

Standardized Histomorphometric Evaluation of Osteoarthritis in a Surgical Mouse Model
Published on: May 6, 2020
Osteoporosis in juvenile idiopathic arthritis--a practical approach to diagnosis and therapy
Johannes Roth1, Susanne Bechtold, Gudrun Borte
1Department of Pediatric Pneumology and Immunology, Charite University Medicine, Berlin, Germany. johannes.roth@charite.de

Insights
Juvenile idiopathic arthritis (JIA) often leads to decreased bone mass in children. Focusing on muscle mass, a key predictor, and utilizing advanced bone densitometry is crucial for managing JIA
Area of Science:
- Pediatric rheumatology
- Musculoskeletal health
- Bone metabolism
Background:
- Children with juvenile idiopathic arthritis (JIA) frequently exhibit reduced bone mass.
- Emerging research highlights muscle mass as the primary determinant of bone mass.
- The musculoskeletal system, encompassing bone and muscle, is integral to JIA pathogenesis.
Purpose of the Study:
- To review diagnostic and therapeutic strategies for musculoskeletal complications in JIA.
- To emphasize the importance of a standardized approach to managing bone and muscle health in JIA.
- To provide guidance on integrating these strategies into clinical practice.
Main Methods:
- Review of current literature on JIA, bone mass, and muscle mass.
- Analysis of advancements in pediatric bone densitometry techniques.
- Synthesis of diagnostic and therapeutic options for musculoskeletal involvement in JIA.
Main Results:
- Bone mass reduction is prevalent across JIA subgroups.
- Muscle mass is identified as the strongest predictor of bone mass.
- Advanced bone densitometry enables reliable assessment in pediatric patients.
Conclusions:
- A standardized diagnostic and therapeutic approach to the musculoskeletal system is essential for JIA patients not in rapid remission.
- Early intervention focusing on muscle and bone health is critical.
- Integrating advanced assessment tools and management strategies can improve outcomes for children with JIA.
Abstract:
In all subgroups of juvenile idiopathic arthritis, a decrease in bone mass has been described in a high percentage of children. Recently, new pathogenetic concepts have identified muscle mass as the strongest predictor of bone mass and bone is now recognized as part of the musculoskeletal system. In addition, the sophisticated use of bone densitometry in pediatrics, including new measurement techniques, has provided the tools for a reliable assessment. A standardized diagnostic approach to the musculoskeletal system, including prophylaxis and therapy, is, therefore, mandatory in all children with JIA who do not achieve rapid remission. In this review, diagnostic and therapeutic options are being described and possibilities to incorporate them into clinical practice are suggested.

Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:20
Rheumatic Heart Disease IV: Nursing Management
 01:21
Rheumatic Heart Disease III: Medical Management
 01:26
Nephrotic Syndrome II : Assessment and Medical Management