Related Experiment Video
Updated: Jul 15, 2026
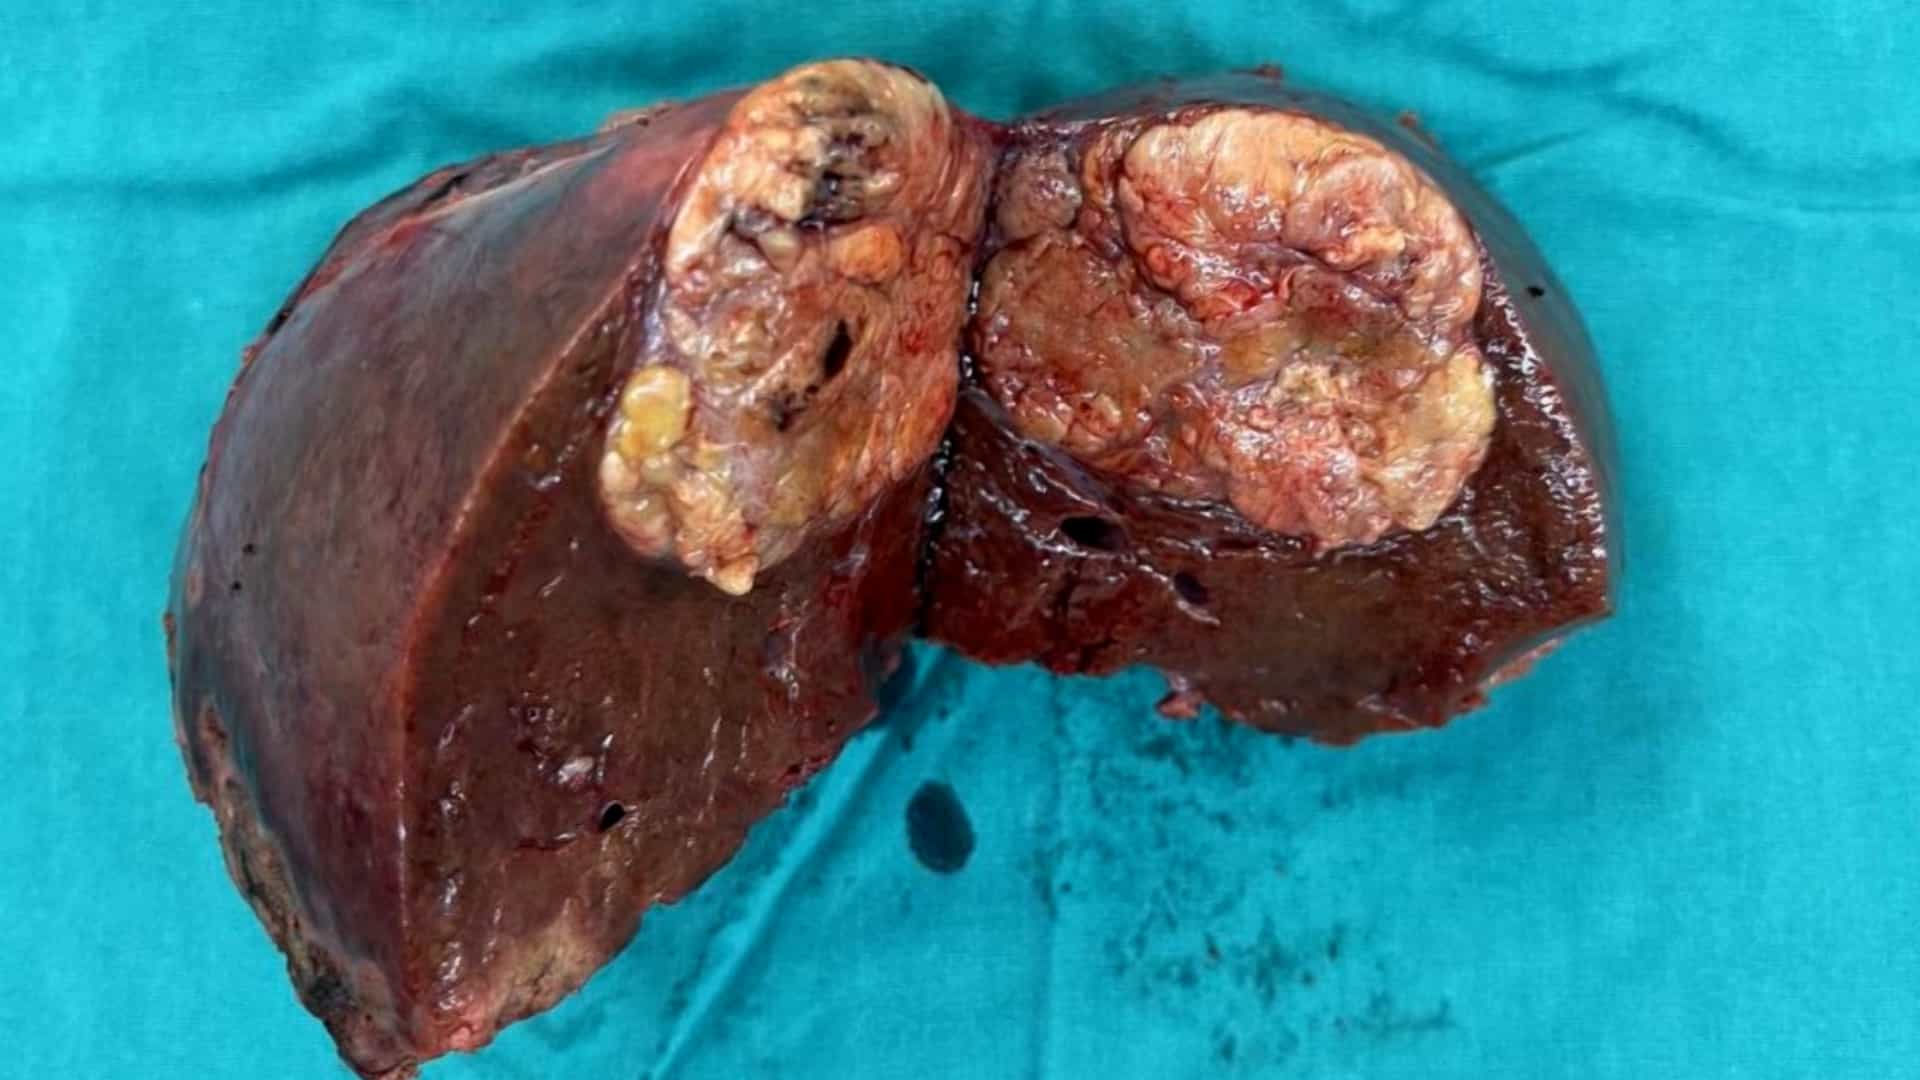

Laparoscopic Anatomical Liver Segment VII Resection with Liver Parenchymal Transection Following a Priority Approach
Published on: May 23, 2025
Acute pancreatitis after embolization of liver tumors: frequency and associated risk factors
R López-Benítez1, B A Radeleff, H M Barragán-Campos
1Department of Diagnostic Radiology, University of Heidelberg, Heidelberg, Germany. ruben_lopez@med.uni-heidelberg.de

Introduction:
Acute pancreatitis (AP) is a rare complication after liver embolization (LE) of primary and secondary liver tumors (approximately 1.7%), but it has a significant morbidity and mortality potential if associated with other complications. It usually develops early within 24 h after the LE procedure.
Study Purpose:
To calculate the frequency of AP after LE in our institution and to analyze the factors involved in this procedure (anatomical features, embolization materials, cytostatic drugs, technical factors).
Materials And Methods:
118 LE (bland embolization and transarterial chemoembolization) were performed in our institution. The study group included 59 patients who met the following inclusion criteria: one or more LE events, with complete pre- and post-interventional laboratory studies including: serum Ca(2+), creatinine, blood urea nitrogen, glucose, lactate dehydrogenase, aminotransferases, alkaline phosphatase, amylase, lipase, C-reactive protein, hematocrit and leukocytes. The diagnosis of AP was established according to the criteria of the Atlanta system of classification. For the statistical analysis the association between two response variables (e.g. AP after embolization and risk factor during the embolization, AP after embolization and volume of embolic material) was evaluated using Pearson's chi(2) test and Fisher's exact test.
Results:
The calculated frequency of AP after LE in our series was 15.2%. Amylase and lipase were elevated up to 8.7 and 20.1 times, respectively, 24 h after LE. We observed a statistically significantly lower incidence of AP in those patients who received 2 ml or less of embospheres compared with those with an embolization volume of >2 ml (Pearson's chi(2) = 4.5000, Pr = 0.034, Fisher's exact test = 0.040). Although carboplatin was administered to 7 of 9 of the patients who developed AP after the embolization procedure, there was no statistical significance (Fisher's exact test = 0.197) for carboplatin as an AP risk factor when compared with all the patients who received this drug (n = 107).
Conclusion:
Although AP after LE seems to have a multifactorial etiology, both the toxicity of the antineoplastic drugs (carboplatin-related toxicity) as well as direct ischemic mechanisms (non-target embolization, reflux mechanisms) may be the most important causes of the inflammatory pancreatic reaction after LE. We suggest that systematic measurement of serum pancreatic enzymes should be performed in cases of abdominal pain following selective LE and transarterial chemoembolization in order to confirm acute pancreatitis after embolization, which can clinically mimic a postembolization syndrome.
Related Concept Videos
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
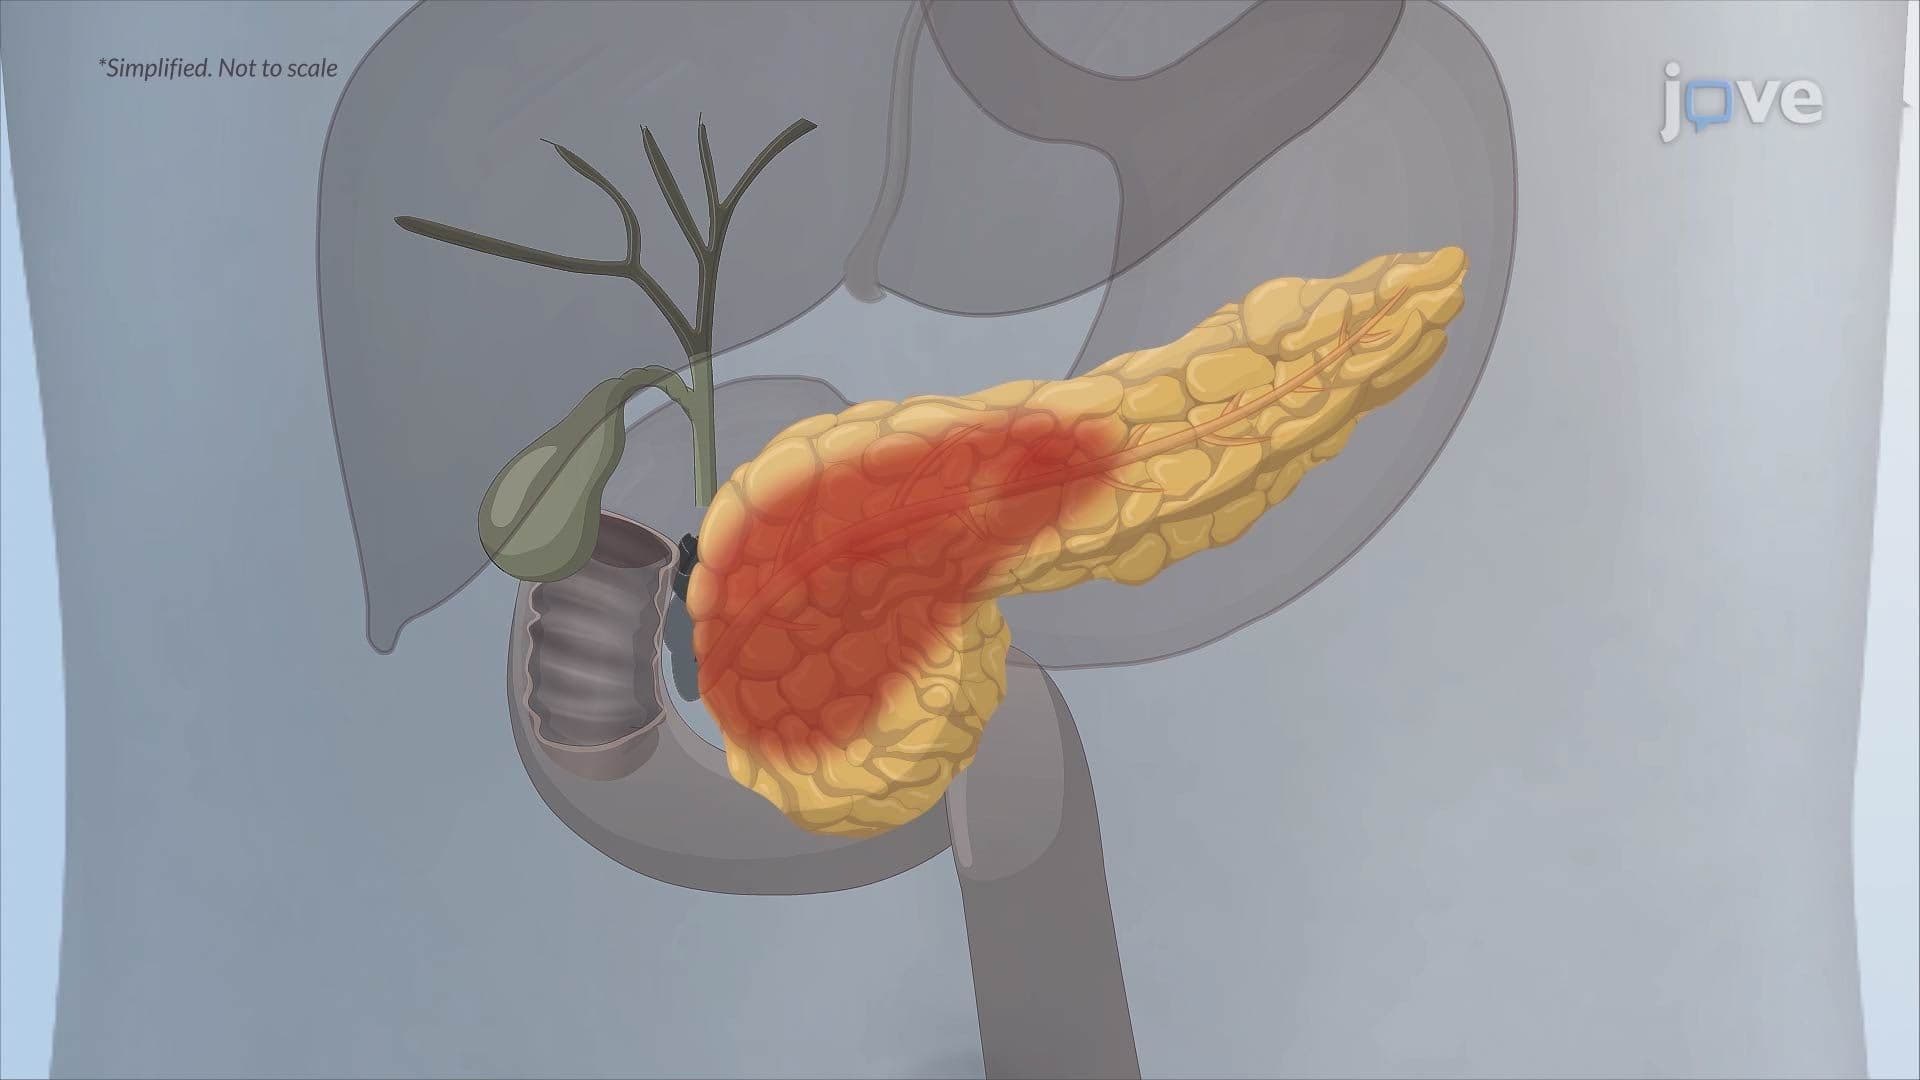
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:21
Chronic Pancreatitis II: Pathophysiology