Related Experiment Video
Updated: Jul 15, 2026
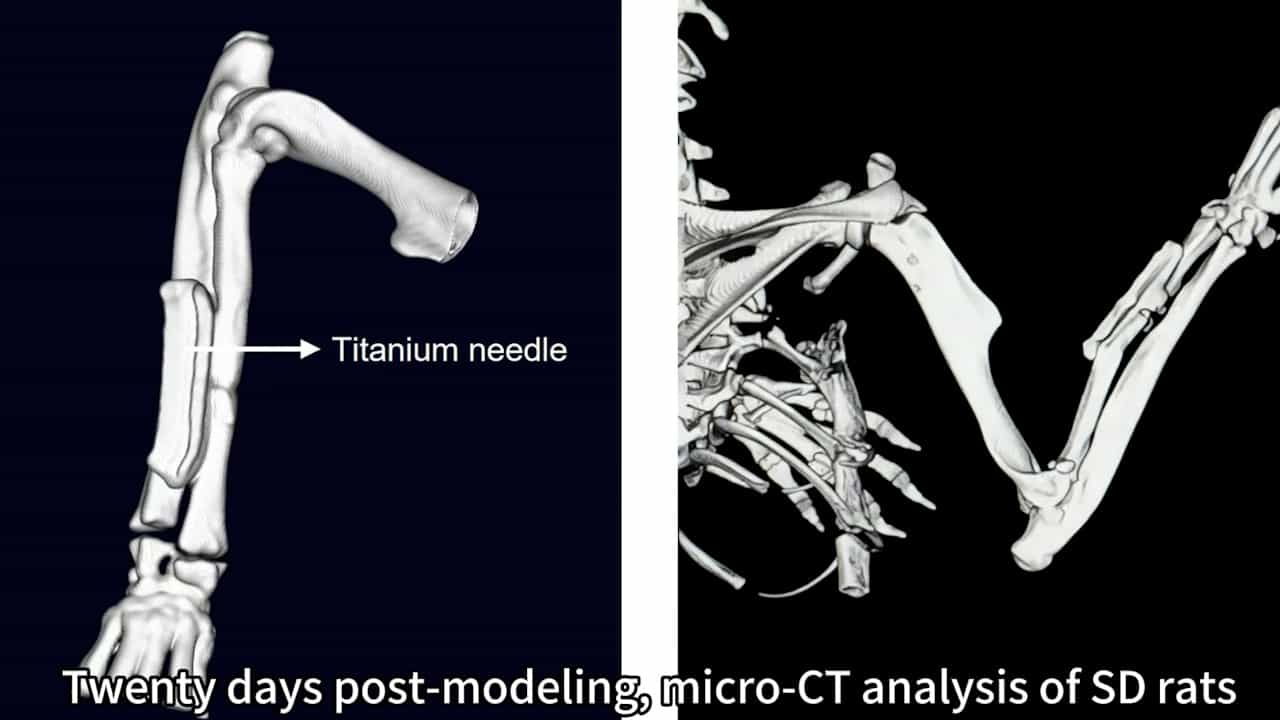

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
[Treatment of metacarpal and phalangeal fractures--a review]
Andrzej Zyluk1, Tomasz Budzyński
1Klinika Chirurgii Ogólnej i Chirurgii Reki, Pomorska Akademia Medyczna w Szczecinie.

Insights
Metacarpal and phalangeal fractures, common in young adults, show good outcomes with various treatments. Current evidence suggests no single method is superior for these hand and finger fractures.
Area of Science:
- Orthopedic surgery
- Traumatology
- Hand surgery
Context:
- Metacarpal and phalangeal fractures are common upper extremity injuries, representing 10% of all skeletal fractures.
- These fractures predominantly affect individuals aged 10–40, impacting children and young adults.
- Treatment outcomes for these injuries have been reviewed over the past two decades.
Purpose:
- To present the results of various treatment methods for isolated metacarpal and phalangeal fractures.
- To analyze the effectiveness of conservative versus operative interventions.
- To highlight the current state of evidence regarding treatment superiority.
Summary:
- Conservative management (elastic bandages, splints) is common for isolated, undisplaced fractures.
- Operative fixation (K-wires, screws, plates, external fixation) is often used for unstable or displaced fractures, particularly phalangeal fractures.
- Treatment outcomes are generally favorable across methods, with complications including nonunion, malunion, and joint stiffness.
Impact:
- Current literature lacks definitive evidence supporting one treatment modality over another for metacarpal and phalangeal fractures.
- Further research should incorporate subjective patient assessments of hand function using standardized questionnaires.
- Understanding treatment efficacy is crucial for optimizing patient recovery and hand function post-injury.
Abstract:
Isolated fractures of metacarpals and phalanges are the commonest injuries affected upper extremity, which constitute about 10% of skeletal fractures in general. They occur the most frequently in age between 10 and 40, so affect mostly children and young adults. Based no the literature from last two decades, the results of the treatment of these fractures with various methods are presented. Isolated and undisplaced fractures of the metacarpals and phalanges are usually managed conservatively using a plethora of methods of immobilization including elastic bandage, taping with neighbored finger, thermoplastic and plaster of Paris splints. Stable fractures with angular displacement require reduction or not, if dislocation is acceptable. Unstable and axially displaced fractures are usually treated operatively, however there is no enough scientific evidence that this option is more effective. Surgery for these fractures includes percutaneous fixation with K-wires introduced intramedullary or crossed, K-wires fixation with neighbored, unaffected metacarpal bone, open techniques such as lag screws and plates and external fixation. Phalangeal fractures are more frequently treated operatively, since they are commonly believed unstable what may result in malunion. The results of the treatment of fractures of metacarpals and phalanges are generally good, regardless the method which was used. The failures include nonunion, malunion which disturbs hand function or is cosmetically unacceptable, reduction of finger movement, degenerative changes in neighbored joints and algodystrophy. We stress that contemporary literature provides no evidence that either of the methods of the treatment of these fractures is superior, but rather suggests that they are equally effective. Common drawback of the quoted studies is lack of subjective assessment of the dexterity of the hand in daily and professional activity with standardized questionnaires.

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: