Related Experiment Video
Updated: Jul 15, 2026
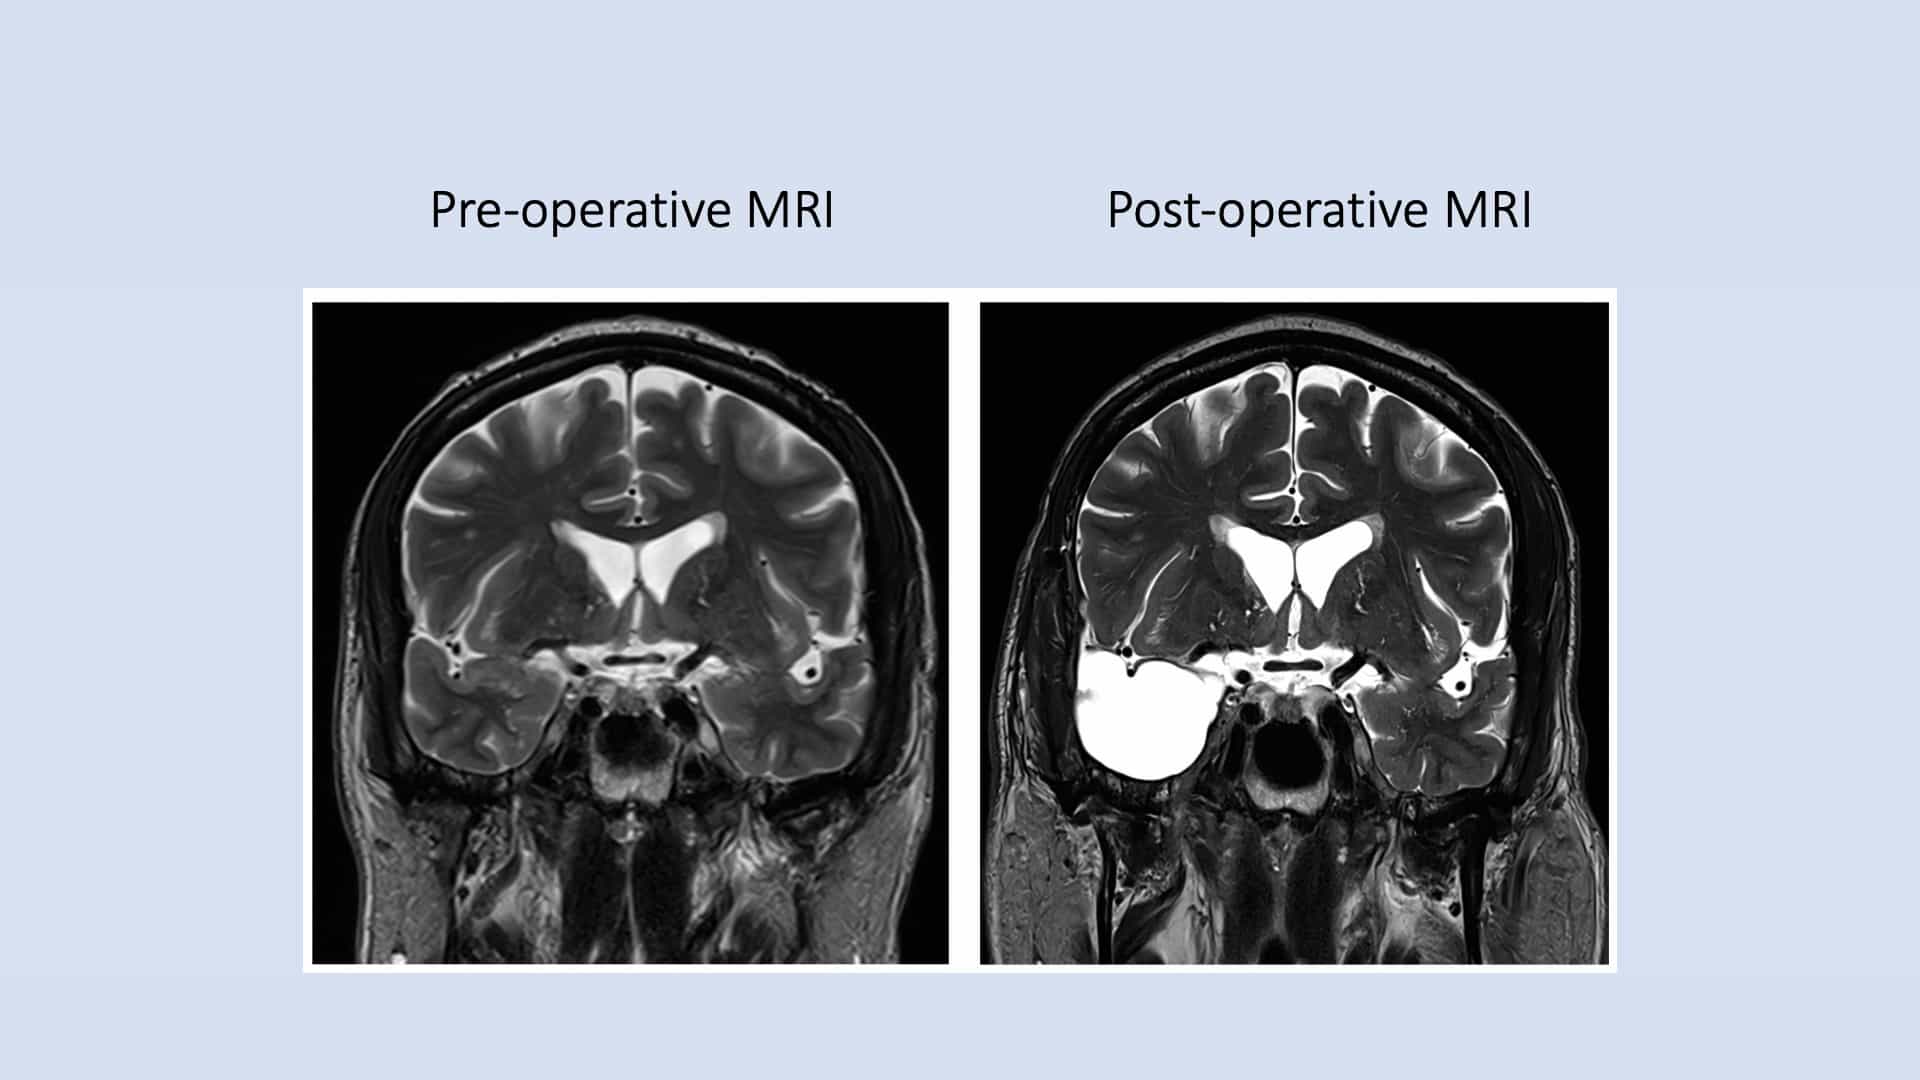

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Long-term seizure outcome in reoperation after failure of epilepsy surgery

Objective:
Treatment of patients who fail epilepsy surgery is problematic. Selected patients may be candidates for further surgery, potentially leading to a significant decrease in the frequency and severity of seizures. We present our long-term outcome series of highly investigated patients who failed resective epilepsy surgery and subsequently underwent reoperative resective procedures.
Methods:
We performed a retrospective consecutive analysis of patients who underwent reoperative procedures because of medically intractable epilepsy at our institution from 1990 to 2001. Seventy patients underwent reoperative epilepsy surgery, with 57 patients having a minimum follow-up period of 2 years. We assessed the relationship between seizure outcome and categorical variables using chi2 and Fisher's exact tests, and the relationship between outcome and continuous variables using a Wilcoxon rank-sum test. Statistical significance was set at a P value of 0.05.
Results:
Of the 57 patients (29 male and 28 female patients), the age of seizure onset ranged from 3 months to 39 years (mean, 10.7 +/- 10.3 yr; median, 7 yr). The mean age at reoperation was 24.7 +/- 12 years (range, 4-50 yr). The interval between first and second resection was 7 days to 16 years. The follow-up period ranged from 24 to 228 months (mean, 128 mo; mode, 132 mo). Seizure outcome was classified according to Engel's classification. Fifty-two percent of the patients had a favorable outcome (38.6% were Class I and 14.0% were Class II). Patients with tumors as their initial pathology had better outcome compared with patients with focal cortical dysplasia and mesial temporal sclerosis (P < 0.05).
Conclusion:
Reoperation should be considered in selected patients failing epilepsy resective surgery because approximately 50% of patients may have benefit. Patients with cortical dysplasia and mesial temporal sclerosis are less likely to improve after reoperation.
Insights
Reoperative epilepsy surgery can significantly reduce seizures in about half of patients who did not benefit from initial epilepsy surgery. However, outcomes vary by initial pathology, with tumors faring better than cortical dysplasia or mesial temporal sclerosis.
Area of Science:
- Neurosurgery
- Epileptology
- Clinical Outcomes Research
Background:
- Epilepsy surgery failure presents significant challenges for patient management.
- Reoperative surgery offers a potential solution for selected patients with intractable epilepsy.
Purpose of the Study:
- To evaluate the long-term outcomes of reoperative resective epilepsy surgery in patients who failed prior epilepsy surgery.
- To identify factors influencing seizure control after reoperation.
Main Methods:
- Retrospective analysis of 57 patients undergoing reoperative epilepsy surgery between 1990 and 2001.
- Statistical analysis using chi-squared, Fisher's exact, and Wilcoxon rank-sum tests.
- Seizure outcomes classified using Engel's scale with a minimum 2-year follow-up.
Main Results:
- 52% of patients achieved favorable seizure outcomes (Engel Class I or II).
- Patients with tumors as the initial pathology showed significantly better outcomes (P < 0.05).
- Mean follow-up was 128 months, with reoperation age averaging 24.7 years.
Conclusions:
- Reoperation is a viable option for approximately half of patients with medically intractable epilepsy after initial surgery failure.
- Outcomes are less favorable for patients with underlying focal cortical dysplasia or mesial temporal sclerosis.
- Careful patient selection is crucial for optimizing results in reoperative epilepsy surgery.
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:20
Seizures l: Introduction
 01:22
Epilepsy ll: Types