Related Experiment Videos
Usefulness of the comprehensive geriatric assessment in older patients with upper gastrointestinal bleeding: a
Alberto Pilotto1, Luigi Ferrucci, Carlo Scarcelli
1Geriatric Unit and Gerontology & Geriatrics Research Laboratories, IRCCS Casa Sollievo della Sofferenza, San Giovanni Rotondo, Italy. alberto.pilotto@libero.it

Background:
The potential usefulness of standardized comprehensive geriatric assessment (CGA) in evaluating treatment and follow-up of older patients with upper gastrointestinal bleeding is unknown.
Aim:
To evaluate the usefulness of the CGA as a 2-year mortality multidimensional prognostic index (MPI) in older patients hospitalized for upper gastrointestinal bleeding.
Materials And Methods:
Patients aged > or =65 years consecutively hospitalized for acute upper gastrointestinal bleeding were included. Diagnosis of bleeding was based on clinical and endoscopic features. All patients underwent a CGA that included six standardized scales, i.e., Activities of Daily Living (ADL), Instrumental Activities of Daily Living (IADL), Short Portable Mental Status Questionnaire (SPMSQ), Mini Nutritional Assessment (MNA), Exton-Smith Score (ESS) and Comorbity Index Rating Scale (CIRS), as well as information on medication history and cohabitation, for a total of 63 items. A MPI was calculated from the integrated total scores and expressed as MPI 1 = low risk, MPI 2 = moderate risk, and MPI 3 = severe risk. The predictive value of the MPI for mortality over a 24-month follow-up was calculated.
Results:
36 elderly patients (M 16/F 20, mean age 82.8 +/- 7.9 years, range 70-101 years) were included in the study. A significant difference in mean age was observed between males and females (M 80.1 +/- 4.8 vs. F 84.9 +/- 9.3 years; p < 0.05). The causes of upper gastrointestinal bleeding were duodenal ulcer in 38.8%, gastric ulcer in 22.2%, and erosive gastritis in 16.6% of the patients, while 16.6% had gastrointestinal bleeding from unknown origin. The overall 2-year mortality rate was 30.5%. 18 patients (50%) were classified as having a low-risk MPI (mean value 0.18 +/- 0.09), 12 (33.3%) as having a moderate-risk MPI (mean value 0.48 +/- 0.08) and 6 (16.6%) as having a severe-risk MPI (mean value 0.83 +/- 0.06). Higher MPI grades were significantly associated with higher mortality (grade 1 = 12.5%, grade 2 = 41.6%, grade 3 = 83.3%; p = 0.001). Adjusting for age and sex, the prognostic efficacy of MPI for mortality was confirmed and highly significant (odds ratio 10.47, 95% CI 2.04-53.6).
Conclusion:
CGA is a useful tool for calculating a MPI that significantly predicts the risk of 2-year mortality in older patients with upper gastrointestinal bleeding.
Related Concept Videos
 01:17
Assessment of the Gastrointestinal System I: Subjective Data
Health History
The initial step in assessing the GI system is obtaining a comprehensive health history. This includes inquiring about the patient's history or presence of problems related to...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
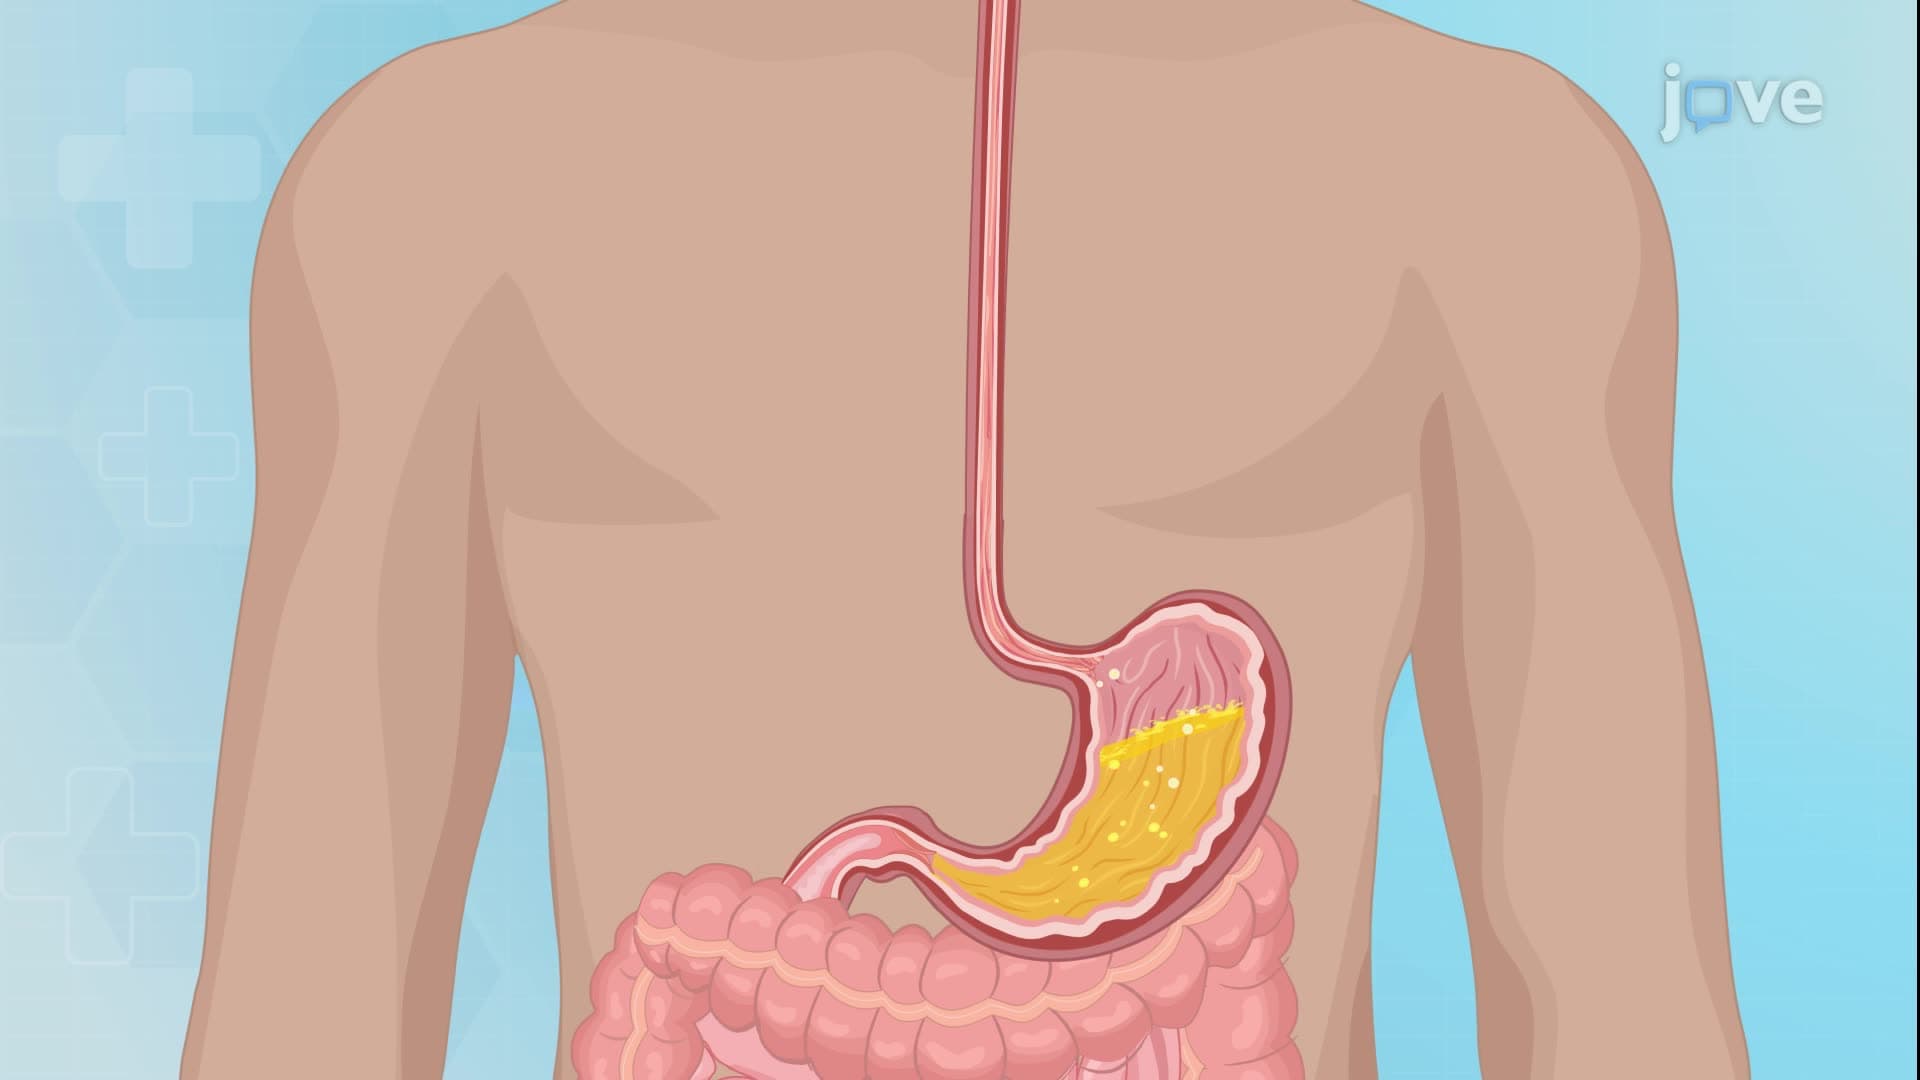 01:24
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...