Related Experiment Videos
Exposure to amlodipine in the first trimester of pregnancy and during breastfeeding
Hyun Kyong Ahn1, Alejandro A Nava-Ocampo, Jung Yeol Han
1The Korean Motherisk Program, Cheil Hospital & Women's Health-care Center, Kwandong University School of Medicine, Seoul, Korea.

Objective:
To assess the fetal outcome of three hypertensive women exposed to amlodipine. 5 mg/day, in the first trimester of pregnancy. CASE 1: The patient was treated with amlodipine until 7 weeks of gestation. She was also exposed to levosulpiride, aluminum hydroxide gel, magnesium carbonate, and Ginkgo biloba. At 38(+3) weeks of pregnancy, she delivered a 3750 g healthy female baby, and restarted taking amlodipine, 5 mg/day, while exclusively breastfeeding her daughter. At three months of age, the infant was healthy. CASE 2: The patient was treated with amlodipine from 2(+2) to 3(+4) weeks of pregnancy. Her treatment was modified to atenolol until the week 6(+4 weeks), when she declined any antihypertensive treatment. At 39(+4) weeks of pregnancy, the patient delivered a 2600 g baby. At 20 months old, the baby presented with intellectual delay and weakness in the left arm and hand grasp. These neurological alterations were not attributed to her exposure to amlodipine early in utero. CASE 3: The patient was treated with amlodipine from 7(+6) to 12 weeks of pregnancy. She was also taking sucralfate and lorazepam. At 12 weeks of amenorrhea, ultrasound revealed a 15.3 mm, single fetal pole in the gestational sac without cardiac activity. She underwent dilatation and evacuation of a dead embryo.
Conclusion:
As reported with other calcium-channel blockers, amlodipine does not appear to be teratogenic and it appears to be compatible with breastfeeding.
Related Concept Videos
 01:24
Drug Toxicity: Risk factors
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
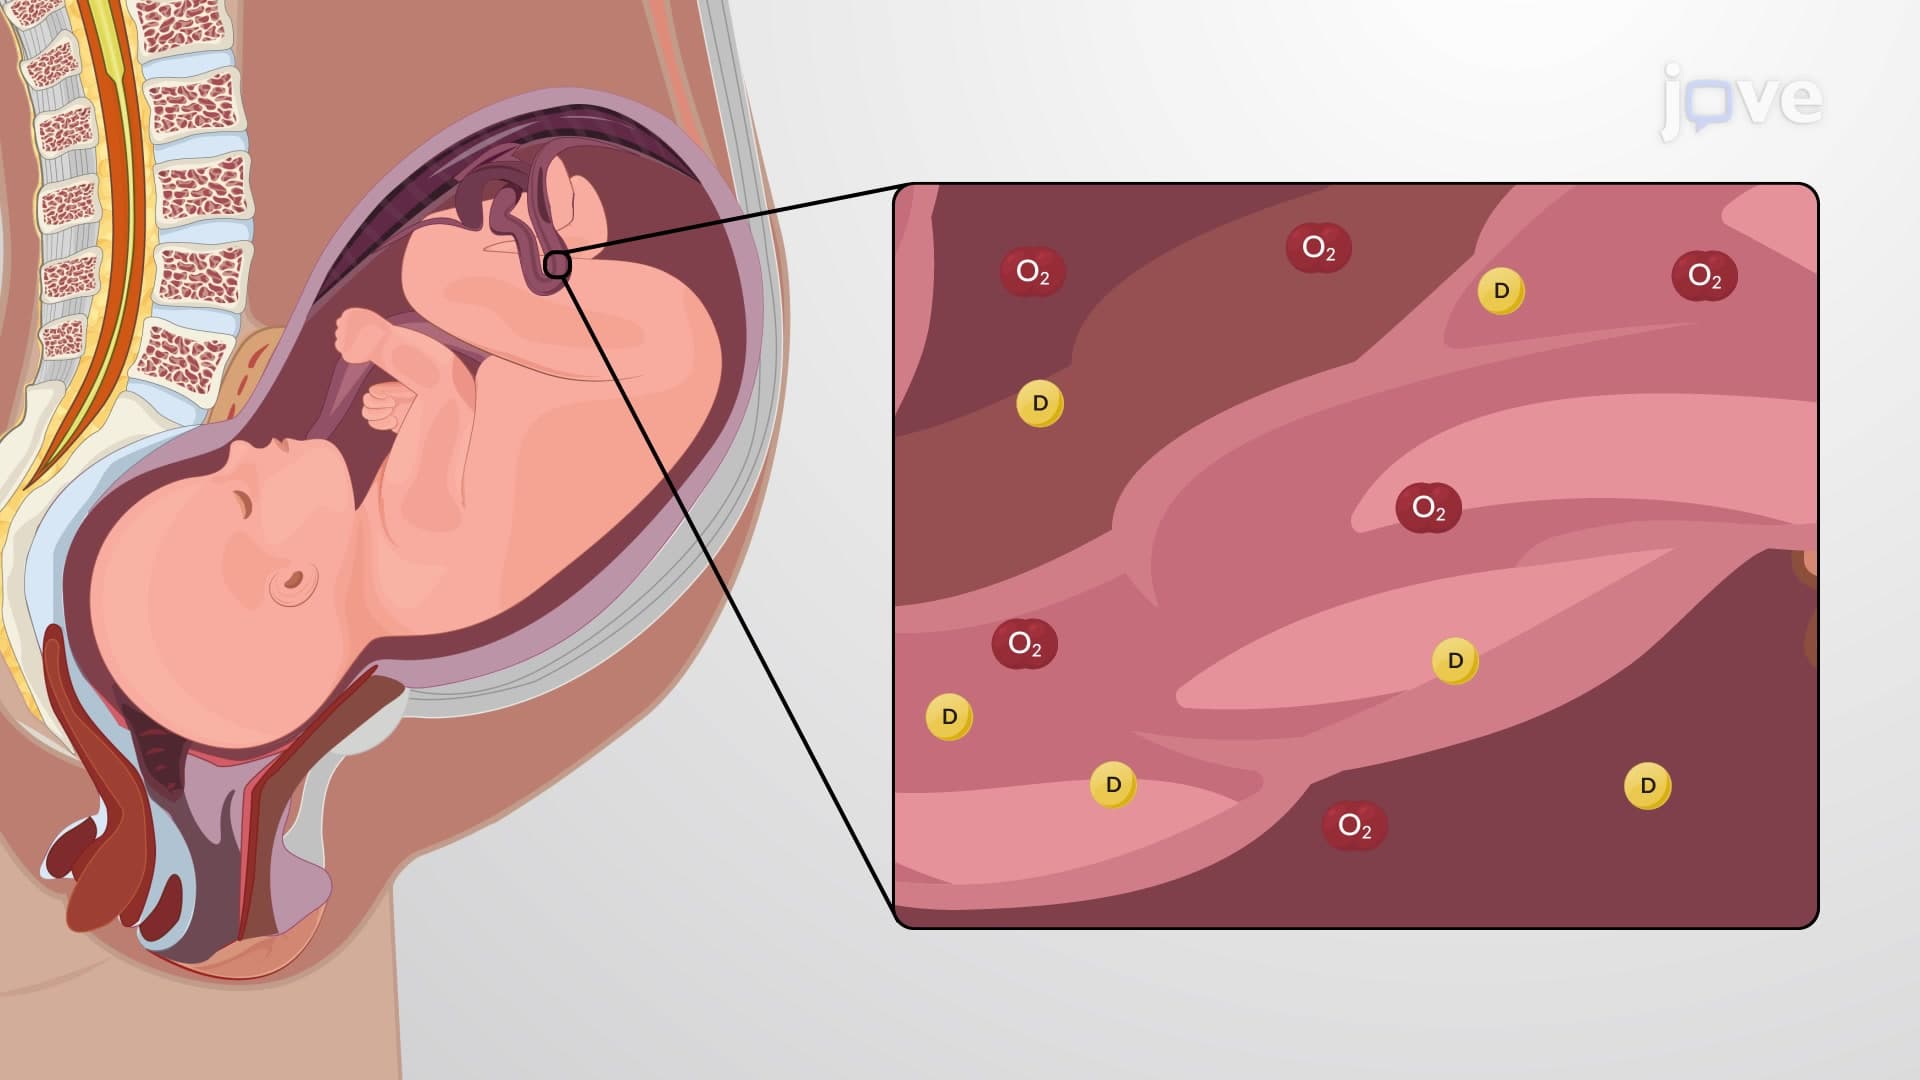 01:21
Factors Affecting Drug Response: Overview
 01:07
Teratogenicity
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion