Related Experiment Video
Updated: Jul 15, 2026

Effect of Hyaluronic Acid 35 kDa on an In Vitro Model of Preterm Small Intestinal Injury and Healing Using Enteroid-Derived Monolayers
Published on: July 28, 2022
Food mineral composition and acid-base balance in preterm infants
Hermann Kalhoff1, Friedrich Manz, Peter Kiwull
1Paediatric Clinic, 44137 Dortmund, Germany. hermann.kalhoff@klinikumdo.de

Insights
Preterm infants
Area of Science:
- Neonatal physiology
- Pediatric nutrition
- Renal function
Background:
- Preterm infants have immature renal capacity for acid excretion, increasing risk of metabolic acidosis.
- This can lead to impaired growth and bone mineralization.
- Dietary factors significantly influence acid-base balance in this vulnerable population.
Purpose of the Study:
- To investigate how diet composition affects renal regulation and acid-base balance in preterm infants.
- To analyze acid-base data from blood and urine under various feeding regimens.
- To understand the impact of mineral and protein content on infant metabolism.
Main Methods:
- Collected data from 82 preterm infants on different diets: mother's milk (native or fortified) and standard or modified preterm formulas.
- Measured food intake and determined acid-base parameters in blood and timed urine samples.
- Analyzed the relationship between dietary composition and renal acid-base regulation.
Main Results:
- Dietary mineral differences created significant variations in daily alkali intake.
- Renal base excretion showed a strong, significant correlation with individual dietary alkali intake (P < 0.0001).
- Blood acid-base parameters (base excess, PCO2) were not significantly affected by diet variations.
Conclusions:
- Renal mechanisms effectively compensate for dietary acid-base load differences in preterm infants.
- Urinary acid-base analysis is a more sensitive indicator of nutritional challenges than blood analysis.
- Reducing the acid load in standard preterm formulas is recommended due to infants' limited renal acid excretion capacity.
Background:
Due to a transient age-related low renal capacity for net acid excretion, preterm infants fed formula are at a considerable risk of spontaneously developing incipient late metabolic acidosis, clinically characterized by e.g., disturbed bone mineralization and impaired growth.
Aim Of The Study:
From acid-base data in blood and urine under different diets of modified human milk or preterm formulas is attempted to explore the impact of food mineral (and protein) composition on renal regulation and systemic acid-base balance in preterm infants.
Patients And Methods:
Data were collected from 48 infants fed their own mother's milk (28 native human milk, 20 enriched with fortifier) and 34 patients on formula (23 on a standard batch, 11 on a modified batch with reduced acid load). Intake of food was measured and acid-base data were determined in blood and timed-urine (8-12 h) samples.
Results:
Differences in mineral composition of the diets led to considerable differences of daily "alkali-intake", without significant effects on non-respiratory (base excess, BE) and respiratory (PCO(2)) acid-base data in the blood. In contrast, a highly significant proportionality between individual dietary alkali intake and daily renal base (Na(+) + K(+)-Cl(-)) excretion was observed (y = 0.32x-0.70, n = 80, r = 0.77, P < 0.0001), irrespective of the type of the diet.
Conclusion:
Renal base saving mechanisms are normally effective in preterm infants to compensate for differences in dietary acid-base load. Generally, nutritional acid-base challenges can be judged much earlier and more safely by urinary than by blood acid-base analysis. Taking into account the age specific low capacity for renal NAE, the relatively high nutritional acid load of preterm standard formula should be reduced.

Related Concept Videos
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 01:29
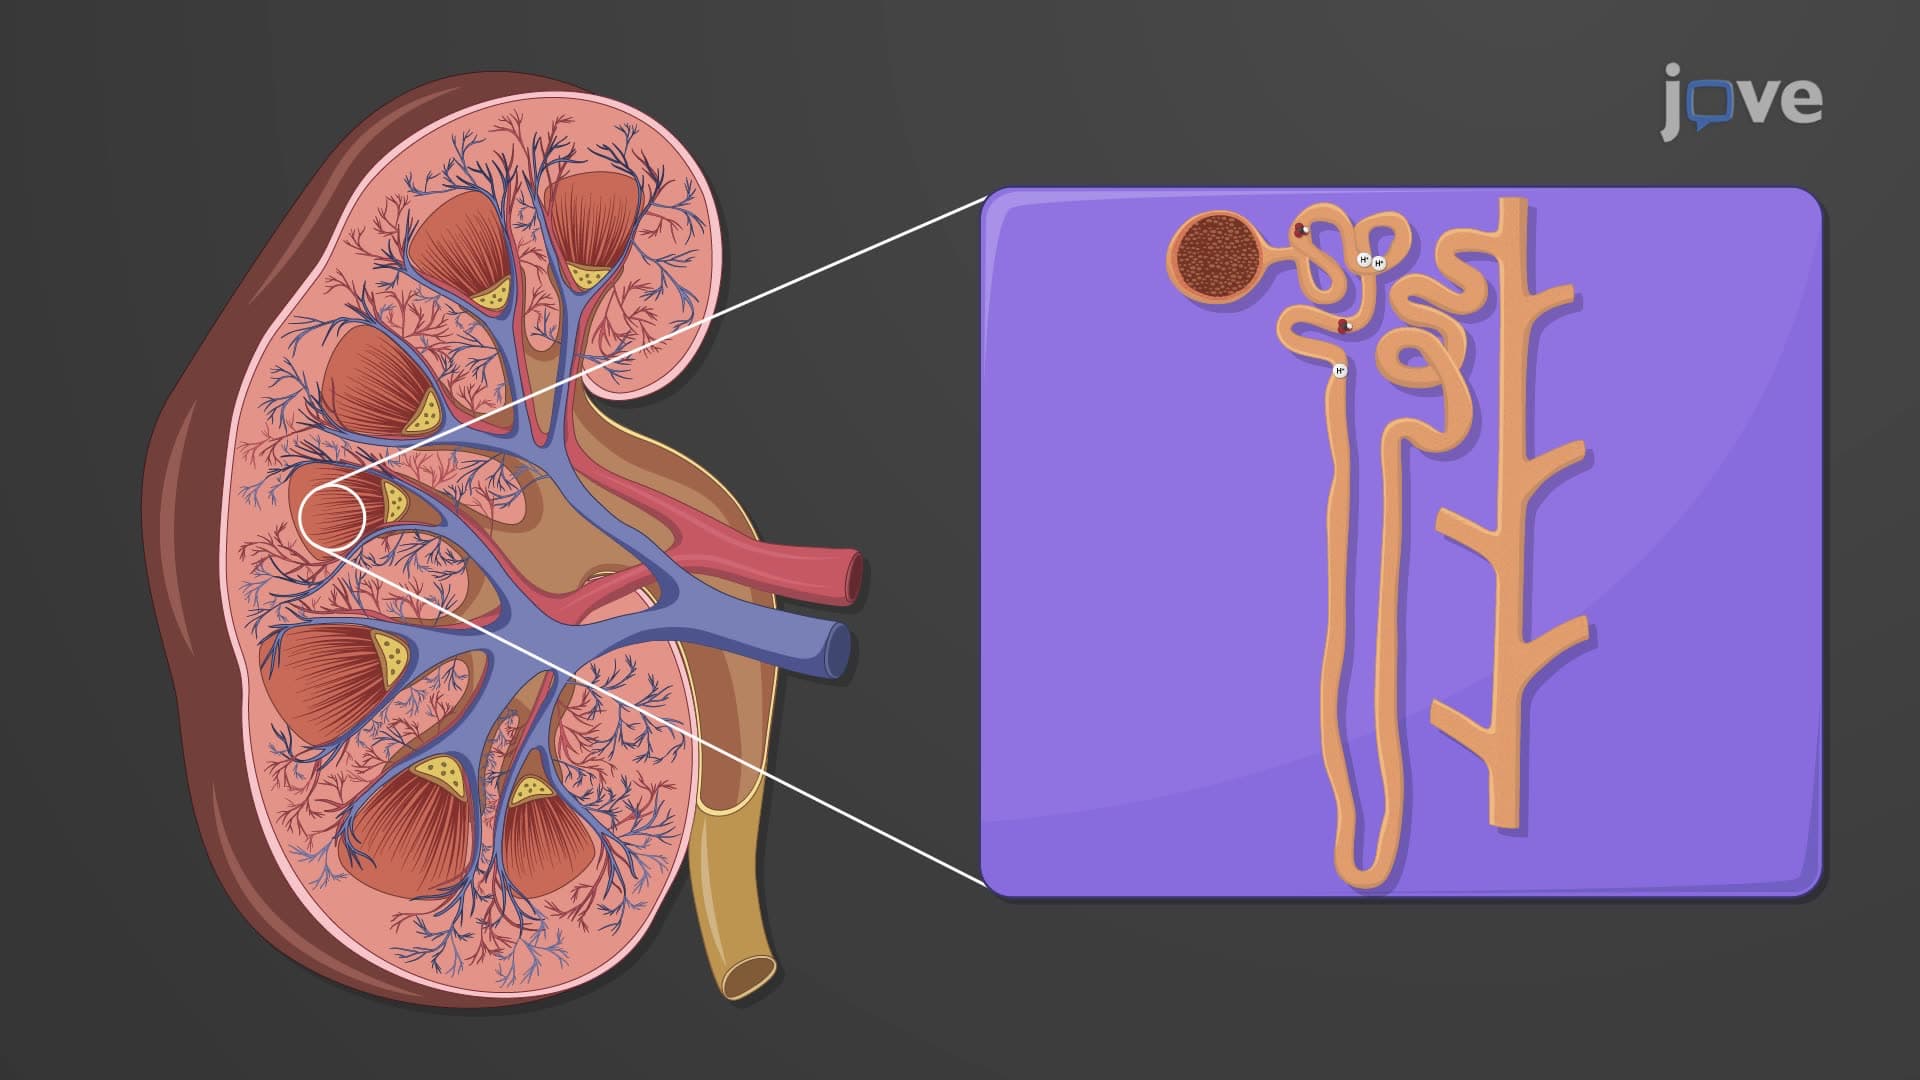
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are produced, leading to a...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:30
Development of Human Microbiota