Related Experiment Video
Updated: Jul 15, 2026
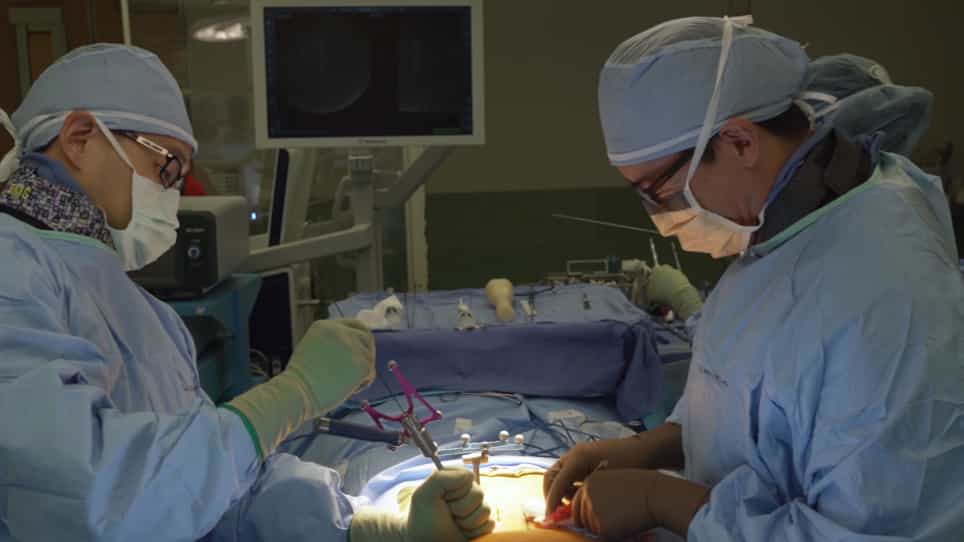

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Comparison of fluoroscopic and imageless registration in surgical navigation of the acetabular component
James B Stiehl1, David A Heck, Branislav Jaramaz
1Department of Orthopaedic Surgery, Medical College of Wisconsin, Columbia-St Mary's Hospital, Milwaukee, Wisconsin, USA. jbstiehl@aol.com

Objective:
This study compared the repeatability and reproducibility of acetabular component positioning using imageless and fluoroscopic-referenced navigation methods.
Methods:
A single cadaveric pelvis had a modular acetabular component securely fixed. Cup position was evaluated using imageless and fluoroscopic registration techniques. These were compared to measurements of a coordinate measuring machine (CMM) and a validated CT scan protocol.
Results:
The CMM-determined anatomical acetabular inclination measurement was 46.02 degrees (SD = 1.07), while the CMM-determined anatomical anteversion (pubic symphysis) was 15.79 degrees (SD = 0.41). Computed tomography revealed inclination of 42.2 degrees (SD = 0.65); anteversion with pubic tubercle referencing of 12.1 degrees (SD = 0.14); and anteversion with pubic symphysis referencing of 14.3 degrees (SD = 0.89). Evaluation of repeatability (one surgeon; n = 8) with the imageless system (pubic tubercle) revealed inclination of 41.8 degrees (SD = 0.46) and anteversion of 11.2 degrees (SD = 0.8). For the fluoroscopic system (pubic symphysis), inclination was 42.8 degrees (SD = 1.6) and anteversion was 17.6 degrees (SD = 3.1). Evaluation of reproducibility (three surgeons; n = 24) with the imageless system revealed inclination of 41.8 degrees (SD = 0.82) and anteversion of 15.2 degrees (SD = 1.06). For the fluoroscopic system, inclination was 48.5 degrees (SD = 0.9) and anteversion was 17.8 degrees (SD = 2.5). Imageless referencing of cup inclination and anteversion were found to be process capable using the Six Sigma Cp and Cpk capability indices. Fluoroscopic referencing was process capable for cup inclination but not for cup anteversion (Cp - 1.1; Cpk - 1.0). An F-test revealed significantly greater variance with fluoroscopic referenced anteversion (p < 0.002).
Conclusions:
Imageless referencing was process capable for computer navigation of cup placement in the ex-vivo setting. Fluoroscopic referencing for pelvic landmarks is problematic as locating points from radiographic images is difficult, especially for cup anteversion.
More Related Videos
 06:59
Improved Registration of 3D CT Angiography with X-ray Fluoroscopy for Image Fusion During Transcatheter Aortic Valve Implantation
Published on: June 3, 2018
 07:43
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021