Related Experiment Video
Updated: Jul 15, 2026

Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Secondary hyperparathyroidism due to hypovitaminosis D affects bone mineral density response to alendronate in
Antonella Barone1, Andrea Giusti, Giulio Pioli
1Department of Gerontology and Musculoskeletal Sciences, Galliera Hospital, Genoa, Italy. antonella.barone@galliera.it

Objectives:
To determine whether secondary hyperparathyroidism (HPTH) due to hypovitaminosis D affects bone mineral density (BMD) response to alendronate (ALN) in elderly women with osteoporosis.
Design:
Randomized, controlled trial with 1-year follow-up.
Setting:
Two osteoporosis centers in northern Italy.
Participants:
Community-dwelling women aged 60 and older with a BMD T-score below -2.5 and secondary HPTH with vitamin D insufficiency.
Intervention:
One hundred twenty subjects were randomly assigned to receive ALN 70 mg once a week alone or ALN 70 mg once a week plus calcitriol (1,25D3) 0.5 microg daily.
Measurements:
BMD measured using dual-energy x-ray absorptiometry at the lumbar spine (L1-L4), femoral neck, and total hip and serum levels of intact PTH at baseline and 12 months.
Results:
After 1 year, BMD of the lumbar spine, femoral neck, and total hip significantly increased from baseline in both groups (P<.001). Patients allocated to ALN plus 1,25D3 demonstrated a significantly higher increase in lumbar spine BMD than those receiving ALN alone (mean percentage+/-standard deviation 6.8+/-4.6 vs 3.7+/-3.2, P<.001). Serum levels of PTH did not change significantly at 1 year in the ALN group (mean percentage, -3.7+/-27.1, P=.13) but decreased significantly in the ALN plus 1,25D3 group (-32.1+/-22.1, P<.001). At 12 months, subjects with normalized PTH independent of therapy allocation had a greater increase in lumbar spine BMD than those with persistent HPTH (6.5+/-4.6% vs 3.7+/-3.4%, P<.001). Lumbar spine BMD changes showed a significant negative correlation with PTH at 1 year (correlation coefficient (rho) =-0.399, P<.001) and a positive correlation with PTH changes (i.e., baseline value - 1 year value; rho=0.295, P=.005).
Conclusion:
Persistence of secondary HPTH reduces BMD response to ALN in older women with osteoporosis.
Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:21
Skeleton and Calcium Homeostasis
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:40
Bone Remodeling
 00:59
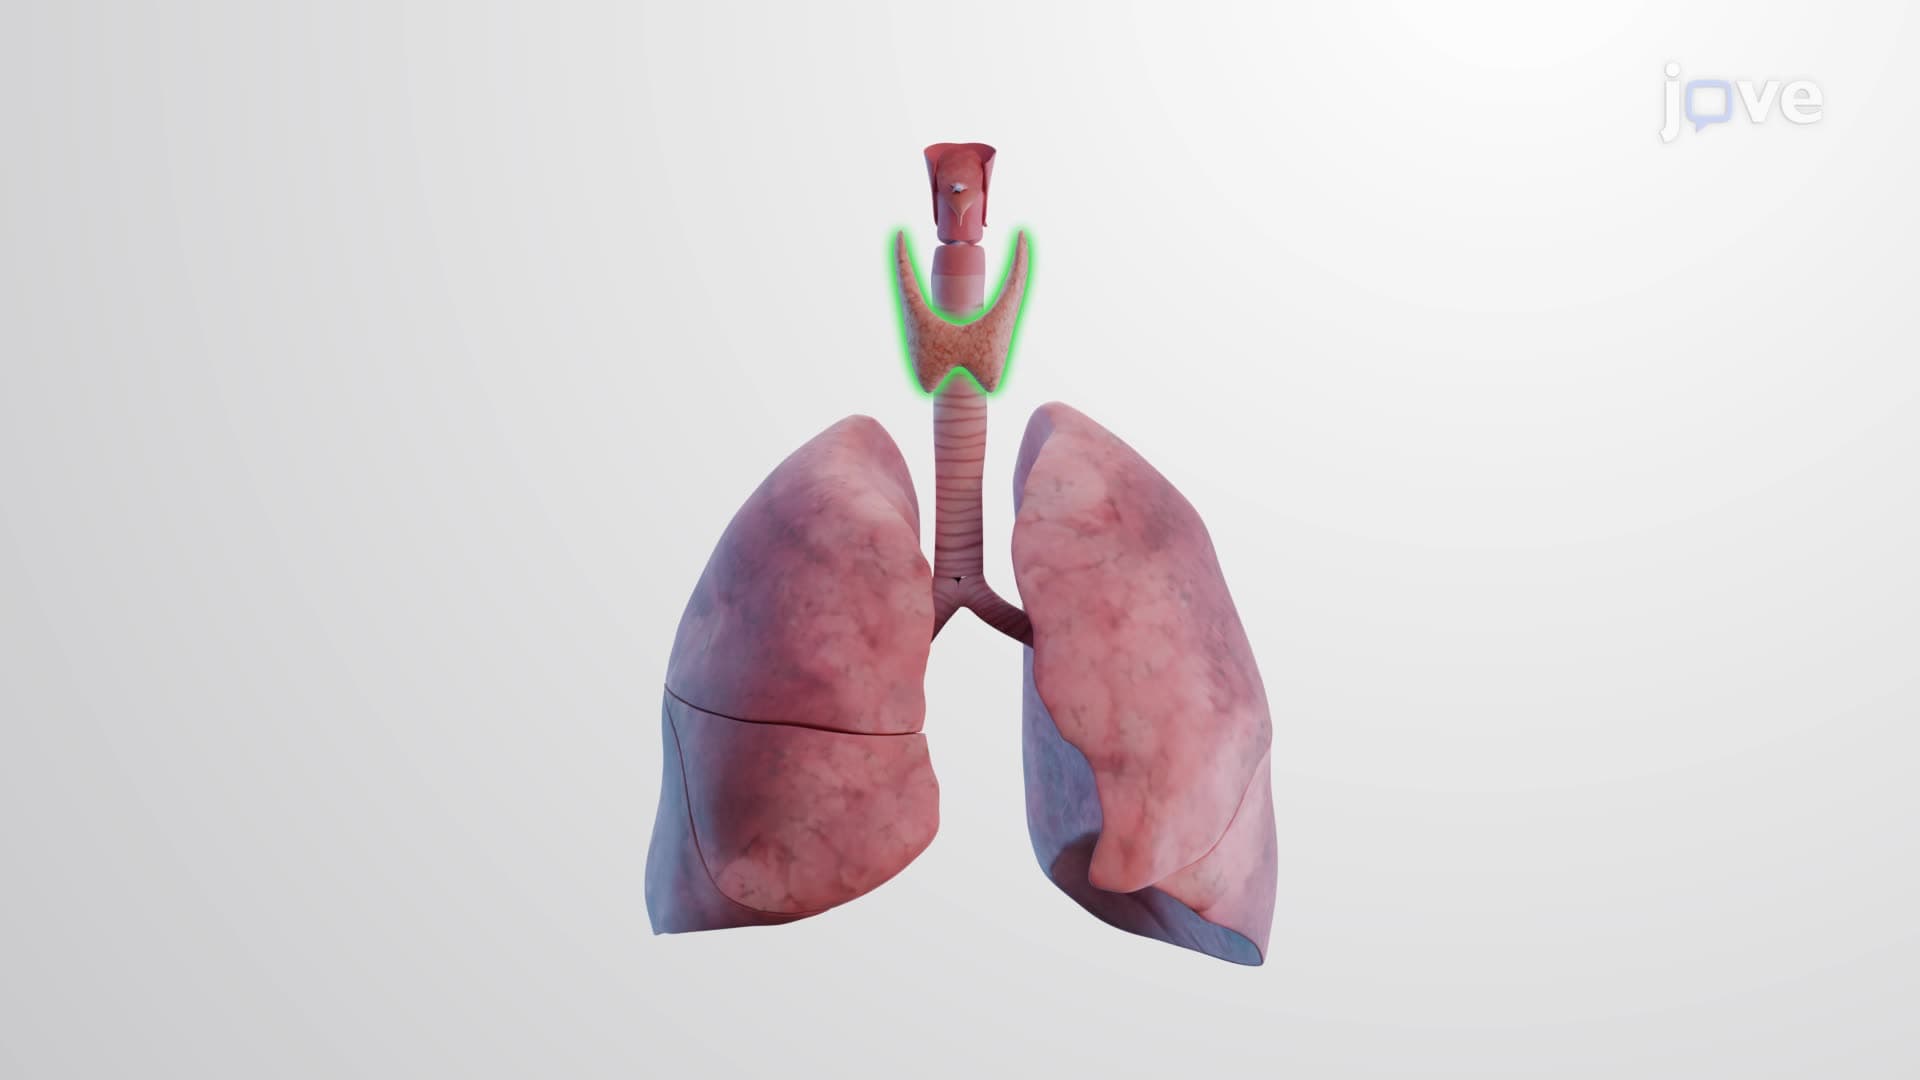
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...