Related Experiment Video
Updated: Jul 15, 2026


Closure of a Patent Foramen Ovale (PFO): An Intervention Sequence
Published on: December 23, 2022
Patent foramen ovale, stroke, and cardiovascular disease in migraine
Hans-Christoph Diener1, Tobias Kurth, David Dodick
1Department of Neurology, University of Duisburg-Essen, Essen, Germany. hans.diener@uni-duisburg-essen.de

Purpose Of Review:
We will review the literature on the association between migraine with patent foramen ovale, stroke, and coronary heart disease.
Recent Findings:
The prevalence of patent foramen ovale in patients with migraine with aura is significantly higher than in nonmigraine controls and migraineurs without aura. However, there is currently no evidence to support a causal relationship. Migraine with aura has been consistently associated with increased risk of ischemic stroke in several epidemiologic studies. Migraine with aura is associated with a more unfavourable cardiovascular risk profile and recent data suggest that the association between migraine with aura and stroke may extend to overall cardiovascular disease. Identification of migraine patients at particular risk for stroke or other vascular events is impossible based on current knowledge.
Summary:
Migraine with aura and patent foramen ovale have higher coincidences than expected by chance only. It is possible that both conditions are inherited together. Until now there has been no evidence from placebo-controlled randomized trials that closure of patent foramen ovale improves migraine with aura. There is increasing evidence that migraine with aura is not only a risk factor for ischemic stroke but also for myocardial infarction and other ischemic vascular events.
Insights
Migraine with aura is linked to a higher prevalence of patent foramen ovale, but a causal link is unproven. This condition also increases the risk of stroke and cardiovascular disease.
Area of Science:
- Cardiology
- Neurology
- Genetics
Background:
- Patent foramen ovale (PFO) is a cardiac anomaly with debated clinical significance.
- Migraine with aura (MA) is a complex neurological disorder.
- The co-occurrence of PFO and MA has been observed more frequently than expected by chance.
Purpose of the Study:
- To review the existing literature on the association between MA, PFO, stroke, and coronary heart disease.
- To evaluate the current evidence for a causal relationship between these conditions.
Main Methods:
- Literature review of observational studies and epidemiological data.
- Analysis of the prevalence of PFO in patients with and without MA.
- Assessment of the association between MA and cardiovascular events, including stroke and myocardial infarction.
Main Results:
- PFO prevalence is significantly higher in patients with MA compared to controls.
- No definitive evidence supports a causal relationship between PFO and MA.
- MA is consistently associated with an increased risk of ischemic stroke and potentially other cardiovascular diseases.
- Current knowledge does not allow for the identification of high-risk migraine patients for vascular events.
Conclusions:
- The higher coincidence of MA and PFO suggests a potential shared genetic or developmental origin.
- Evidence from randomized controlled trials on the efficacy of PFO closure for MA is lacking.
- MA is increasingly recognized as a risk factor for ischemic stroke, myocardial infarction, and other ischemic vascular events.

Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:15
Ischemic Stroke ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
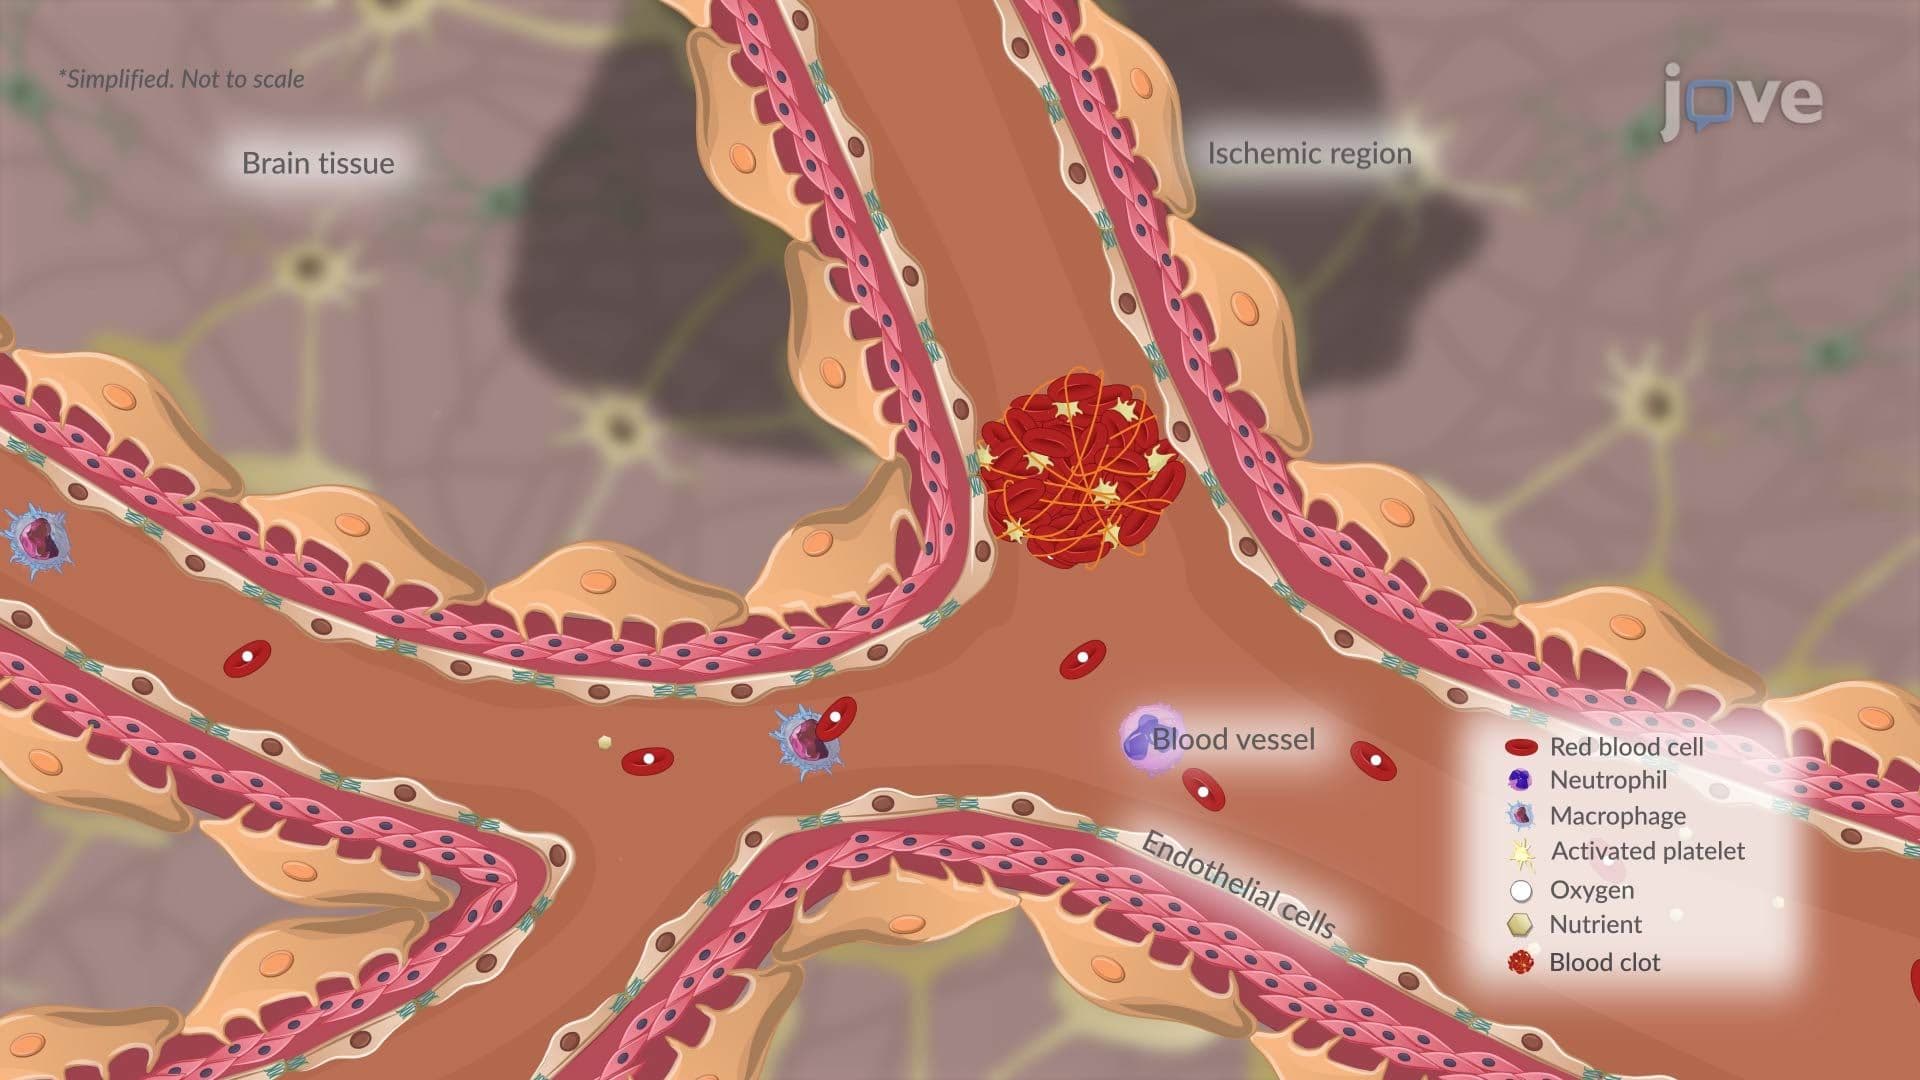 01:26
Transient Ischemic Attack l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction