Related Experiment Video
Updated: Jul 15, 2026
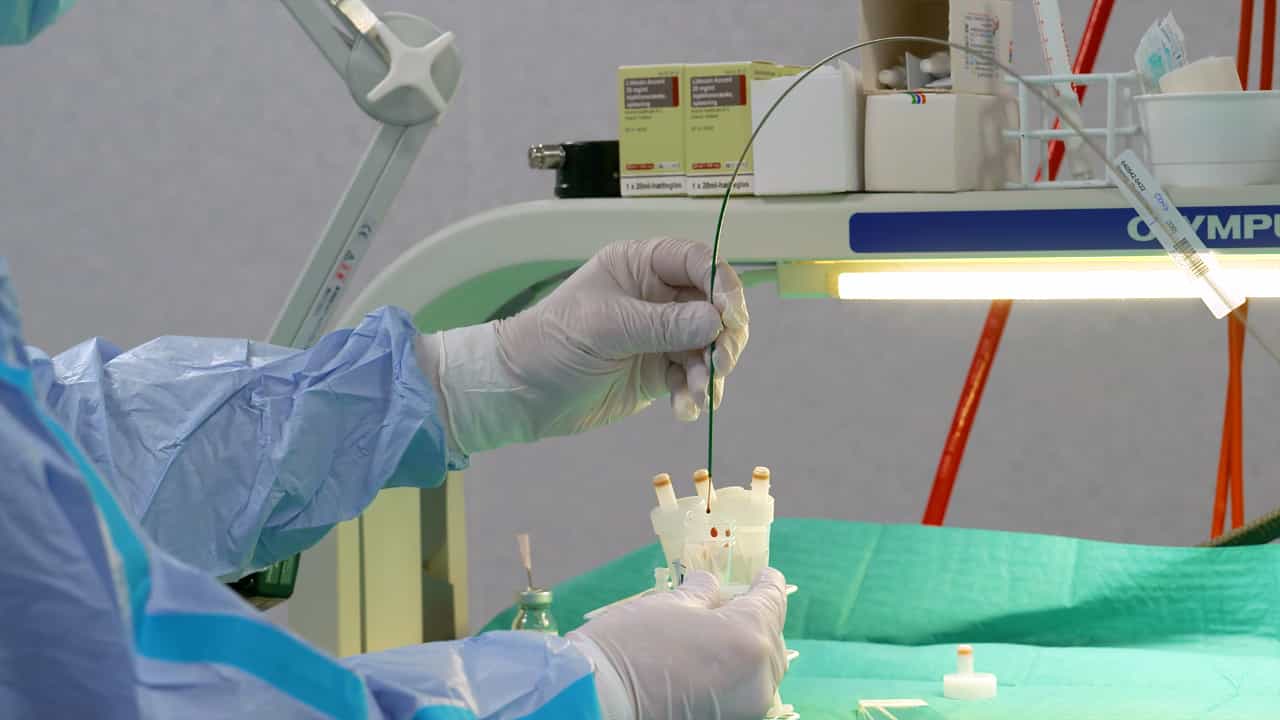

Using the Endoscope for Endobronchial Ultrasound in the Esophagus
Published on: November 21, 2023
Providing on-site diagnosis of malignancy on endoscopic-ultrasound-guided fine-needle aspirates: should it be done?
Nirag C Jhala1, Isam A Eltoum, Mohamad A Eloubeidi
1Department of Pathology, University of Alabama at Birmingham, Birmingham, AL 35249, USA. njhala@path.uab.edu

Background:
Rapid and accurate tissue diagnosis for a deep-seated malignancy would allow treating physicians to provide disease-specific interventions and help patients make early informed management decisions. Providing on-site tissue diagnosis for fine-needle aspirate samples obtained with endosonography would help develop such efficient patient management issues. Here we report our experience of prospectively providing on-site diagnosis on 485 endoscopic ultrasound fine-needle aspirate samples.
Methods:
Four hundred eighty-five endoscopic ultrasound fine-needle aspirates from the pancreas (n= 305), lymph nodes (n = 91), biliary tree (n = 47), liver (n = 15), gastrointestinal tract (n = 19), and adrenal gland (n = 8) were reviewed. For all aspirates, the cytologic diagnoses, both preliminary and final, were categorized into the following: positive for malignancy, positive for neoplastic process, suspicious for malignancy, atypical cells, reactive process, and nondiagnostic.
Results:
Of the 485 cases, 163 (33.6%) were diagnosed as benign, 43 (8.8%) as atypical, 21 (4.3%) as suspicious, 18 (3.7%) as positive for neoplasm, and 230 (47.4%) as malignant after final cytologic interpretation. A significantly (P < .001) higher degree of concordance was noted for unequivocal diagnosis of malignancy (196/198, 98.9%) vs nonmalignancy (200/250, 67.2%) between on-site and final cytologic diagnosis. Of the 52 discordant cases, 12 (2.6%) diagnoses were downgraded and 40 (8.9%) were upgraded from preliminary on-site diagnosis. Our overall sensitivity (87 vs 92), specificity (95% vs 100%), and accuracy (90% vs 94%) improved for final cytologic diagnosis.
Conclusion:
On-site diagnosis of malignancy could be used to initiate informed patient management decisions. Cases where a diagnosis of malignancy is not rendered at on-site interpretation need further cytologic evaluation.


Related Concept Videos
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Endoscopic Procedures V: ERCP
Patient...