Related Experiment Video
Updated: Jul 14, 2026
Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
[Early operative treatment of pelvic fractures associated with urethral disruption]
Jian Jia1, Lu-Zeng Guo, Chang-Lin Wu
1Center of Emergency and Traumatology, Tianjin Hospital, Tianjin 300211, China. jiajian1969@yahoo.com.cn

Objective:
To evaluate the early operative treatment and clinical results of pelvic fractures associated with urethra disruption.
Methods:
From January 1995 to January 2005, 25 patients suffered from pelvic fractures combined urethra disruption treated by operation were retrospectively analyzed. According to Tile's classification, 1 case was stable pelvic fracture, 17 rotational unstable fractures, and 7 rotational combined vertical unstable fractures. The complete urethra rupture were in 23 cases and incomplete in 2 cases. The operative methods included: (1) emergency open reduction and internal fixation of the pelvis combined primary urethra suturing in 2 cases, partial suturing after realignment in 4 cases, realignment in 2 cases, and urethrovaginal penetrating wound repairing in 1 case; (2) primary urethra realignment only and delayed (range, 7 to 21 days) pelvic internal fixation in 10 cases; (3) early cystostomy and delayed (range, 3 to 21 days) urethra realignment and pelvic internal fixation in 6 cases.
Results:
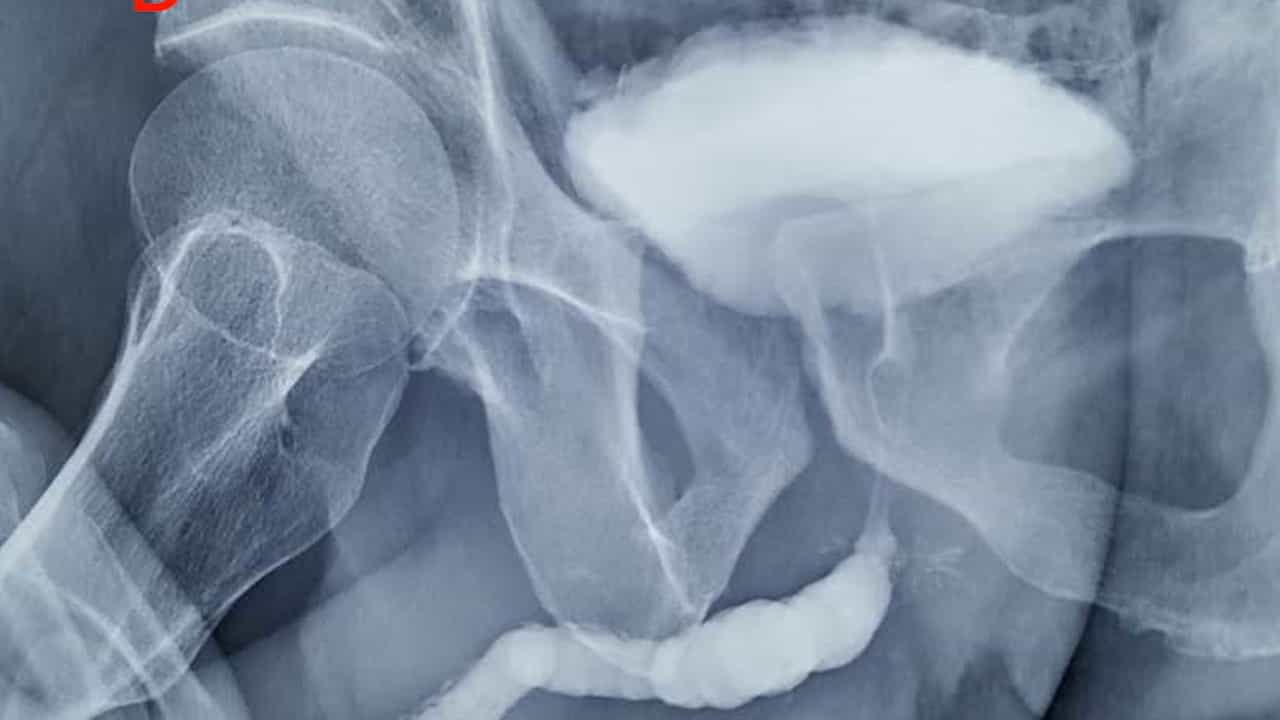
The mean follow-up time of all patients was 34 months (range from 6 to 120 months). According to Majeed's evaluation, 17 cases of pelvic injury showed excellent results, 5 good, and 3 fare. After urinary catheter removed, the mean maximal urine flow rate of 19 (76%) patients was 18.6 ml/s and the mean scar length between both disrupted ends on the film of excretion urethrography was 0.51 cm. Five (20%) cases suffered in dysuria needed urethral dilatation or further surgery. One (4%) female could not control urination who need a second-look operation. The primary suprapubic soft tissue avulsion wound infection secondary to retropubic abscess was found in 1 case, posterior urethra-stenosis in 5 cases, sexual impotence in 3 cases, and incontinence in 1 case.
Conclusions:
The satisfactory reduction and effective fixation of the pelvic fractures is an anatomical basis for receiving "tension-free urethral anastomosis".
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:28
Urinary Tract Calculi V: Nursing Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...