Related Experiment Video
Updated: Jul 14, 2026
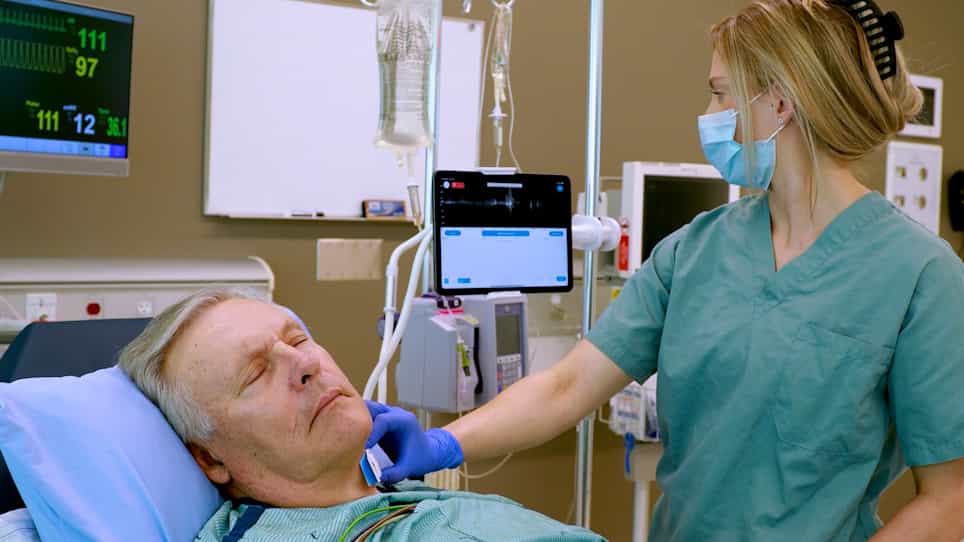

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Can dynamic indicators help the prediction of fluid responsiveness in spontaneously breathing critically ill
Stéphane Soubrier1,2, Fabienne Saulnier3,4, Hervé Hubert4
1Service de Réanimation Médicale, Hôpital Calmette, CHRU, boulevard du Pr Leclercq, 59037, Lille cedex, France. ssoubrier@nordnet.fr.

Objective:
To investigate whether the respiratory changes in arterial pulse (DeltaPP) and in systolic pressure (DeltaSP) could predict fluid responsiveness in spontaneously breathing (SB) patients. Because changes in intrathoracic pressure during spontaneous breathing (SB) might be insufficient to modify loading conditions of the ventricles, performances of indicators were also assessed during a forced respiratory maneuver.
Design:
Prospective interventional study.
Setting:
A 34-bed university hospital medico-surgical ICU.
Patients And Participants:
Thirty-two SB patients with clinical signs of hemodynamic instability.
Intervention:
A 500-ml volume expansion (VE).
Measurements And Results:
Cardiac index, assessed using transthoracic echocardiography, increased by at least 15% after VE in 19 patients (responders). At baseline, only dynamic indicators were higher in responders than in nonresponders (13+/-5% vs. 7+/-3%, p=0.003 for DeltaPP and 10+/-4% vs. 6+/-2%, p=0.002 for DeltaSP). Moreover, they significantly decreased after VE (11+/-5% to 6+/-4%, p<0.001 for DeltaPP and 8+/-4% to 6+/-3%, p<0.001 for DeltaSP). DeltaPP and DeltaSP areas under the ROC curve were high (0.81+/-0.08 and 0.82+/-0.08; p=0.888, respectively). A DeltaPP>or=12% predicted fluid responsiveness with high specificity (92%) but poor sensitivity (63%). The forced respiratory maneuver reproducing a dyspneic state decreased the predictive power.
Conclusions:
Due to their lack of sensitivity and their dependence to respiratory status, DeltaPP and DeltaSP are clearly less reliable to predict fluid responsiveness during SB than in mechanically ventilated patients. However, when their baseline value is high without acute right ventricular dysfunction in a participating patient, a positive response to fluid is likely.
More Related Videos
 14:28
Non-Invasive Monitoring of Microvascular Oxygenation and Reactive Hyperemia using Hybrid, Near-Infrared Diffuse Optical Spectroscopy for Critical Care
Published on: May 10, 2024
 05:56
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Related Concept Videos
 01:23
Acute Respiratory Failure-IV
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:30
Acute Respiratory Failure-III
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...