Related Experiment Video
Updated: Jul 14, 2026


Hypoxia Alters miRNAs Levels Involved in Non-Mendelian Inheritance of Autism Spectrum Disorder in Mice
Published on: July 11, 2025
Maternal oxygen delivery is not related to altitude- and ancestry-associated differences in human fetal growth
Stacy Zamudio1, Lucrecia Postigo, Nicholas P Illsley
1Department of Obstetrics Gynecology and Women's Helath, New Jersey Medical School, 185 South Orange Avenue, Newark, NJ 07103, USA. stacy.zamudio@umdnj.edu

Fetal growth is reduced at high altitude, but the decrease is less among long-resident populations. We hypothesized that greater maternal uteroplacental O(2) delivery would explain increased fetal growth in Andean natives versus European migrants to high altitude. O(2) delivery was measured with ultrasound, Doppler and haematological techniques. Participants (n=180) were pregnant women of self-professed European or Andean ancestry living at 3600 m or 400 m in Bolivia. Ancestry was quantified using ancestry-informative single nucleotide polymorphism. The altitude-associated decrement in birth weight was 418 g in European versus 236 g in Andean women (P<0.005). Altitude was associated with decreased uterine artery diameter, volumetric blood flow and O(2) delivery regardless of ancestry. But the hypothesis was rejected as O(2) delivery was similar between ancestry groups at their respective altitudes of residence. Instead, Andean neonates were larger and heavier per unit of O(2) delivery, regardless of altitude (P<0.001). European admixture among Andeans was negatively correlated with birth weight at both altitudes (P<0.01), but admixture was not related to any of the O(2) transport variables. Genetically mediated differences in maternal O(2) delivery are thus unlikely to explain the Andean advantage in fetal growth. Of the other independent variables, only placental weight and gestational age explained significant variation in birth weight. Thus greater placental efficiency in O(2) and nutrient transport, and/or greater fetal efficiency in substrate utilization may contribute to ancestry- and altitude-related differences in fetal growth. Uterine artery O(2) delivery in these pregnancies was 99 +/- 3 ml min(-1), approximately 5-fold greater than near-term fetal O(2) consumption. Deficits in maternal O(2) transport in third trimester normal pregnancy are unlikely to be causally associated with variation in fetal growth.
Fetal growth is reduced at high altitude, but the decrease is less among long-resident populations. We hypothesized that greater maternal uteroplacental O(2) delivery would explain increased fetal growth in Andean natives versus European migrants to high altitude. O(2) delivery was measured with ultrasound, Doppler and haematological techniques. Participants (n=180) were pregnant women of self-professed European or Andean ancestry living at 3600 m or 400 m in Bolivia. Ancestry was quantified using ancestry-informative single nucleotide polymorphism. The altitude-associated decrement in birth weight was 418 g in European versus 236 g in Andean women (P<0.005). Altitude was associated with decreased uterine artery diameter, volumetric blood flow and O(2) delivery regardless of ancestry. But the hypothesis was rejected as O(2) delivery was similar between ancestry groups at their respective altitudes of residence. Instead, Andean neonates were larger and heavier per unit of O(2) delivery, regardless of altitude (P<0.001). European admixture among Andeans was negatively correlated with birth weight at both altitudes (P<0.01), but admixture was not related to any of the O(2) transport variables. Genetically mediated differences in maternal O(2) delivery are thus unlikely to explain the Andean advantage in fetal growth. Of the other independent variables, only placental weight and gestational age explained significant variation in birth weight. Thus greater placental efficiency in O(2) and nutrient transport, and/or greater fetal efficiency in substrate utilization may contribute to ancestry- and altitude-related differences in fetal growth. Uterine artery O(2) delivery in these pregnancies was 99 +/- 3 ml min(-1), approximately 5-fold greater than near-term fetal O(2) consumption. Deficits in maternal O(2) transport in third trimester normal pregnancy are unlikely to be causally associated with variation in fetal growth.


Related Concept Videos
 01:24
Factors Affecting Respiration
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:27
Oxygen Transport in the Blood
 01:29
Oxygen Requirements and Growth Patterns
 01:20
Respiration and Gaseous Exchange
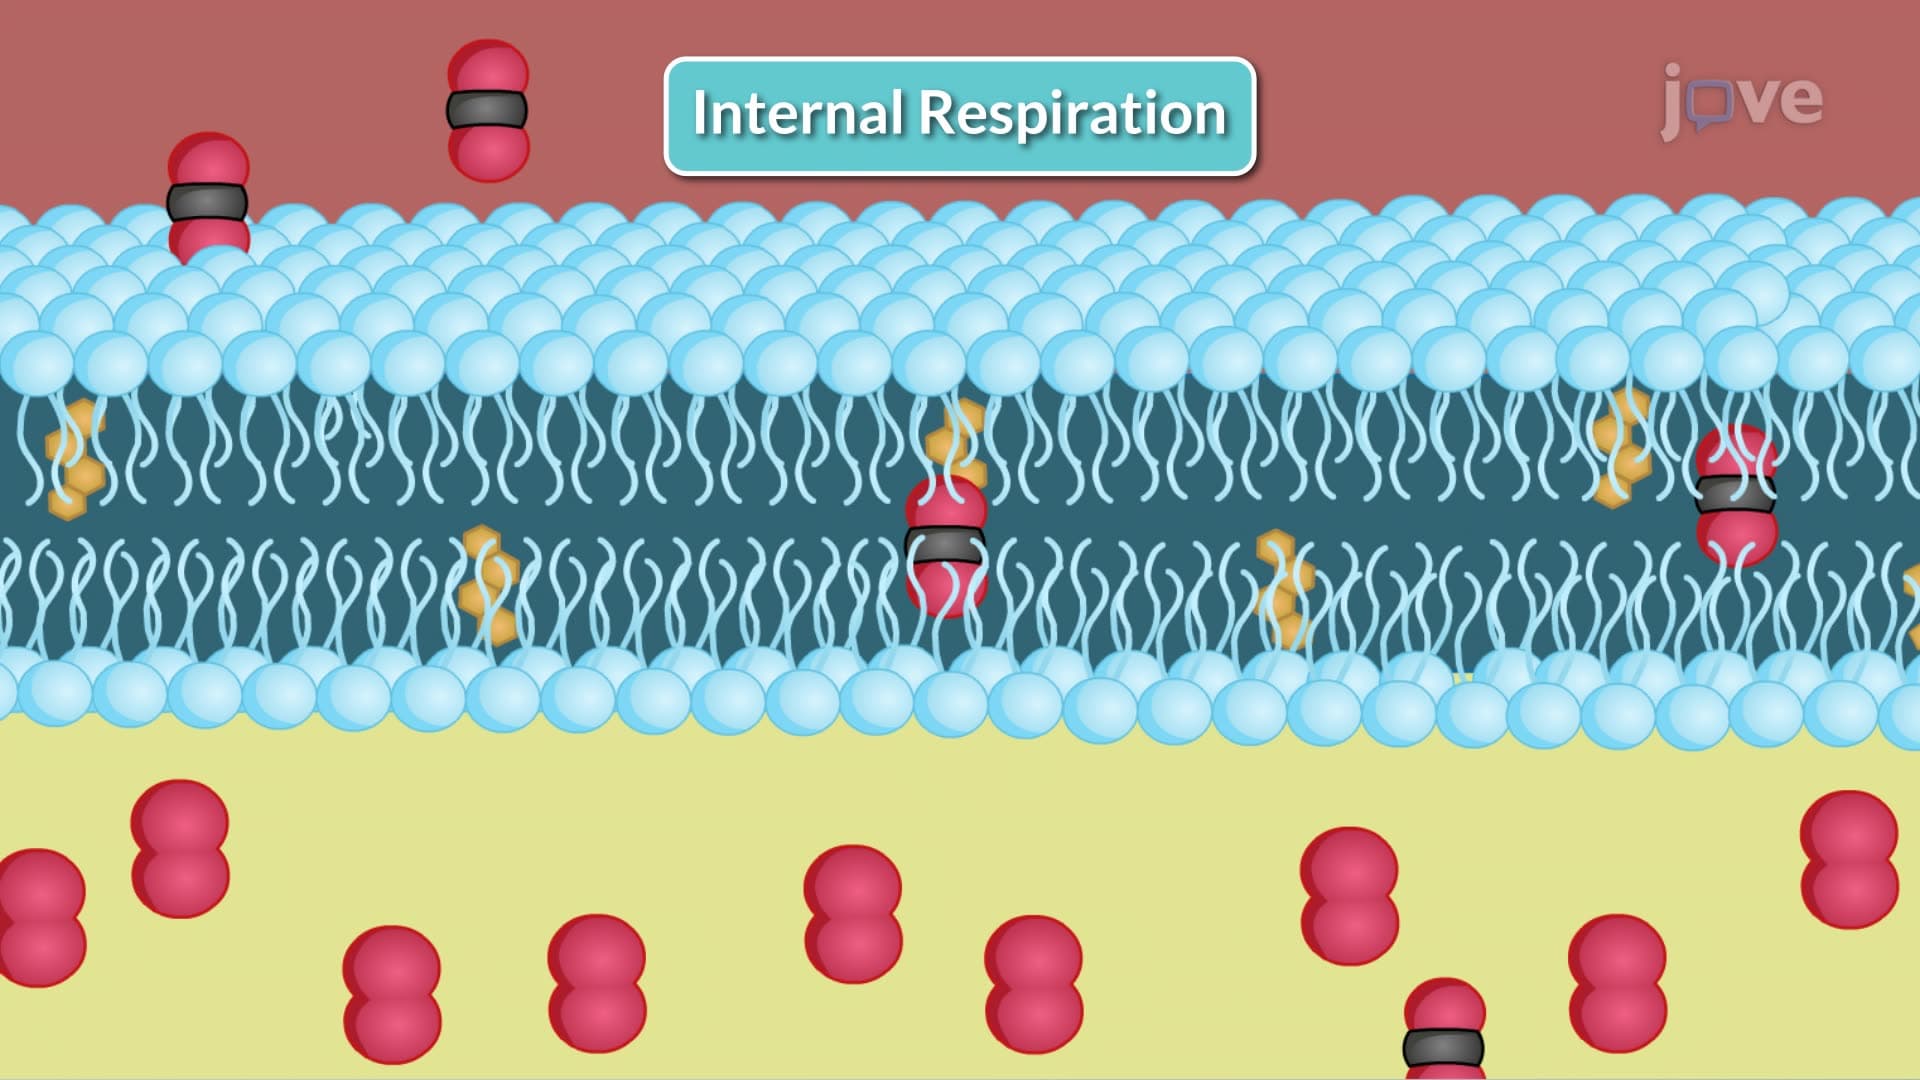
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: