Related Experiment Video
Updated: Jul 14, 2026
Using In Vitro Live-cell Imaging to Explore Chemotherapeutics Delivered by Lipid-based Nanoparticles
Published on: November 1, 2017
Pegylated liposomal doxorubicin treatment in recurrent gynecologic cancer patients with renal dysfunction
Yanfang Li1, Kevin W Finkel, Wei Hu
1Department of Gynecologic Oncology, The University of Texas M. D. Anderson Cancer Center, Houston, Texas, 1155 Pressler Street, Houston, TX 77030, USA.

Objectives:
A paucity of data exists regarding the efficacy and toxicity of pegylated liposomal doxorubicin (PLD) in cancer patients with chronic kidney disease (CKD). We sought to investigate the toxicity and efficacy of PLD in gynecologic cancer patients with CKD.
Methods:
The clinical records of all patients with recurrent gynecological cancer and CKD at the University of Texas M.D. Anderson Cancer Center from 08/1999 to 08/2006 were reviewed retrospectively to identify patients who received PLD.
Results:
Twenty-eight patients were identified, which included 14 with epithelial ovarian cancer, 4 with peritoneal cancer, and 10 with other gynecologic cancers. CKD was defined as a creatinine clearance (CrCl) of <90 ml/min/1.73 m(2) and classified as mild (5 patients), moderate (16 patients), or severe (7 patients) (CrCl 60-89, 30-59, and <30 ml/min/1.73 m(2), respectively). The initial doses of PLD were classified into regular initial dose (40 mg/m(2)/4 weeks) and lower initial dose (30-35 mg/m(2)/4 weeks). The median cycle was 4.5 (range 1-17). The incidence of grade 3-4 palmar-plantar erythrodysesthesia, stomatitis, and hematologic toxicity was 11.1% (2/18), 5.6% (1/18), and 16.7% (3/18) among 18 patients with an initial dose of 40 mg/m(2)/4 weeks, which included 5, 10, and 3 patients with mild, moderate, and severe CKD, respectively. Dose reduction due to toxicities occurred in 33.3% (6/18) patients. In 18 patients with ovarian and peritoneal cancer (all platinum-resistant), the rates of complete response, partial response, stable disease, and progression were 0%, 11.1%, 44.4%, and 44.4%, respectively.
Conclusions:
Patients with CKD who received PLD therapy at an initial dose of 40 mg/m(2)/4 weeks may require greater subsequent dose reduction mainly secondary to mucocutaneous and hematologic toxicities. Treatment response in this population with ovarian and peritoneal cancer was similar to that of patients with normal renal function.

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:24
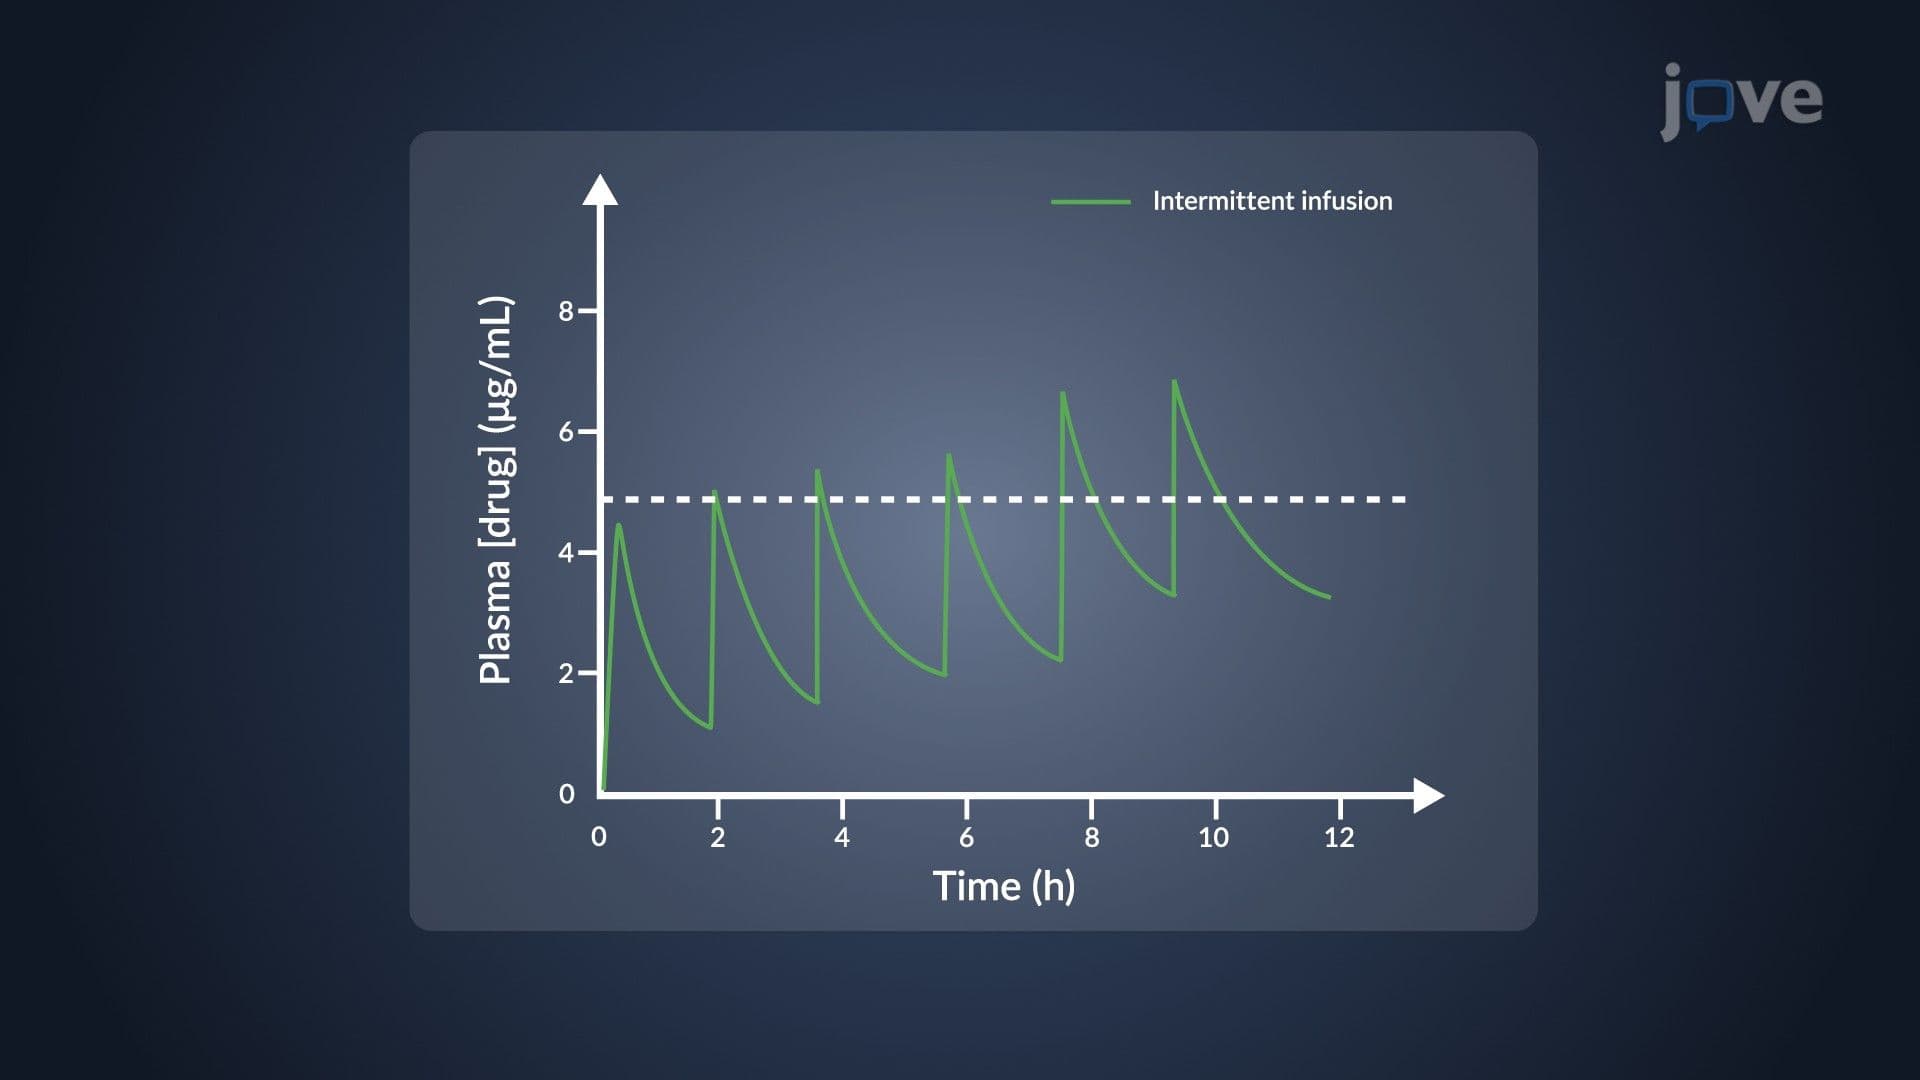
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:25
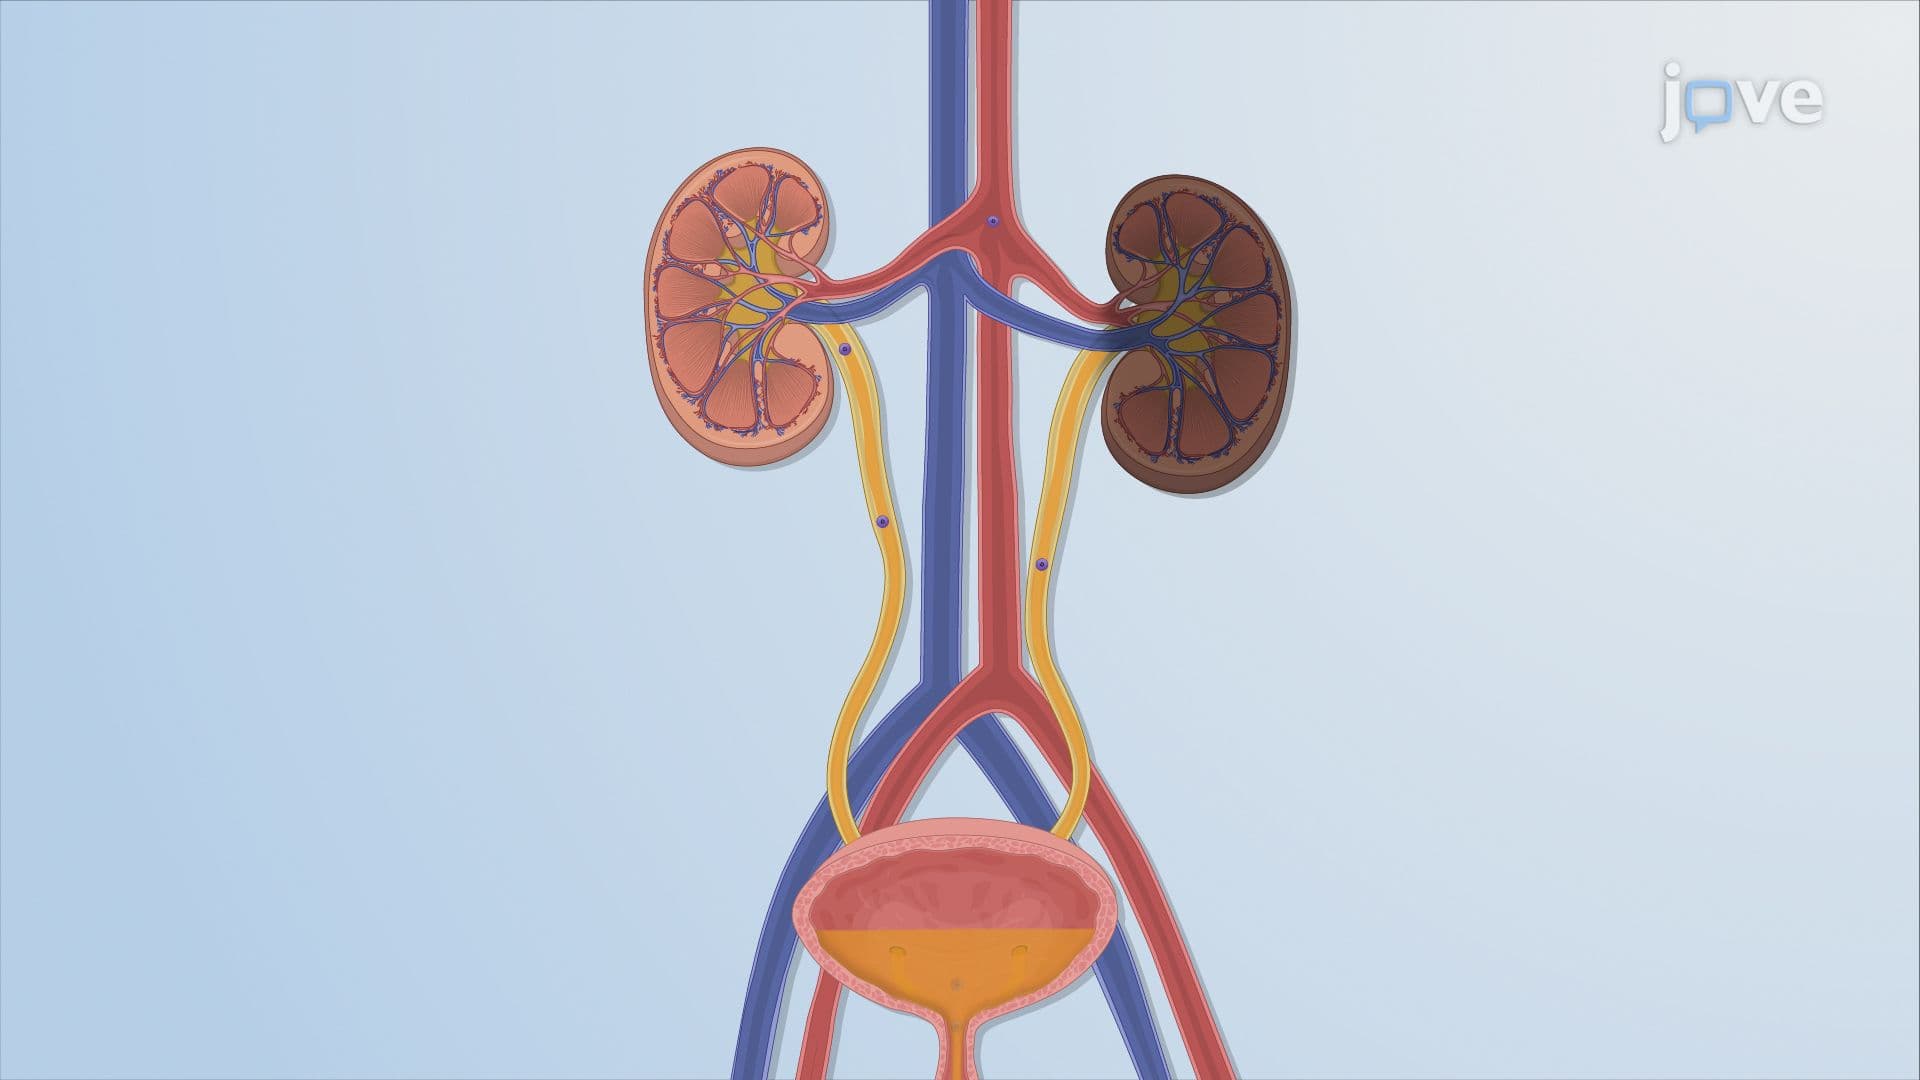
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant