Related Experiment Video
Updated: Jul 14, 2026


Detection of Helicobacter pylori Infection and Antibiotic Resistance via Stool Quantitative Polymerase Chain Reaction Analysis
Published on: May 16, 2025
Culture of Helicobacter pylori from stool samples in children
Tahereh Falsafi1, Nargess Valizadeh, Mehri Najafi
1Department of Biology Microbiology, Azzahra University, 1993891176 Tehran, Iran. tfalsafi@yahoo.com

Insights
We evaluated two stool culture protocols for isolating Helicobacter pylori in children. Cholestyramine treatment improved H. pylori recovery from stool samples, especially in cases with lower gastric bacterial density.
Area of Science:
- Medical Microbiology
- Pediatric Gastroenterology
Background:
- Helicobacter pylori infection is a common cause of pediatric gastrointestinal issues.
- Accurate diagnosis is crucial for effective treatment and management.
- Stool-based diagnostic methods offer a non-invasive alternative to traditional biopsy procedures.
Purpose of the Study:
- To compare the efficacy of two stool culture protocols for Helicobacter pylori isolation in children.
- To evaluate the impact of bacterial density and bile inactivation on stool culture yield.
Main Methods:
- Comparison of biopsy-based tests with stool antigen tests and stool culture in 23 children.
- Evaluation of two stool culture protocols (standard vs. cholestyramine treatment) in 20 non-biopsied children.
- Identification of H. pylori isolates using Gram staining, slide agglutination, biochemical tests, and PCR.
Main Results:
- Helicobacter pylori was successfully isolated from stool samples of biopsied children with low to moderate gastric bacterial density.
- Cholestyramine treatment of stool samples significantly improved H. pylori isolation yield in non-biopsied children.
- The density of H. pylori in the stomach appears to influence stool sample recovery, with bile inactivation enhancing culture success.
Conclusions:
- Stool culture, particularly with cholestyramine treatment, is a viable method for diagnosing H. pylori infection in children.
- Bile inactivation using cholestyramine enhances the isolation of an enhanced metabolic form of H. pylori from stool.
- Gastric bacterial density may impact the successful recovery of H. pylori from stool specimens.
Abstract:
We evaluated two protocols for isolation of Helicobacter pylori in stool from biopsied and nonbiopsied children. Twenty-three child patients whose presumptive positivity or negativity was diagnosed by endoscopy and a rapid urease test at site were used to compare biopsy-based tests with stool-based tests (H. pylori stool antigen test and stool culture). Their gastric activity and bacterial density were graded by the updated Sydney system. Biopsy and stool specimens were cultured on Campy-blood and Belo horizonte agar plates after enrichment in selective Campy-Thio medium. To compare two stool culture protocols, stools from 20 nonbiopsied children were tested by the HpSA test and cultured either as above or after treatment with cholestyramine. Grown colonies were screened by Gram staining, slide agglutination using anti-H. pylori monoclonal IgG; positive isolates were tested by biochemical tests and polymerase chain reaction for H. pylori-specific ureA gene. Coccoid H. pylori was isolated in stool samples from the biopsied patients whose bacterial density was two to four in histology. Their oxidase was slightly positive but became positive after two subcultures, while additional biochemical tests confirmed the isolation of H. pylori. Similar coccoid but oxidase positive H. pylori was isolated from three nonbiopsied children with the protocol of cholestyramine treatment only. The density of bacteria in the stomach may influence the recovery of H. pylori from stool; inactivation of bile with cholestyramine improves the yield in culture and favors isolation of an enhanced metabolic form of bacteria.
More Related Videos
 03:33
Rapid Detection of Fecal Antigen of Helicobacter pylori Infection Based on Double Antibody Sandwich Detection Technology
Published on: May 23, 2025
 06:40
Quantitative Polymerase Chain Reaction (qPCR)-Based Rapid Diagnosis of Helicobacter pylori Infection and Antibiotic Resistance
Published on: July 28, 2023
Related Concept Videos
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:27
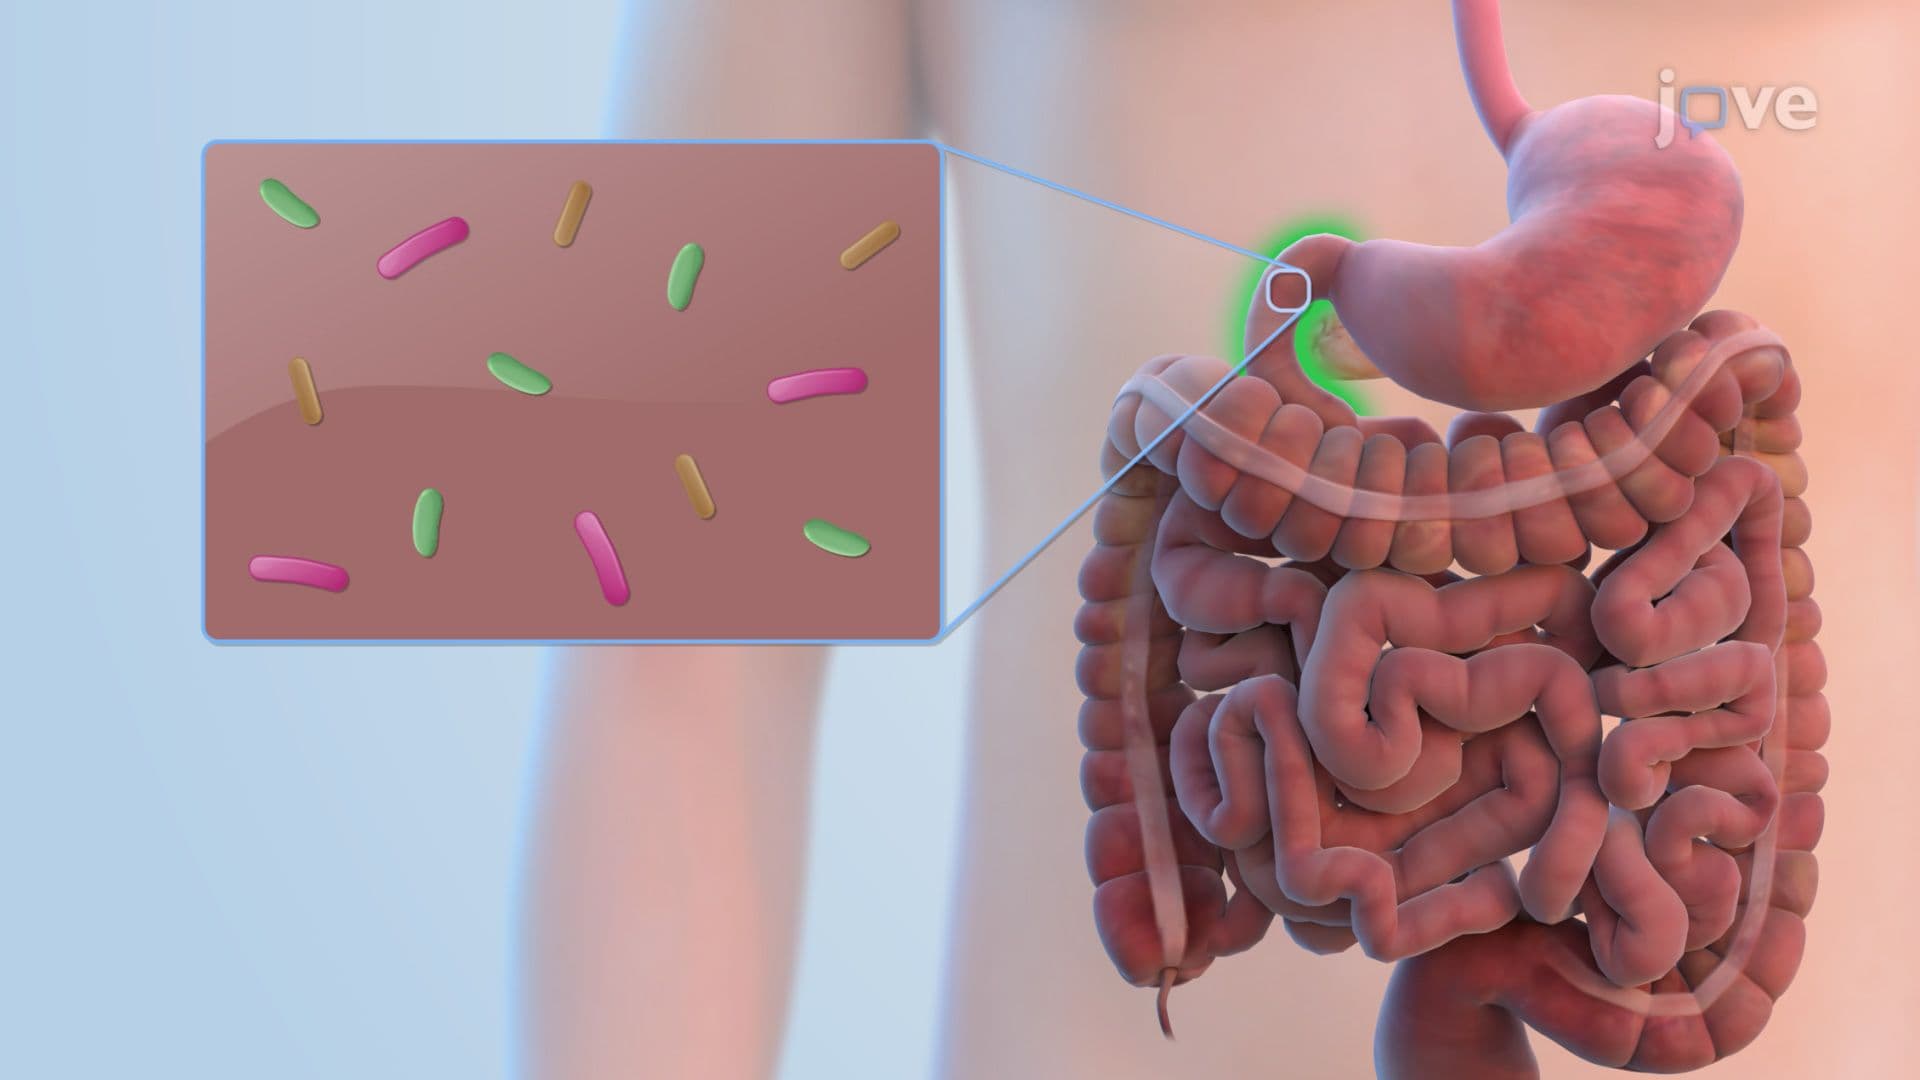
Microbiota of the Stomach and Small Intestine
 01:27
Peptic Ulcer
 01:26
Gastritis II: Pathophysiology
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:30
Serum Laboratory Studies, Stool Test, Breath Test