Related Experiment Video
Updated: Jul 14, 2026


Skin Biopsy for Diagnosing Discoid Lupus Erythematosus
Published on: June 10, 2025
Histological diversity of reactive and atypical proliferative lymph node lesions in systemic lupus erythematosus
Masaru Kojima1, Tadashi Motoori, Shigeyuki Asano
1Department of Pathology and Clinical Laboratories, Gunma Cancer Center Hospital, Ohta, Japan. mkojima@gunma-cc.jp

Abstract:
Localized or generalized lymphadenopathy, which may be associated with systemic symptoms such as fever, is frequently found in patients with systemic lupus erythematosus (SLE). Histologically, the lymph node lesion is characterized by varying degrees of coagulative necrosis with hematoxylin bodies or reactive follicular hyperplasia. The former histology is unique to SLE, but is rarely seen in biopsied specimens. In this review, we describe a histologic variation of SLE lymphadenopathy based on the findings of our own cases, and discuss several problems related to the differential diagnosis of various benign and malignant lymphoproliferative disorders (LPDs). Among 33 cases we encountered, 17 (51%) cases exhibited atypical LPDs: (i) reactive follicular hyperplasia with giant follicles (RFHGFs), 3 cases; (ii) histologic findings of Castleman's disease (CD), 5 cases ; (iii) atypical paracortical hyperplasia with lymphoid follicles (APHLFs), 7 cases; and (iv) atypical lymphoplasmacytic and immunoblastic proliferation (ALPIBP), 2 cases. This finding indicates that atypical LPDs frequently appear in SLE. Moreover, the majority of patients with atypical LPDs exhibited follicular hyperplasia (RFHGF, 3 cases; histologic findings of CD, 5 cases; and APHLF, 7 cases). Previously, follicular hyperplasia was usually considered a non-specific change and therefore has received little attention in the literature. However, the present review indicates that reactive follicular hyperplasia in lymph nodes from SLE occasionally poses serious problems in the differential diagnosis of various benign and malignant LPDs. The presence of numerous copies of Epstein-Barr virus was determined by in situ hybridization studies in only two (8%) of the 26 cases examined. As previously suggested, the absence of EBV, as determined by ISH studies, in the majority of LPDs associated with SLE indicates that EBV is not related to the lymphoproliferative process, and suggests that the underlying cause of the patient's lymphadenopathy may reside in the immune deficit of SLE in the majority of reactive and atypical LPDs associated with SLE.

Related Concept Videos
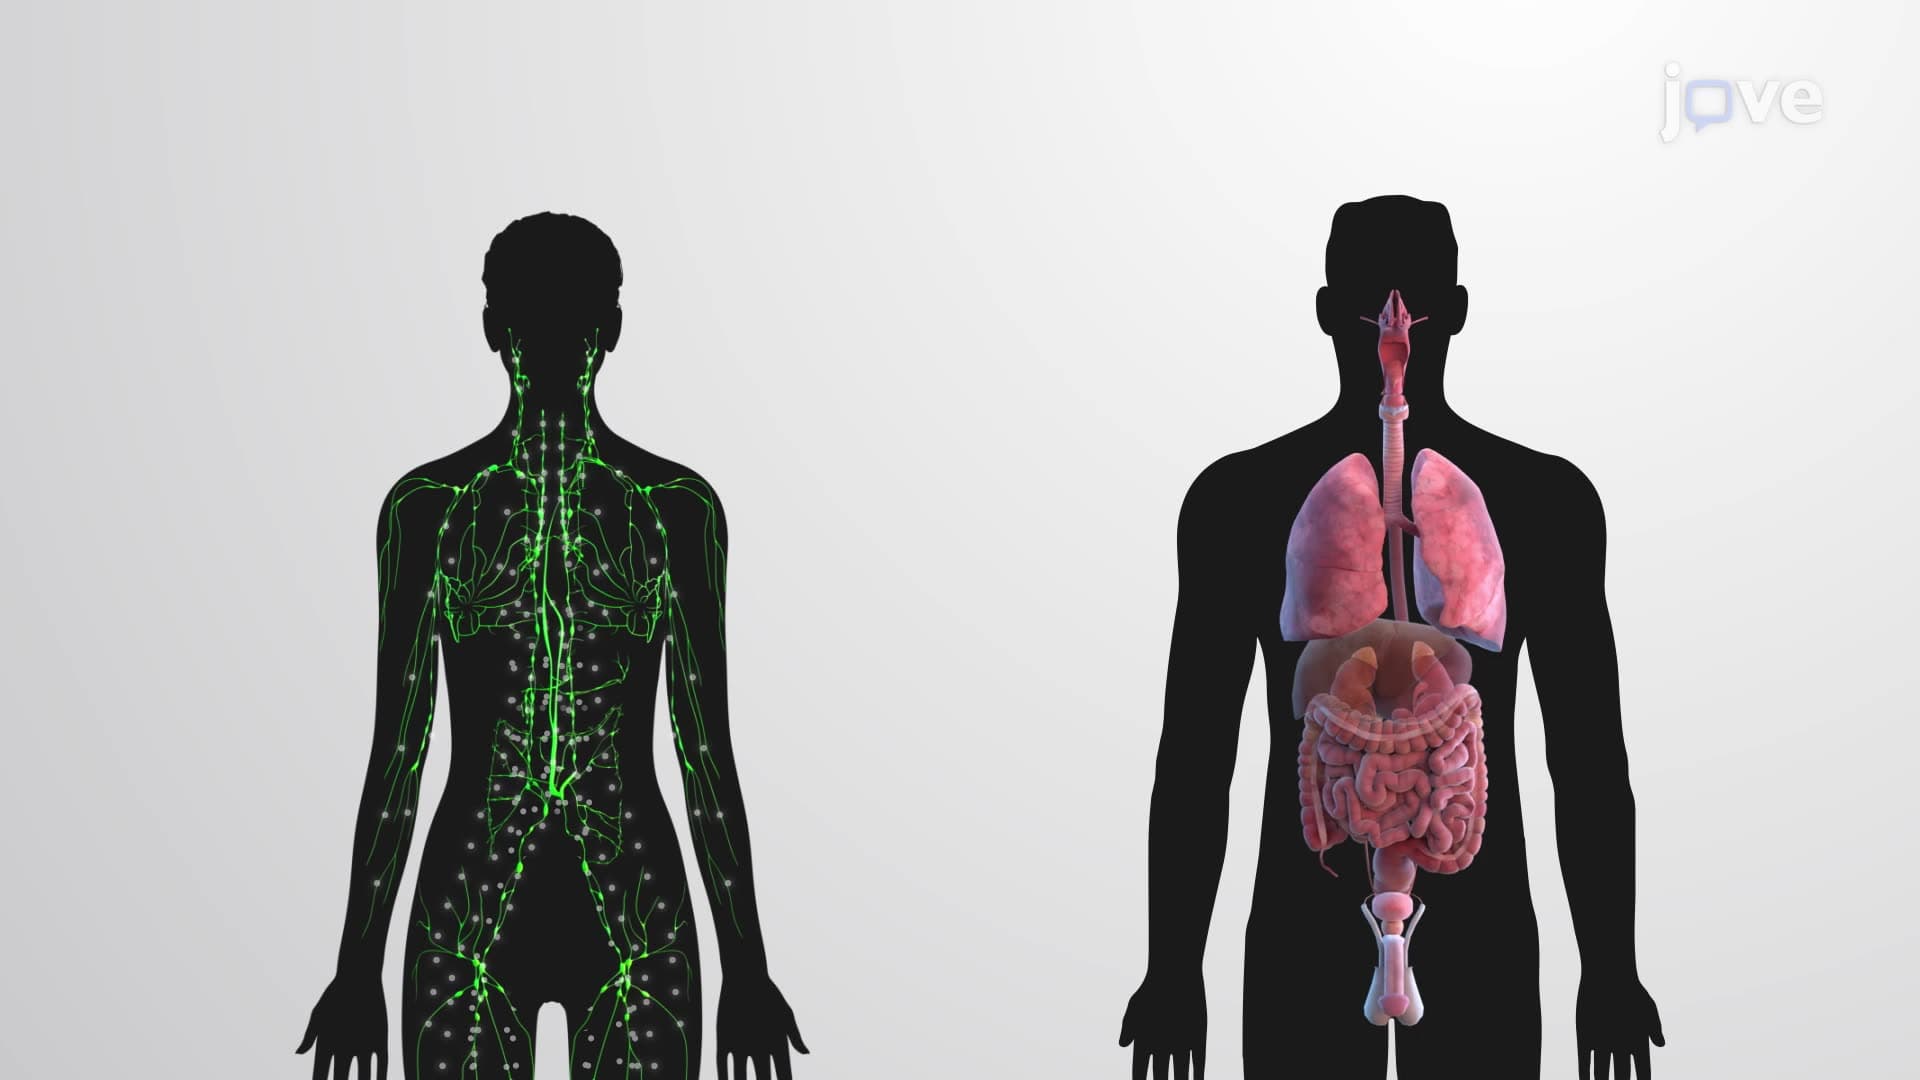 01:18
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
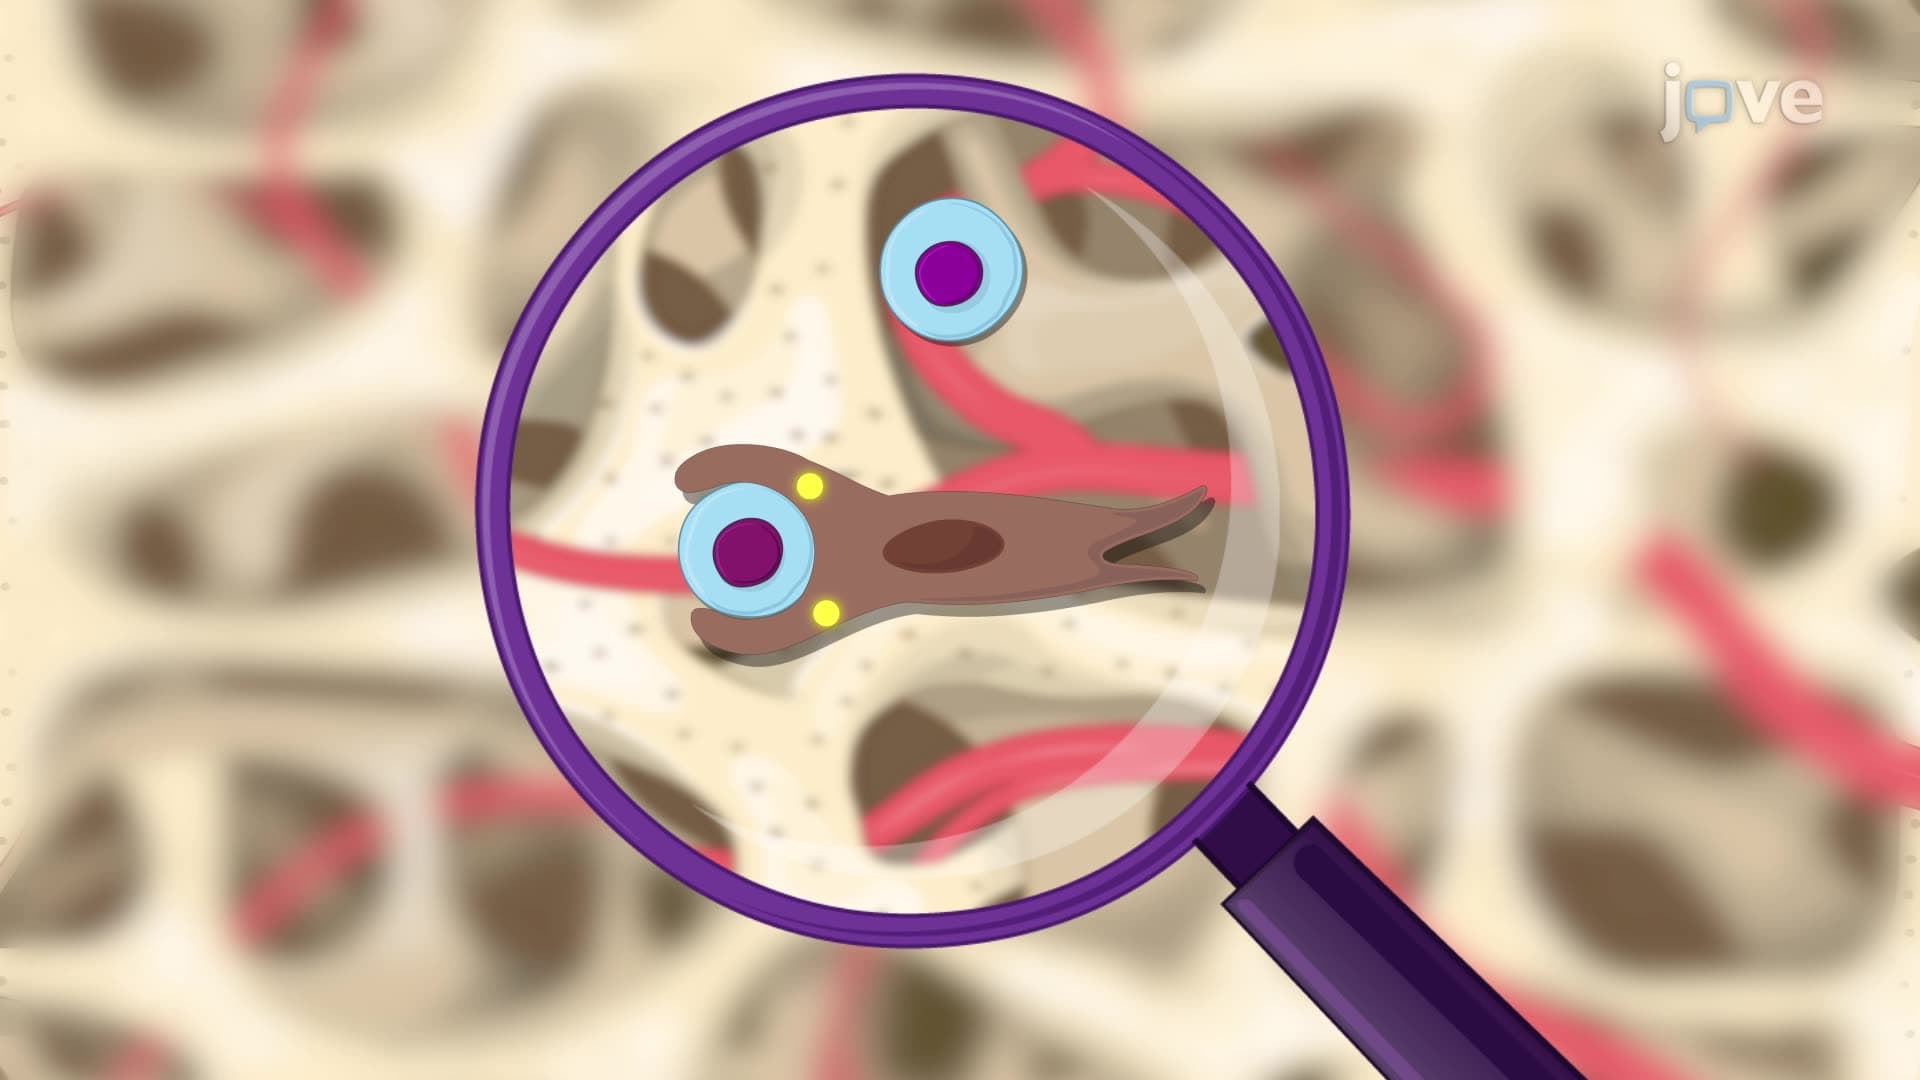 01:16
Primary Lymphoid Organs
The red bone marrow is a soft, spongy tissue nestled in the interior of long bones such as the humerus and femur. It is the site...
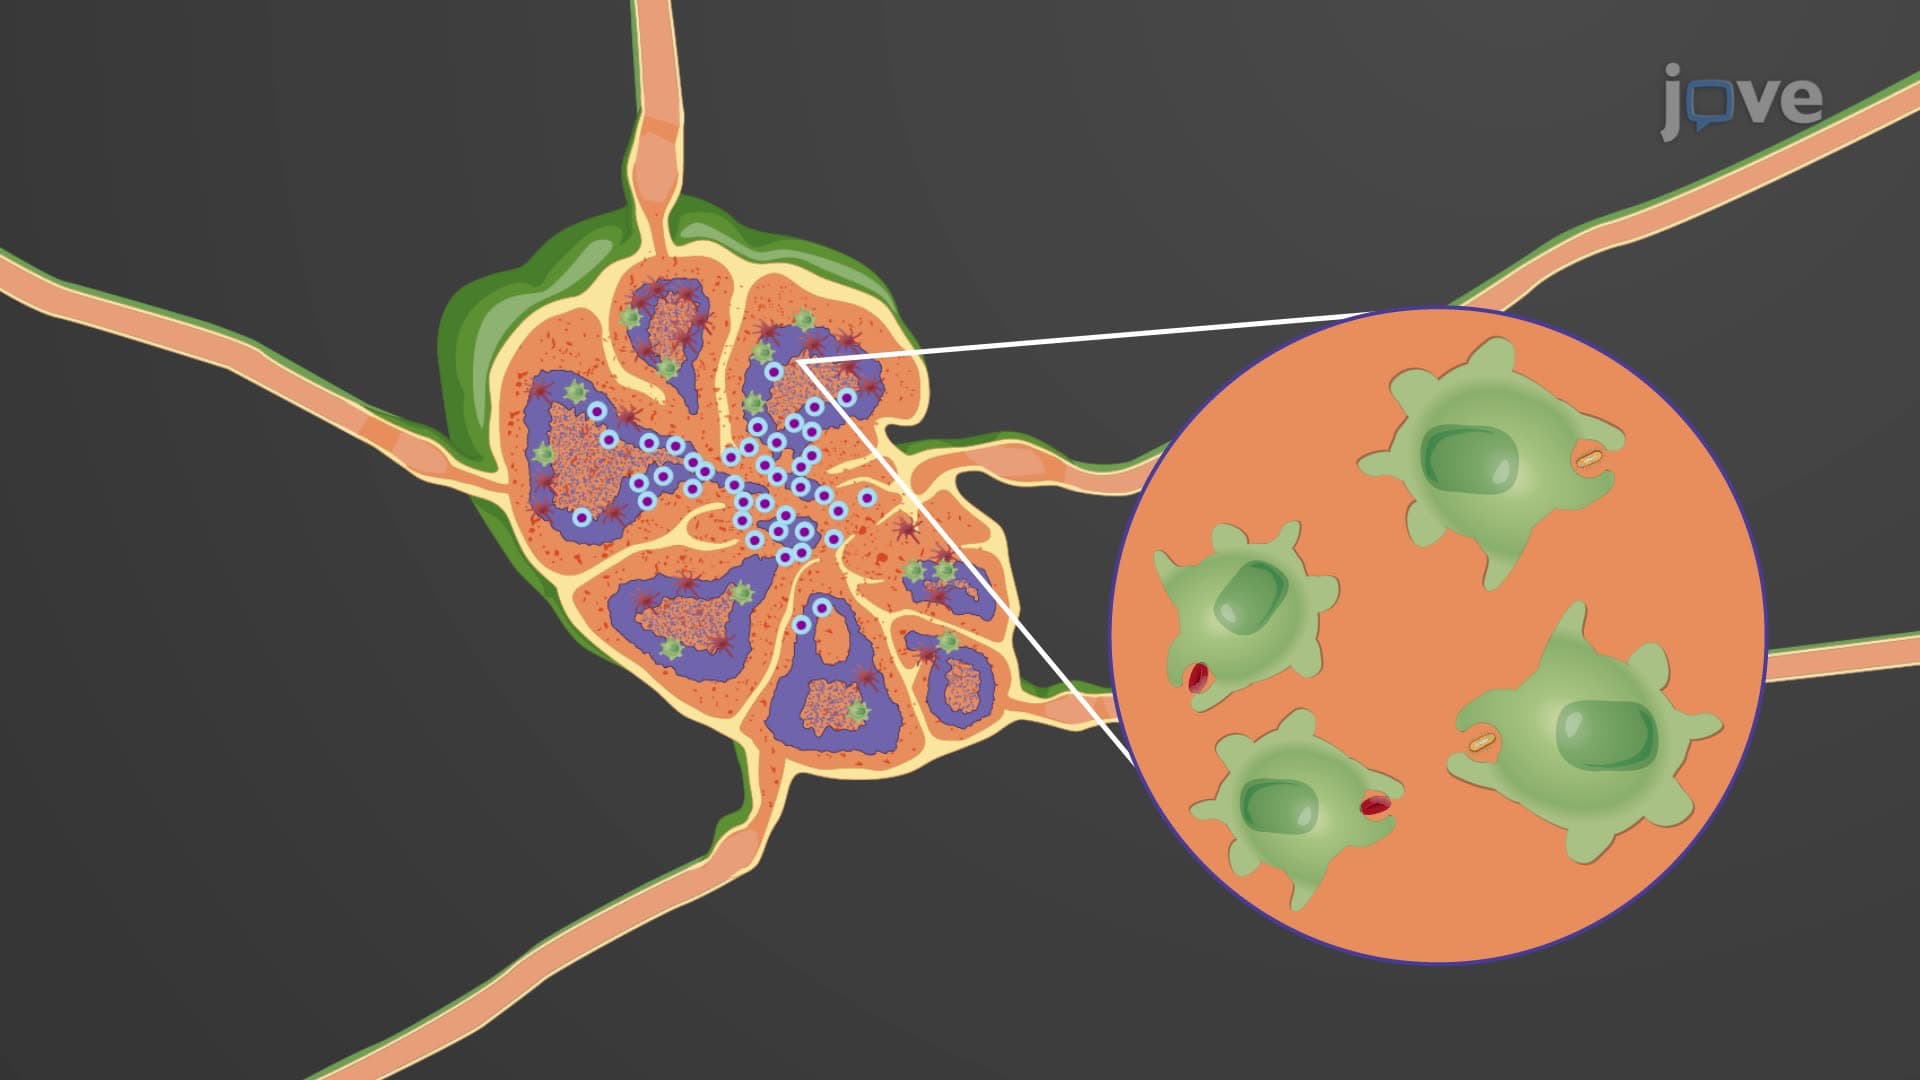 01:15
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...