Related Experiment Video
Updated: Jul 14, 2026
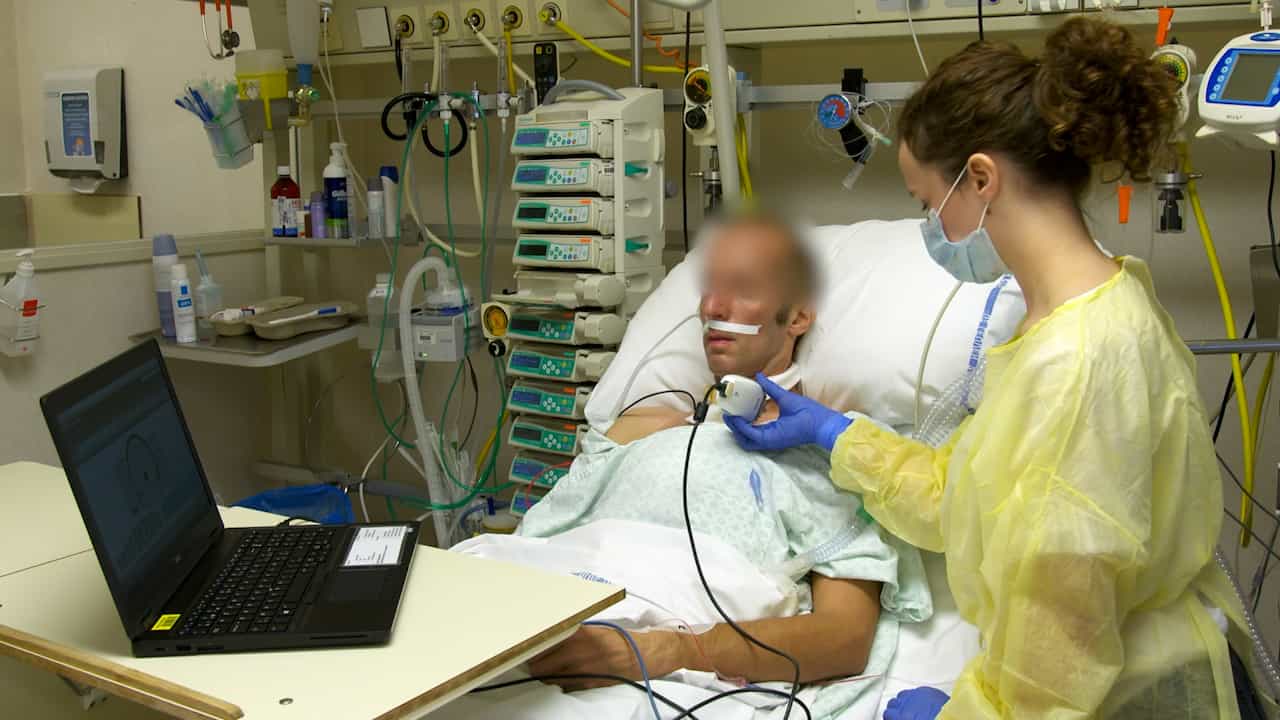

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Myasthenic crisis: guidelines for prevention and treatment
Agnes Jani-Acsadi1, Robert P Lisak
1Department of Neurology, Wayne State University, Detroit, MI, USA.

Management of myasthenic crisis (MC) requires admission of the patient into a neurological intensive care unit and timely institution of an efficient and safe treatment. Despite the growing clinical experience with disease modifying immunotherapy there is no clinical consensus regarding the use of plasma exchange or high dose immunoglobulin treatment in an ICU setting. The choice of treatment modalities seem to rely mostly on institutional preferences primarily due to a lack of well-designed clinical trials comparing currently available therapeutic options. In our experience and based on a review of recent literature we advocate the use of plasma exchange (PE) as a primary modality in the acute care setting, supported by other immunomodulatory medications such as corticosteroids. Pharmacological management cannot substitute for adequate intensive care management of the respiratory and bulbar insufficiency associated with MC. Every effort should be done to prevent myasthenic exacerbation/crisis and to develop a maintenance management that leads to effective prevention.
Management of myasthenic crisis (MC) requires admission of the patient into a neurological intensive care unit and timely institution of an efficient and safe treatment. Despite the growing clinical experience with disease modifying immunotherapy there is no clinical consensus regarding the use of plasma exchange or high dose immunoglobulin treatment in an ICU setting. The choice of treatment modalities seem to rely mostly on institutional preferences primarily due to a lack of well-designed clinical trials comparing currently available therapeutic options. In our experience and based on a review of recent literature we advocate the use of plasma exchange (PE) as a primary modality in the acute care setting, supported by other immunomodulatory medications such as corticosteroids. Pharmacological management cannot substitute for adequate intensive care management of the respiratory and bulbar insufficiency associated with MC. Every effort should be done to prevent myasthenic exacerbation/crisis and to develop a maintenance management that leads to effective prevention.
Related Concept Videos
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which leads...
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:22
Myocarditis IV: Nursing Management
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:28
Acute Coronary Syndrome IV: Interprofessional Care