Related Experiment Video
Updated: Jul 14, 2026
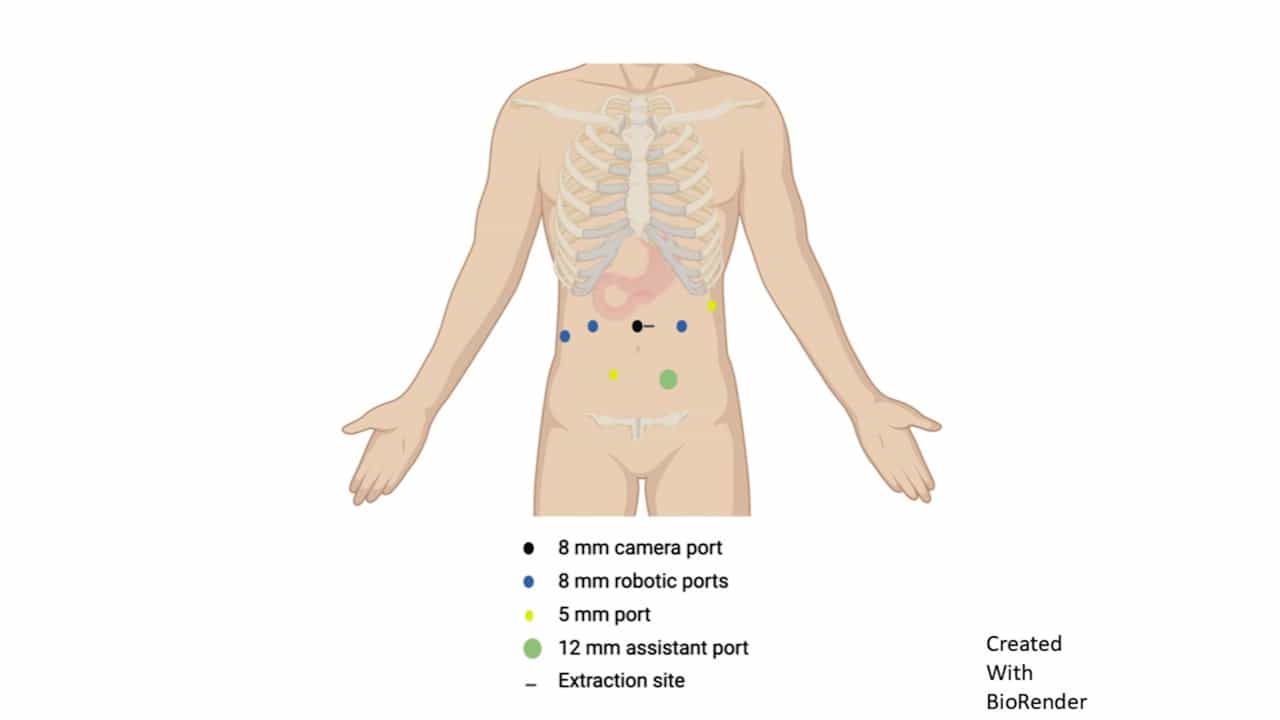

Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Second line therapies for the treatment of gastrointestinal stromal tumor
1Department of Oncology, Helsinki University Central Hospital, Helsinki, Finland. heikki.joensuu@hus.fi

Purpose Of Review:
Most gastrointestinal stromal tumors eventually acquire resistance to imatinib mesylate. This review focuses on recent progress on management of patients whose disease progresses on the standard dose of imatinib.
Recent Findings:
Approximately 30% of patients failing standard-dose imatinib achieve disease stabilization with high-dose imatinib, but objective responses are few and the clinical benefit usually short-lived. Patients receiving enzyme-inducing drugs may need high imatinib doses to achieve therapeutic blood concentrations. Surgical excision of a single growing metastasis leads to a median progression-free survival time of 7-11 months. Sunitinib malate is effective following imatinib failure. The median time to disease progression is approximately 6 months with sunitinib therapy versus 6 weeks with placebo following discontinuation of imatinib, but few (5%) patients achieve objective response. Patients with gastrointestinal stromal tumor with KIT exon 9 mutation may benefit more from sunitinib than those with exon 11 mutation. Sunitinib frequently causes abnormal thyroid function.
Summary:
Sunitinib is now the approved second line therapy following imatinib failure and for patients intolerant to imatinib. The clinical benefit is only moderate, and thyroid function monitoring is required. Several investigational agents are being evaluated for imatinib-resistant gastrointestinal stromal tumor. Palliative procedures, such as hepatic arterial embolization, also require study.
Insights
Most gastrointestinal stromal tumors (GIST) develop imatinib resistance. High-dose imatinib offers limited benefit, while sunitinib is approved for second-line therapy, requiring thyroid monitoring.
Area of Science:
- Gastroenterology
- Oncology
- Pharmacology
Background:
- Gastrointestinal stromal tumors (GIST) frequently develop resistance to imatinib mesylate, the standard first-line therapy.
- Management of imatinib-resistant GIST is a significant clinical challenge.
Purpose of the Study:
- To review recent advancements in managing patients with GIST whose disease progresses on standard-dose imatinib.
- To evaluate treatment options for imatinib-resistant GIST.
Main Methods:
- Review of current literature on imatinib resistance in GIST.
- Analysis of clinical trial data for second-line therapies.
- Evaluation of palliative procedures for advanced GIST.
Main Results:
- High-dose imatinib provides stabilization in ~30% of patients, but responses are often transient.
- Surgical excision of metastases offers temporary progression-free survival.
- Sunitinib malate is an effective second-line treatment, showing improved progression-free survival compared to placebo, though objective responses are infrequent.
- Patients with KIT exon 9 mutations may respond better to sunitinib than those with exon 11 mutations.
- Sunitinib use is associated with frequent thyroid dysfunction.
Conclusions:
- Sunitinib is the approved second-line therapy for imatinib-resistant or intolerant GIST, offering moderate clinical benefit.
- Thyroid function monitoring is essential during sunitinib treatment.
- Investigational agents and palliative procedures like hepatic arterial embolization require further study for imatinib-resistant GIST.

Related Concept Videos
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against specific...
 01:15
Drugs that Stabilize Microtubules