Related Experiment Video
Updated: Jul 14, 2026
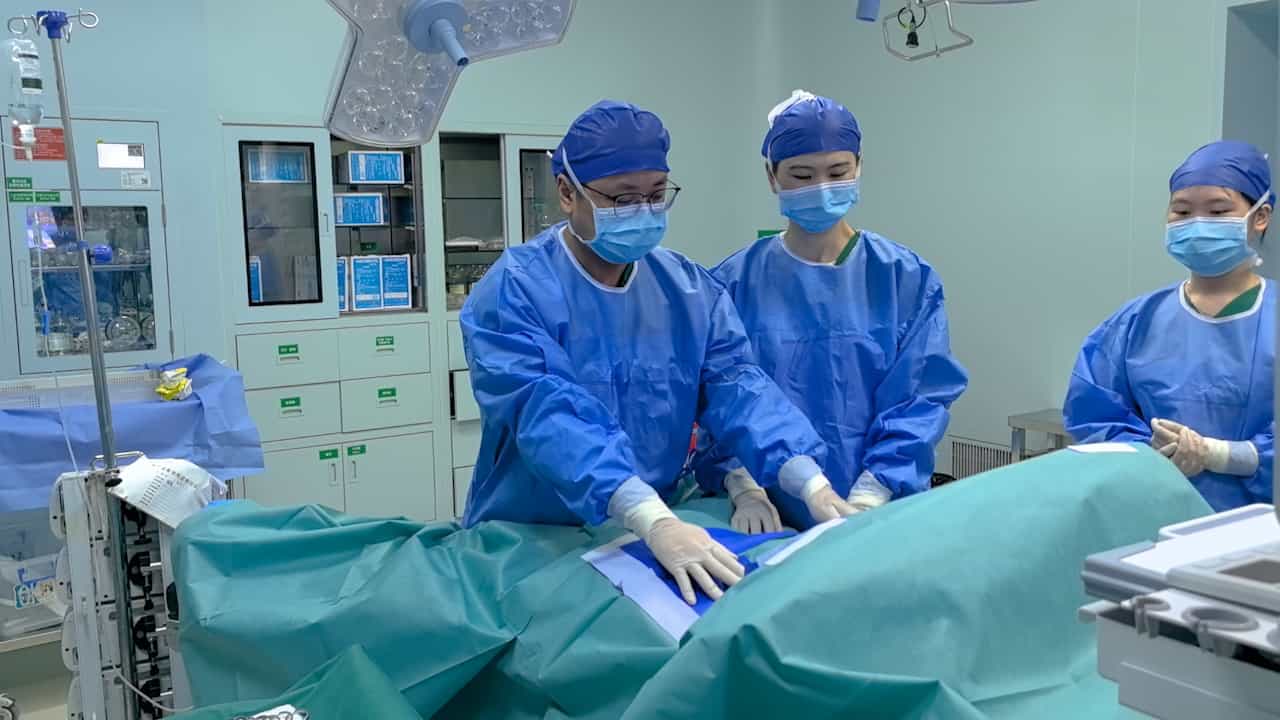

"Sun's Seven-Step Technique" for Endoscopic En-Bloc Resection of Thyroid Cancer via the Chest-Breast Approach
Published on: November 28, 2025
Neck management in medullary thyroid carcinoma
I M Oskam1, F Hoebers, A J M Balm
1Department of Head and Neck Oncology and Surgery, The Netherlands Cancer Institute/Antoni van Leeuwenhoek Hospital, Plesmanlaan 121, 1066 CX Amsterdam, The Netherlands. im.oskam@vumc.nl

Aims:
The aims of this study were to retrospectively evaluate incidence and patterns of lymph node metastases, surgical treatment and prognostic factors of medullary thyroid carcinoma.
Methods:
Out of a group of 70 MTC patients data of 67 patients were collected. Sixty-two of these patients underwent surgery. Apart from thyroidectomy, 16 patients underwent a bilateral neck dissection, 21 a unilateral neck dissection and 29 a paratracheal dissection or node-picking operation. Thirty-six patients were irradiated, of which 31 postoperatively and five with palliative intent.
Results:
Lymph node metastases were found in 91% of the ipsilateral neck dissection specimens, 91% of the paratracheal dissections and 63% of the contralateral dissections. Of the 12 elective neck dissections, 5 were tumor positive. Level VI was positive in 91% of the cases where a dissection was done, whereas preoperatively only 16% were scored tumor positive. During follow-up 22 of the 67 patients developed one or more locoregional recurrences (in total 28 recurrences). The most important factors that were correlated with a worse prognosis of survival were late stage of disease (stage III and IV) (p=0.0014), high number of positive lymph nodes (p=0.0023) and incomplete surgical resection (p=0.0002).
Conclusions:
The high rate of locoregional recurrences in this study are a strong argument for a more aggressive approach to the primary and neck. A routine central and ipsilateral selective neck dissection of levels II-V should be considered in all MTC patients based on the high incidence of metastases and the relative low morbidity of a unilateral neck dissection. Patients referred after thyroidectomy alone with elevated (stimulated) calcitonin levels should be re-operated, performing an elective or therapeutic central and unilateral neck dissection.
Related Concept Videos
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:27
Hyperthyroidism II: Pathophysiology
 01:27
Goiter
 01:24
Graves Disease II: Pathophysiology
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:25
Hyperthyroidism I: Introduction