Risk factors for recurrent venous thromboembolism in the European collaborative paediatric database on cerebral venous thrombosis: a multicentre cohort study
Related Experiment Video
Updated: Jul 14, 2026
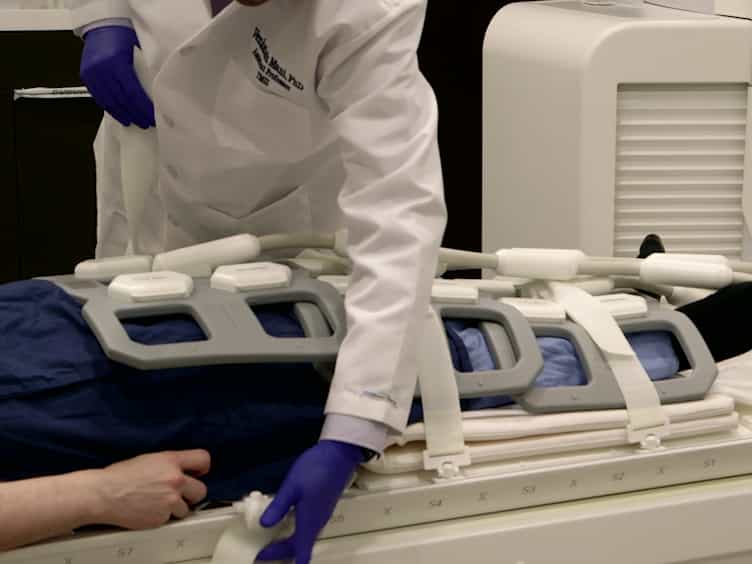
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Gili Kenet1, Fenella Kirkham, Thomas Niederstadt
1Israel National Haemophilia Centre, Sheba Medical Centre, Tel-Hashomer, Israel.

Insights
Recurrent cerebral venous thrombosis (CVT) in children is predicted by age at onset, lack of anticoagulation, persistent occlusion, and the G20210A mutation. Prophylactic anticoagulation should be individualized for high-risk pediatric CVT patients.
Area of Science:
- Pediatric Neurology
- Hematology
- Vascular Medicine
Background:
- Cerebral venous thrombosis (CVT) risk factors in children require further elucidation.
- The predictive value of prior diagnosis and hereditary prothrombotic factors for recurrent venous thrombosis (VT) in pediatric CVT survivors is unknown.
Purpose of the Study:
- To identify predictors of recurrent cerebral or systemic venous thrombosis (VT) in pediatric CVT survivors.
- To compare the importance of various clinical, neuroimaging, and treatment variables in predicting recurrent VT.
Main Methods:
- A longitudinal follow-up study of 396 pediatric CVT survivors (median age 5.2 years) for a median of 36 months.
- Analysis of acute and secondary anticoagulation treatment regimens.
- Cox regression analysis to identify independent predictors of recurrent VT.
Main Results:
- 22 (6%) children experienced recurrent VT, with 13 (3%) having cerebral VT.
- Recurrent VT occurred only in children diagnosed with CVT after age 2.
- Independent predictors of recurrent VT included non-administration of anticoagulation before relapse (HR 11.2), persistent venous occlusion on imaging (HR 4.1), and Factor II G20210A mutation heterozygosity (HR 4.3).
Conclusions:
- Age at CVT onset, non-administration of anticoagulation, persistent venous occlusion, and the Factor II G20210A mutation predict recurrent VT in children.
- Individualized secondary prophylactic anticoagulation is recommended for high-risk pediatric CVT patients.
- Further research is needed on factors influencing recanalisation after CVT.
Background:
The relative importance of previous diagnosis and hereditary prothrombotic risk factors for cerebral venous thrombosis (CVT) in children in determining risk of a second cerebral or systemic venous thrombosis (VT), compared with other clinical, neuroimaging, and treatment variables, is unknown.
Methods:
We followed up the survivors of 396 consecutively enrolled patients with CVT, aged newborn to 18 years (median 5.2 years) for a median of 36 months (maximum 85 months). In accordance with international treatment guidelines, 250 children (65%) received acute anticoagulation with unfractionated heparin or low-molecular weight heparin, followed by secondary anticoagulation prophylaxis with low-molecular weight heparin or warfarin in 165 (43%).
Results:
Of 396 children enrolled, 12 died immediately and 22 (6%) had recurrent VT (13 cerebral; 3%) at a median of 6 months (range 0.1-85). Repeat venous imaging was available in 266 children. Recurrent VT only occurred in children whose first CVT was diagnosed after age 2 years; the underlying medical condition had no effect. In Cox regression analyses, non-administration of anticoagulant before relapse (hazard ratio [HR] 11.2 95% CI 3.4-37.0; p<0.0001), persistent occlusion on repeat venous imaging (4.1, 1.1-14.8; p=0.032), and heterozygosity for the G20210A mutation in factor II (4.3, 1.1-16.2; p=0.034) were independently associated with recurrent VT. Among patients who had recurrent VT, 70% (15) occurred within the 6 months after onset.
Conclusion:
Age at CVT onset, non-administration of anticoagulation, persistent venous occlusion, and presence of G20210A mutation in factor II predict recurrent VT in children. Secondary prophylactic anticoagulation should be given on a patient-to-patient basis in children with newly identified CVT and at high risk of recurrent VT. Factors that affect recanalisation need further research.
Related Concept Videos
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:19
Pulmonary Embolism I: Introduction
 01:26
Varicose Veins I: Introduction
 01:30
Venous Thrombosis IV: Nursing Management