Related Experiment Video
Updated: Jul 14, 2026


Permanent Ligation of the Left Anterior Descending Coronary Artery in Mice: A Model of Post-myocardial Infarction Remodelling and Heart Failure
Published on: December 2, 2014
Determinants of left ventricular thrombus formation after primary percutaneous coronary intervention for anterior
LeRoy Elazar Rabbani1, Carol Waksmonski, Sohah N Iqbal
1Division of Cardiology, Columbia University Medical Center, 161 Fort Washington Avenue, New York, NY 10032, USA. ler8@columbia.edu

Previous studies have reported that left ventricular (LV) thrombus is a complication in 10-56% of ST-segment elevation acute anterior wall myocardial infarctions (AWMI). Data suggest that changes in acute myocardial infarction management such as early anticoagulation, thrombolysis, and most recently, primary percutaneous coronary intervention (PCI), may decrease thrombus occurrence. Early time to reperfusion has been shown to decrease mortality and improve LV function recovery. To determine if door-to-balloon time (DTBT) affects the incidence of LV thrombus, we retrospectively analyzed data on 43 consecutive patients who underwent successful PCI of a primary acute ST-segment elevation AWMI. Transthoracic echocardiography was performed for detecting LV thrombus and measuring LV ejection fraction (EF) within 5 days on all patients (average time: 2.17 days post event). Nineteen patients underwent PCI within 2 h of arrival to the Emergency Department (Group A, average 88 min) and 24 patients underwent PCI with DTBT of more than 2 h (Group B, average 193 min). Clinically significant LV thrombus was detected in 35% of all patients. The incidence of LV thrombus formation in Group A was not significantly different from that in Group B (42.1% vs. 29.0%, respectively; P = 0.52). The risk of LV thrombus was independent of in-hospital anticoagulation and medical management, peak enzyme levels, and LVEF but did relate to age (odds ratio = 1.96, 95% CI 1.03-3.73, P = 0.04 per decade). No embolic events in hospital were observed (average hospital stay 9.2 days). We conclude that the incidence of LV thrombus remains high despite PCI. Also, we find that DTBT in patients presenting with an ST-segment elevation AWMI does not affect the incidence of LV thrombus formation. Increased age, however, does appear to increase the risk of LV thrombus development.
Previous studies have reported that left ventricular (LV) thrombus is a complication in 10-56% of ST-segment elevation acute anterior wall myocardial infarctions (AWMI). Data suggest that changes in acute myocardial infarction management such as early anticoagulation, thrombolysis, and most recently, primary percutaneous coronary intervention (PCI), may decrease thrombus occurrence. Early time to reperfusion has been shown to decrease mortality and improve LV function recovery. To determine if door-to-balloon time (DTBT) affects the incidence of LV thrombus, we retrospectively analyzed data on 43 consecutive patients who underwent successful PCI of a primary acute ST-segment elevation AWMI. Transthoracic echocardiography was performed for detecting LV thrombus and measuring LV ejection fraction (EF) within 5 days on all patients (average time: 2.17 days post event). Nineteen patients underwent PCI within 2 h of arrival to the Emergency Department (Group A, average 88 min) and 24 patients underwent PCI with DTBT of more than 2 h (Group B, average 193 min). Clinically significant LV thrombus was detected in 35% of all patients. The incidence of LV thrombus formation in Group A was not significantly different from that in Group B (42.1% vs. 29.0%, respectively; P = 0.52). The risk of LV thrombus was independent of in-hospital anticoagulation and medical management, peak enzyme levels, and LVEF but did relate to age (odds ratio = 1.96, 95% CI 1.03-3.73, P = 0.04 per decade). No embolic events in hospital were observed (average hospital stay 9.2 days). We conclude that the incidence of LV thrombus remains high despite PCI. Also, we find that DTBT in patients presenting with an ST-segment elevation AWMI does not affect the incidence of LV thrombus formation. Increased age, however, does appear to increase the risk of LV thrombus development.
Related Concept Videos
 01:30
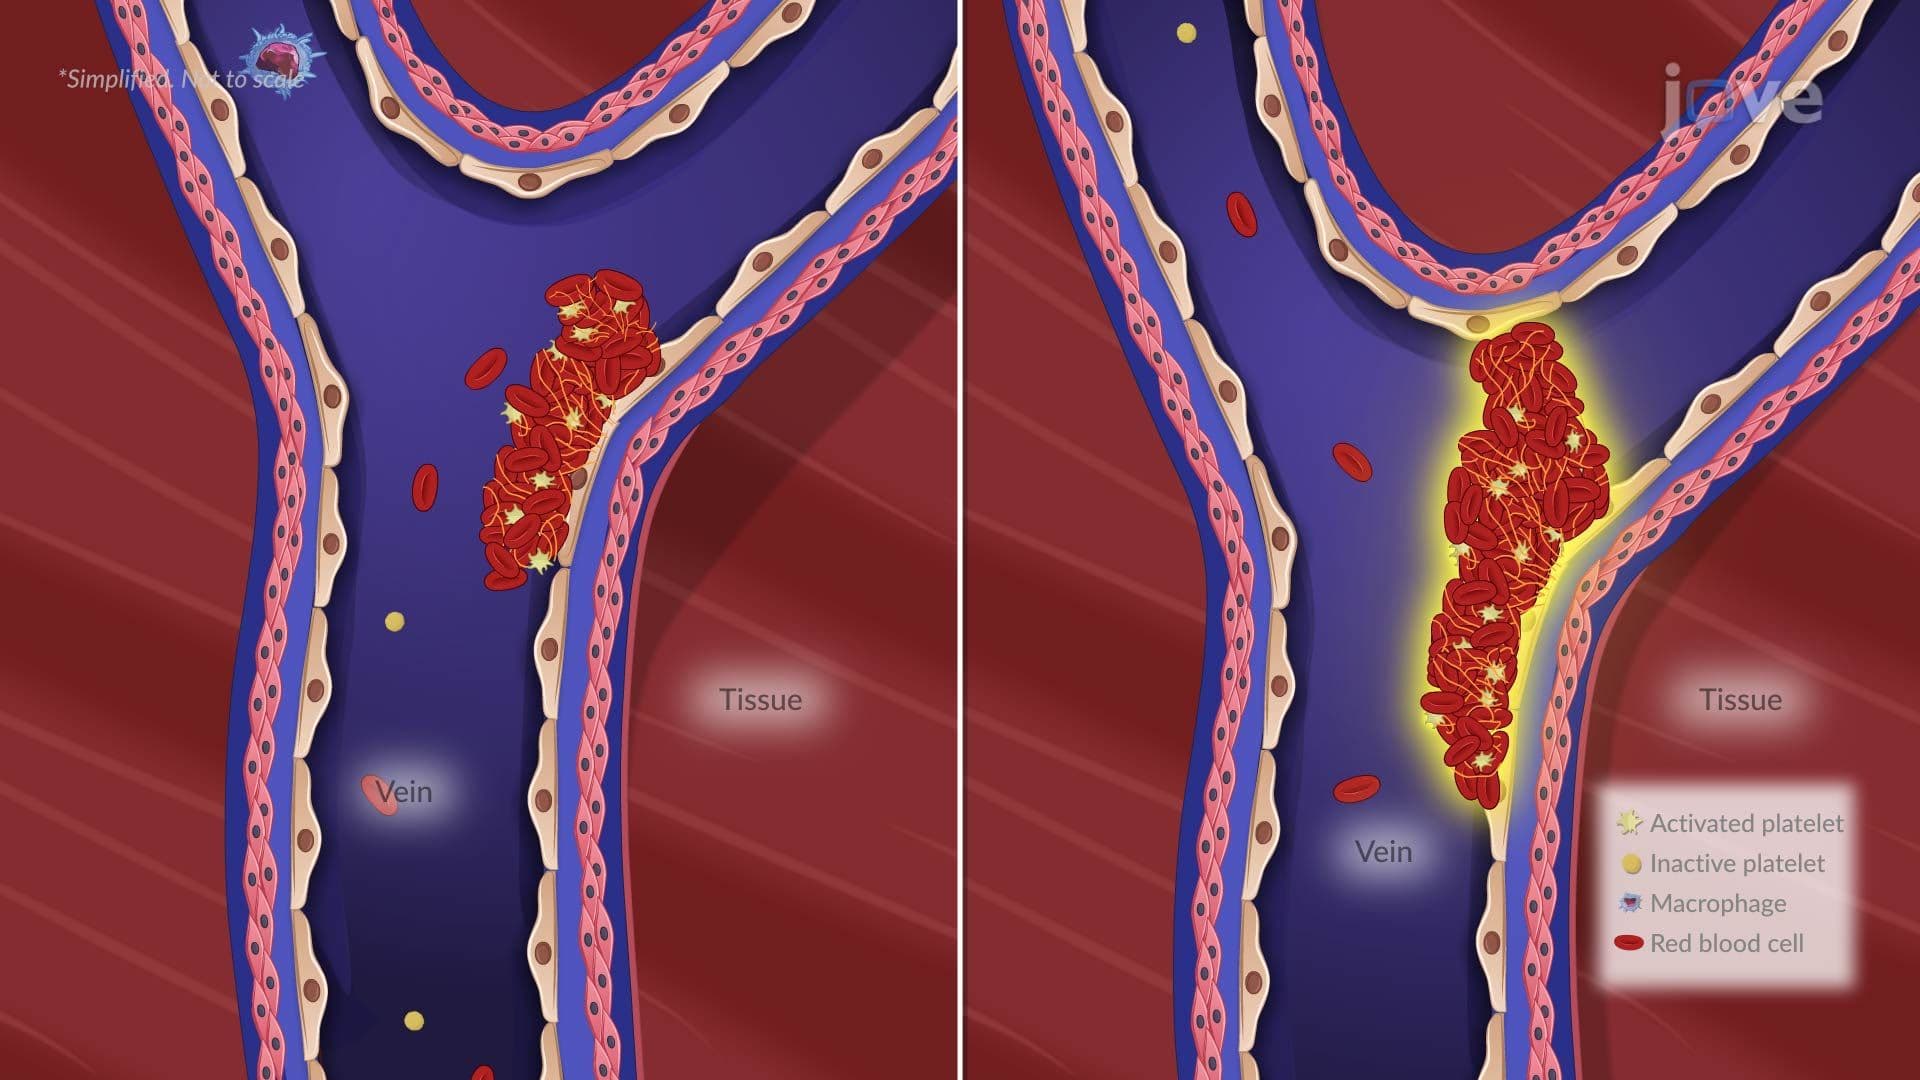
Venous Thrombosis I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:16
Clot Retraction and Fibrinolysis
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Pulmonary Embolism I: Introduction