Related Experiment Video
Updated: Aug 10, 2026

Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Domiciliary nocturnal nasal intermittent positive pressure ventilation in COPD: mechanisms underlying changes in
M W Elliott1, D A Mulvey, J Moxham
1Dept. of Thoracic Medicine, Royal Brompton and National Heart Hospital, London, UK.

Abstract:
The improvement in arterial blood gas tensions following assisted ventilation in chronic obstructive pulmonary disease (COPD) has usually been attributed to the relief of incipient or established respiratory muscle fatigue. The contribution of changes in the load placed upon and the drive to the respiratory muscle pump have not been evaluated. We have investigated the contribution of changes in respiratory muscle strength, the ventilatory response to CO2 and ventilatory function to changes in arterial blood gas tensions in eight patients with severe COPD completing six months domiciliary nasal intermittent positive pressure ventilation. Six patients showed a reduction and two an increase in arterial carbon dioxide tension (PaCO2), median (range) for eight patients, -0.9 kPa (-1.5 to +0.4) (p less than 0.05) and seven showed an improvement in arterial oxygen tension (PaO2), +0.7 kPa (-0.4 to +1.7) (p less than 0.05) during daytime spontaneous breathing. The reduction in PaCO2 was not related to increased inspiratory muscle strength but was correlated with a decrease in gas trapping (Spearman rank correlation coefficient (r(S)) 0.85, p less than 0.05) and in the residual volume (r(s) 0.78, p less than 0.05), suggesting reduced small airway obstruction and, therefore, a reduction in load. The change in PaCO2 also correlated with the increase in ventilation at an end-tidal CO2 of 8 kPa during rebreathing (r(s) -0.76, p less than 0.05) suggesting improved chemosensitivity to CO2. Our data do not support the hypothesis that improvements were due to the relief of muscle fatigue. We suggest that the contribution of changes in load and central drive warrant further investigation.
More Related Videos
 04:53
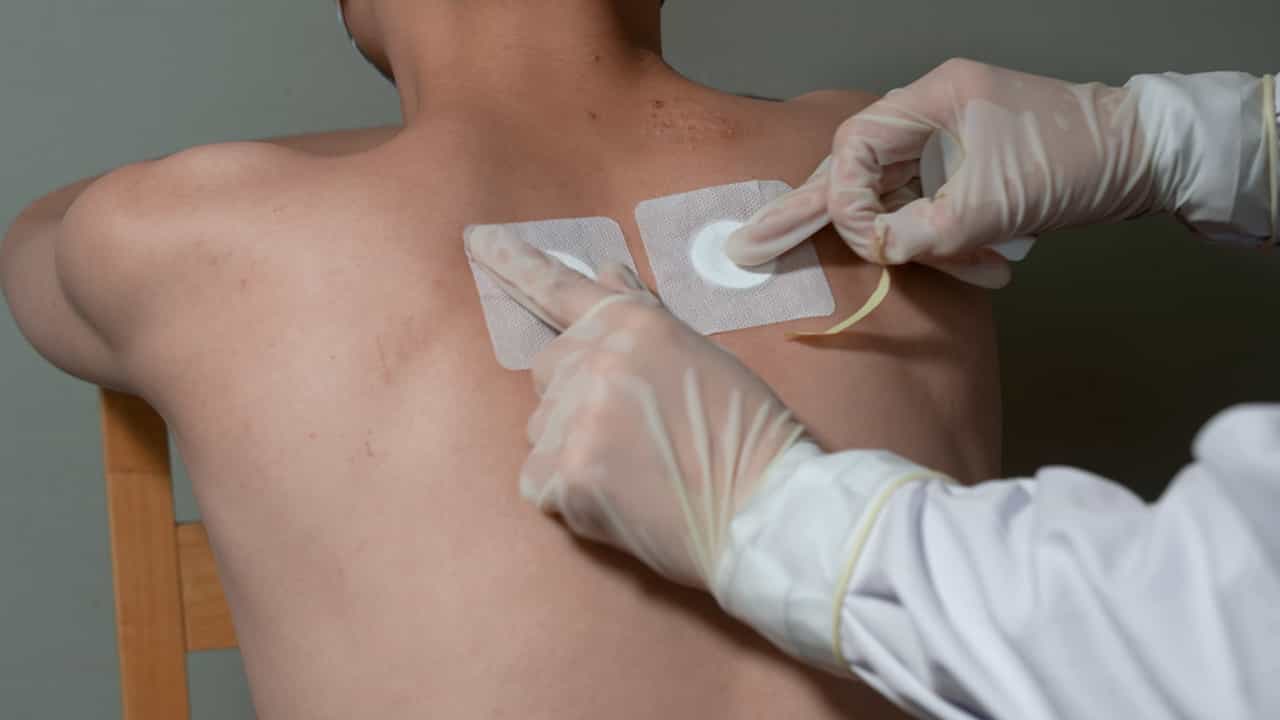
Acupoint Application Combined with Ear Plaster Therapy for Treating Sleep Disorders with Acute Exacerbation of Chronic Obstructive Pulmonary Disease
Published on: October 18, 2024
 07:15
Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
Related Concept Videos
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...