Related Experiment Video
Updated: Jul 14, 2026


Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
Mixed-expired and end-tidal CO2 distinguish between ventilation and perfusion defects during exercise testing in
James E Hansen1, Gaye Ulubay, Bing Fai Chow
1Los angeles Biomedical Research Institute, Harbor-UCLA Medical Center, 1000 W. Carson St, RB-2, Box 405, Torrance CA 90509, USA. jhansen@labiomed.org

Background:
Mismatching of ventilation to perfusion is found in patients with COPD, left ventricular failure (LVF), and pulmonary vascular diseases. Such mismatching may be due to ventilation or perfusion defects or both. Our primary hypothesis was that pressures of mixed-expired CO2 pressure (Peco(2)), end-tidal Pco(2) pressure (Petco(2)), and their ratios would differ between groups during exercise testing, depending on whether the ventilation/perfusion (V/Q) abnormality was dominantly caused by airways or perfusion defects.
Methods:
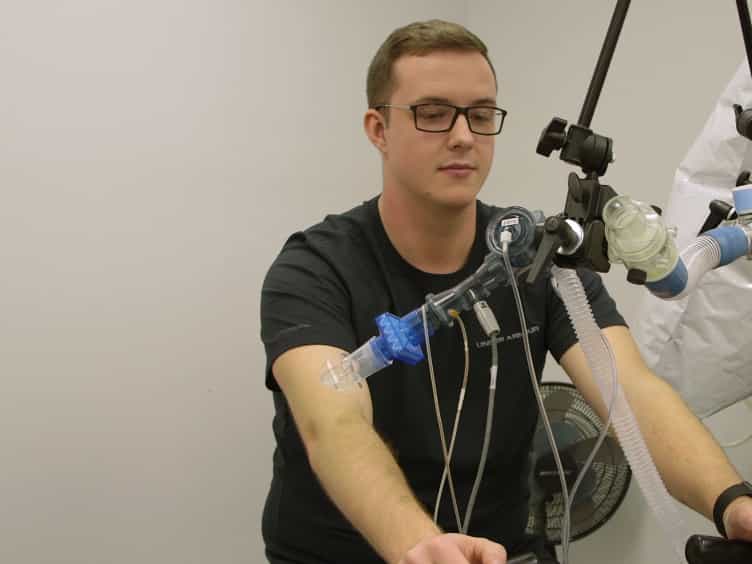
We administered incremental cycle ergometry tests to 25 normal subjects and three groups of 25 patients, each group with uncomplicated COPD, LVF, or primary pulmonary arterial hypertension (PAH). We compared Peco(2), Petco(2), and their ratios at rest, unloaded pedaling, anaerobic threshold, and peak exercise.
Results:
Although each patient group had mean peak O(2) uptake of approximately 50% of predicted normal, the levels and patterns of change for each group for Peco(2), Petco(2), and their ratios were surprisingly distinctive. As hypothesized, the COPD group always had markedly lower Peco(2)/Petco(2) ratios than all other groups (p < 0.001). In addition, patients with LVF had slightly lower Peco(2)/Petco(2) ratios at heavy exercise than normal subjects (p < 0.05). At all times, except for COPD group Petco(2) at peak exercise, each group had significantly lower Petco(2) and Peco(2) than normal subjects (p < 0.001). In patients with PAH, the Petco(2) decline with exercise was distinctive.
Conclusions:
The levels and changes in Peco(2), Petco(2), and their ratios during cardiopulmonary exercise testing are distinctive and explained by the differing pathophysiologies of V/Q mismatching in these disorders.
More Related Videos
 08:44
Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:10
Atelectasis II: Pathophysiology
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:20
Respiration and Gaseous Exchange
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: