Related Experiment Video
Updated: Jul 14, 2026

Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
Regional lung volume changes in children with acute respiratory distress syndrome during a derecruitment maneuver
Gerhard K Wolf1, Bartlomiej Grychtol, Inez Frerichs
1Division of Critical Care Medicine, Department of Anesthesia, Children's Hospital Boston, Harvard Medical School, Boston, MA, USA. gerhard.wolf@childrens.harvard.edu

Insights
Children with acute respiratory distress syndrome (ARDS) experience significant lung collapse during mechanical ventilation, especially in dependent regions. Electrical impedance tomography (EIT) can quantify this lung volume loss during suctioning maneuvers.
Area of Science:
- Pediatric critical care medicine
- Respiratory physiology
- Medical imaging techniques
Background:
- Regional differences in lung volume are known in adult ARDS.
- Limited data exists on regional lung changes in pediatric ARDS.
- Mechanical ventilation and suctioning can impact lung volume.
Purpose of the Study:
- To quantify regional alveolar collapse during mechanical ventilation in children with ARDS.
- To assess lung volume changes during a standardized suctioning maneuver using EIT.
- To investigate regional impedance changes in pediatric ARDS patients.
Main Methods:
- Prospective observational trial in a pediatric intensive care unit.
- Six children with acute respiratory distress syndrome were included.
- Electrical impedance tomography (EIT) was used to measure relative impedance changes (relative DeltaZ).
- A standardized suctioning maneuver was performed.
Main Results:
- Significant regional heterogeneity in lung ventilation was observed.
- Dependent lung regions (layer 4) showed the least ventilation-induced change in relative DeltaZ.
- Suctioning caused negative changes in relative DeltaZ in nondependent and middle lung regions, indicating lung-volume loss.
- Lung-volume loss increased with repeated suctioning maneuvers.
- Mechanical ventilation's effect on relative DeltaZ and dynamic compliance remained unchanged after suctioning.
Conclusions:
- Considerable regional heterogeneity in lung volume occurs in pediatric ARDS during ventilation and suctioning.
- Alveolar collapse in dependent lung regions is suggested by reduced impedance changes.
- EIT is a valuable tool for monitoring regional lung changes in pediatric ARDS.
Objective:
Regional differences in lung volume have been described in adults with acute respiratory distress syndrome, but it remains unclear to what extent they occur in children. To quantify regional alveolar collapse that occurred during mechanical ventilation during a standardized suctioning maneuver, we evaluated regional and global relative impedance changes (relative DeltaZ) in children with acute respiratory distress syndrome using electrical impedance tomography.
Design:
Prospective observational trial.
Setting:
A 30-bed pediatric intensive care unit.
Patients:
Six children with acute respiratory distress syndrome.
Interventions:
Standardized suctioning maneuver.
Measurements And Main Results:
By comparing layers from nondependent (layers 1 and 2) to dependent lung areas (layers 3 and 4), it was demonstrated that the middle layers (2 and 3) had the greatest ventilation-induced change in relative DeltaZ; layer 4 showed the least ventilation-induced change in relative DeltaZ. During suctioning, layers 1, 2, and 3 showed a negative change in relative DeltaZ, whereas layer 4 showed no significant change in relative DeltaZ. The derecruitment-induced change in relative DeltaZ representing the lung-volume loss was -9.8 (-3.0 mL/kg) during the first suctioning maneuver, -16.1 (-5.4 mL/kg) during the second, and -21.7 (-7.4 mL/kg) during the third. The ventilation-induced change in relative DeltaZ during mechanical ventilation remained unchanged after suctioning (mean change in relative DeltaZ before vs. after suctioning, 40.1 +/- 9.1 vs. 41.4 +/- 10.8; p = .30). Dynamic compliance was 11.8 +/- 6.1 mL.cm H2O before and 11.8 +/- 6.9 mL.cm H2O after the suctioning sequence (p = .90).
Conclusions:
Considerable regional heterogeneity was present during ventilation and a derecruitment maneuver. Significantly lower change in relative DeltaZ in the most dependent lung regions suggests alveolar collapse during ventilation before suctioning.

Related Concept Videos
 01:15
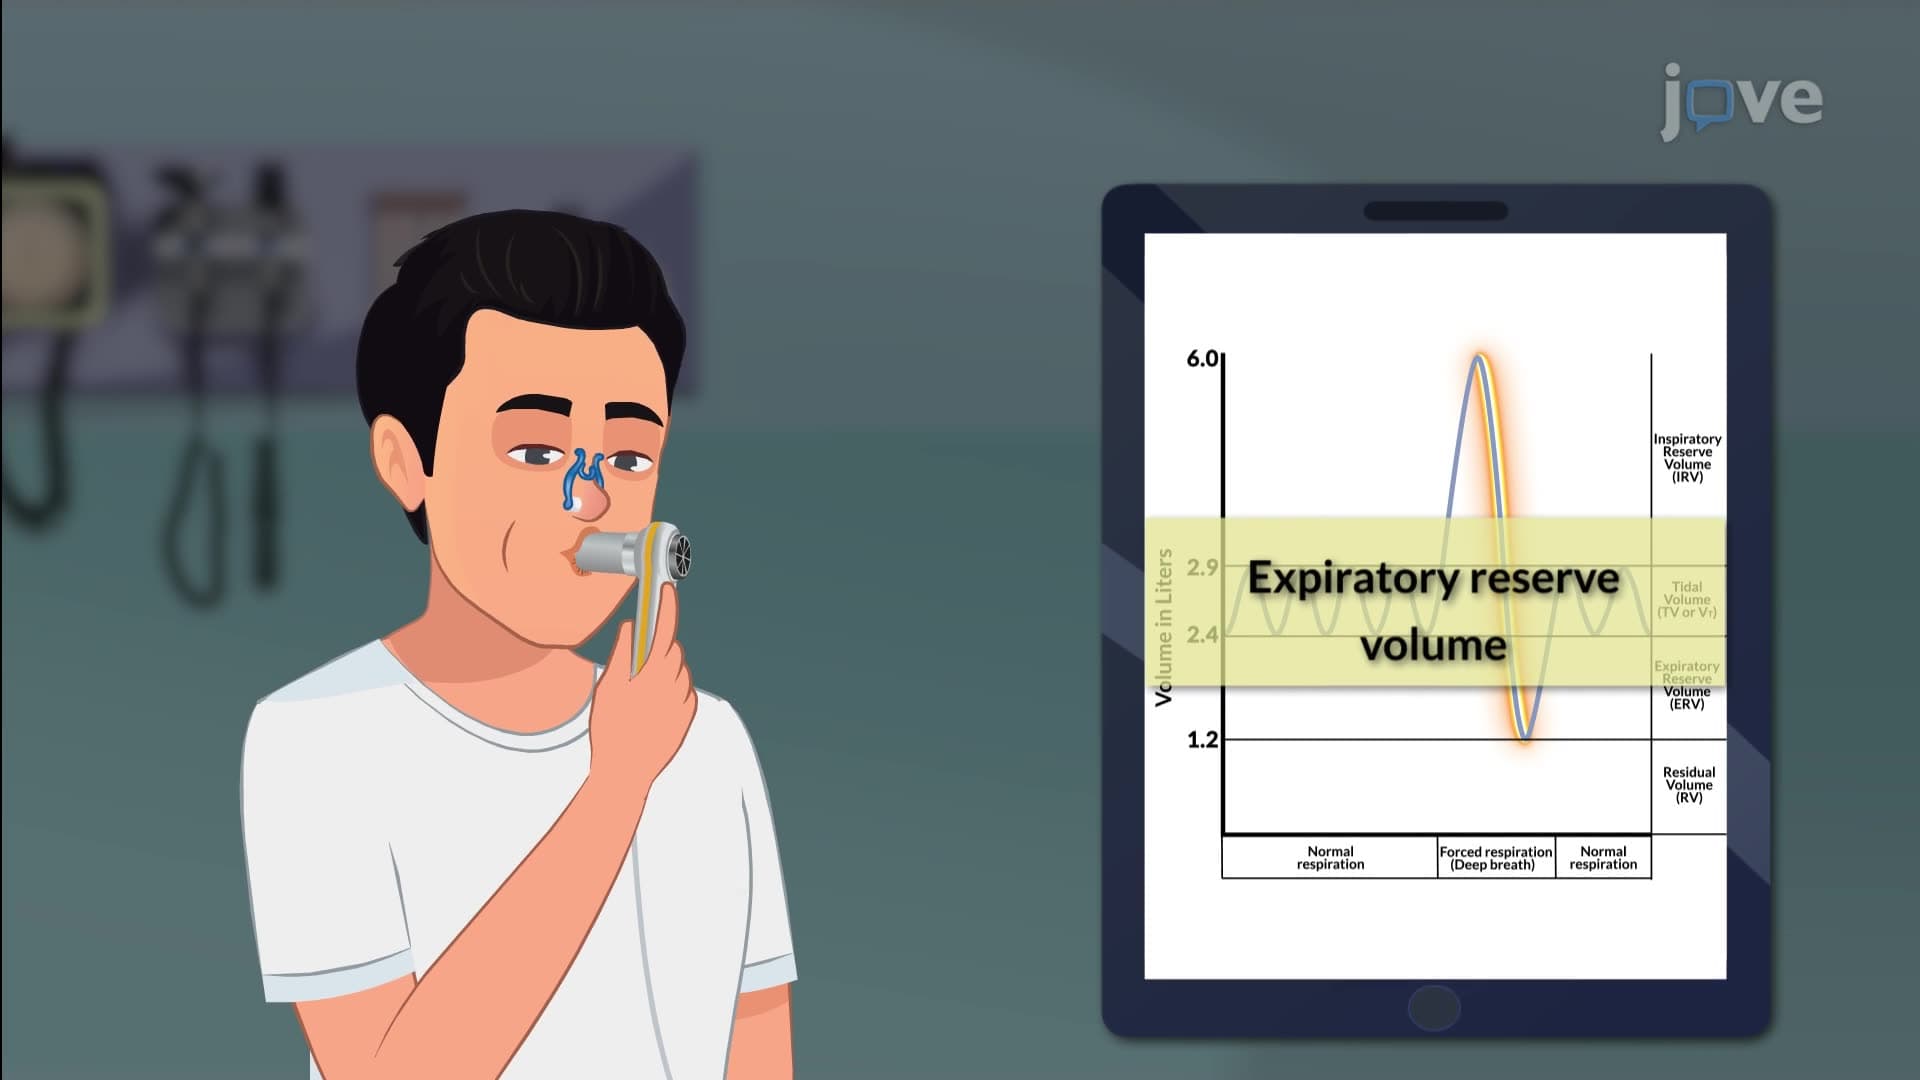
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:17
Pulmonary Cycle: Exhalation
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:26
Respiratory Volumes and Capacities I
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...