Related Experiment Video
Updated: Jul 14, 2026

Modeling Cataract Surgery in Mice
Published on: December 1, 2023
[Surgical treatment of congenital cataracts]
1Klinik für Augenheilkunde, Johann Wolfgang Goethe-Universität, Theodor-Stern-Kai 7, 60590 Frankfurt am Main, Deutschland. Kohnen@em.uni-frankfurt.de

Insights
Pediatric cataract surgery presents unique challenges due to smaller eye anatomy. Advanced techniques and careful intraocular lens (IOL) selection are crucial for optimal visual outcomes in children.
Area of Science:
- Ophthalmology
- Pediatric Surgery
Context:
- Paediatric cataract surgery requires specialized approaches due to unique anatomical and tissue properties in young patients.
- The higher incidence of secondary cataracts necessitates complex surgical strategies and lens implantation techniques.
Purpose:
- To outline the challenges and current surgical strategies for paediatric cataract removal.
- To discuss intraocular lens (IOL) selection and management in infant and child cataract surgery.
Summary:
- Surgery involves limbal or pars plana approaches, addressing challenges like secondary cataract formation.
- Intraocular lens (IOL) implantation is timed after 18 months, with power adjusted for expected axial growth.
- Management includes anti-inflammatory and antibiotic therapies, alongside critical orthoptic follow-up.
Impact:
- Highlights the specialized nature of paediatric cataract surgery.
- Emphasizes the importance of tailored surgical and optical correction for long-term visual development in children.
Abstract:
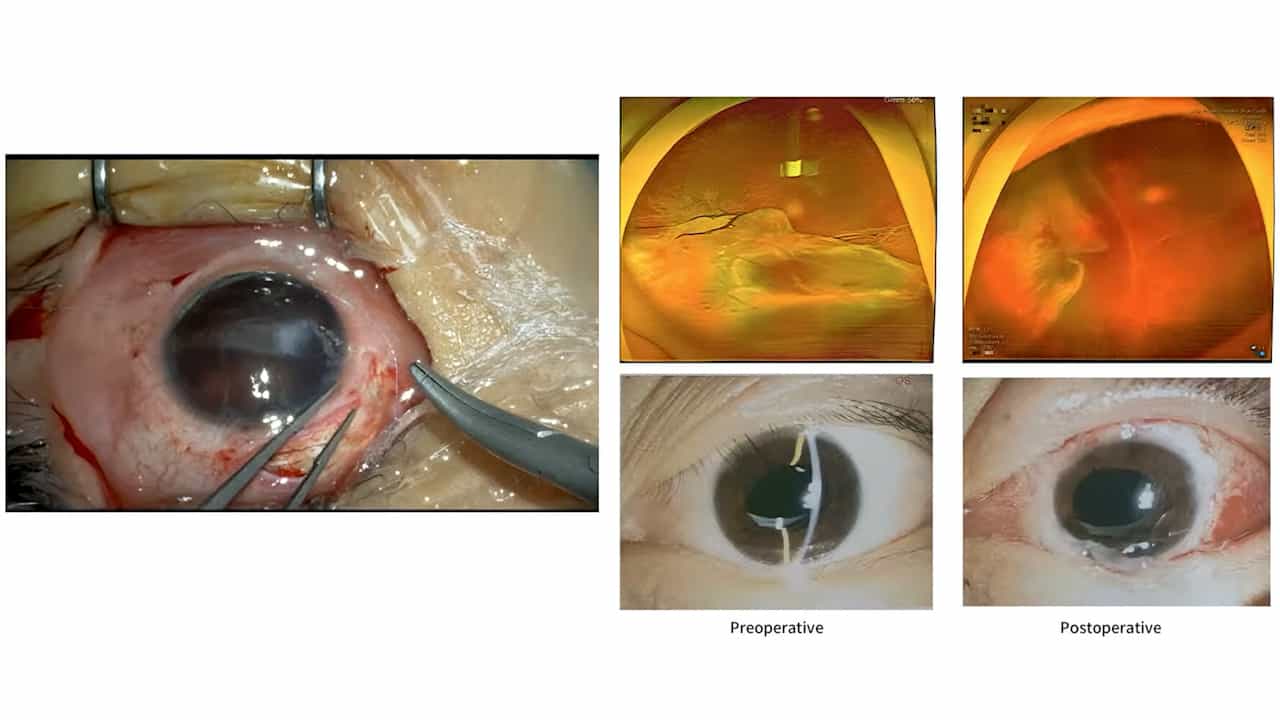
Due to the anatomical dimensions being smaller and the tissue structures being softer and more elastic in the young patient, surgery of paediatric cataracts represents a special challenge for the ophthalmic surgeon. Surgery is performed via a limbal or pars plana approach. The extreme high rate of secondary cataract formation in the paediatric or adolescent eye with closed posterior capsules is countered by means of complicated capsular surgery, special intraocular lens (IOL) implantation techniques, and vitreoretinal surgical procedures. It is customary not to implant IOLs before the children are 1-2 years old as increased axial length growth must be expected during the first 18 months after birth. IOL power is selected so that postoperative refraction is within the hyperopic range and with time, undercorrection will be balanced by bulbus growth. Preoperative and postoperative therapy is highly dependant on the extent of trauma sustained during surgery and should contain anti-inflammatory medication with and without steroids as well as antibiotics. Orthoptic follow-up examinations are also decisive for the long-term result.
Related Concept Videos
 01:28
Angle Closure Glaucoma: Treatment
 01:27
Open Angle Glaucoma: Treatment
Drugs such as carbonic anhydrase inhibitors, α2- and...