Related Experiment Video
Updated: Jul 14, 2026


Voluntary Breath-hold Technique for Reducing Heart Dose in Left Breast Radiotherapy
Published on: July 3, 2014
Intra- and interfraction breathing variations during curative radiotherapy for lung cancer
Trine Juhler Nøttrup1, Stine Sofia Korreman, Anders Navrsted Pedersen
1Department of Radiation Oncology, Rigshospitalet, Copenhagen, Denmark. trine.juhler-noettrup@rh.regionh.dk

Background And Purpose:
This study aimed at quantifying the breathing variations among lung cancer patients over full courses of fractionated radiotherapy. The intention was to relate these variations to the margins assigned to lung tumours, to account for respiratory motion, in fractionated radiotherapy.
Materials And Methods:
Eleven lung cancer patients were included in the study. The patients' chest wall motions were monitored as a surrogate measure for breathing motion during each fraction of radiotherapy by use of an external optical marker. The exhale level variations were evaluated with respect to exhale points and fraction-baseline, defined for intra- and interfraction variations respectively. The breathing amplitude was evaluated as breathing cycle amplitudes and fraction-max-amplitudes defined for intra- and interfraction breathing, respectively.
Results:
The breathing variations over a full treatment course, including both intra- and interfraction variations, were 15.2mm (median over the patient population), range 5.5-26.7mm, with the variations in exhale level as the major contributing factor. The median interfraction span in exhale level was 14.8mm, whereas the median fraction-max-amplitude was 6.1mm (median of patient individual SD 1.4). The median intrafraction span in exhale level was 1.6mm, and the median breathing cycle amplitude was 4.0mm (median of patient individual SD 1.4).
Conclusions:
The variations in externally measured exhale levels are larger than variations in breathing amplitude. The interfraction variations in exhale level are in general are up to 10 times larger than intrafraction variations. Margins to account for respiratory motion cannot safely be based on one planning session, especially not if relying on measuring external marker motion. Margins for lung tumours should include interfraction variations in breathing.


Related Concept Videos
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
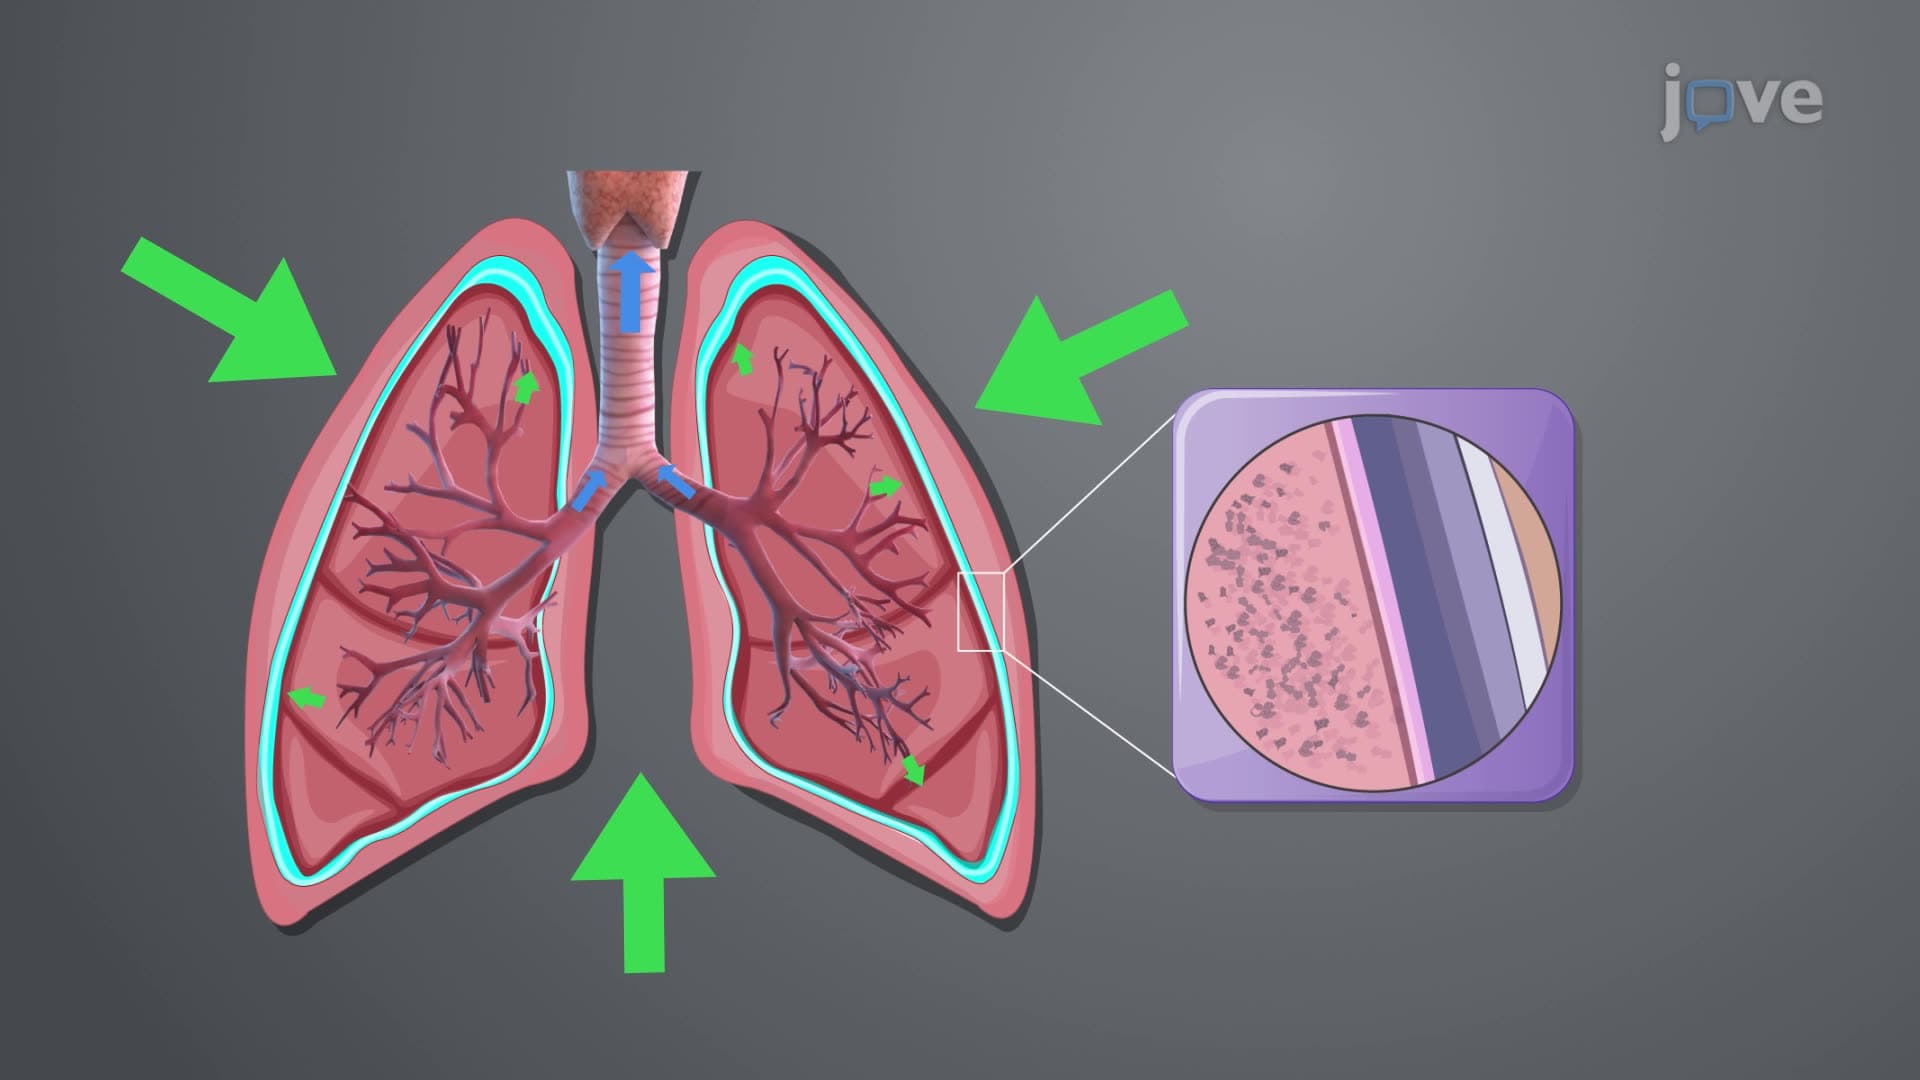
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:24
Pulmonary Ventilation: Inhalation
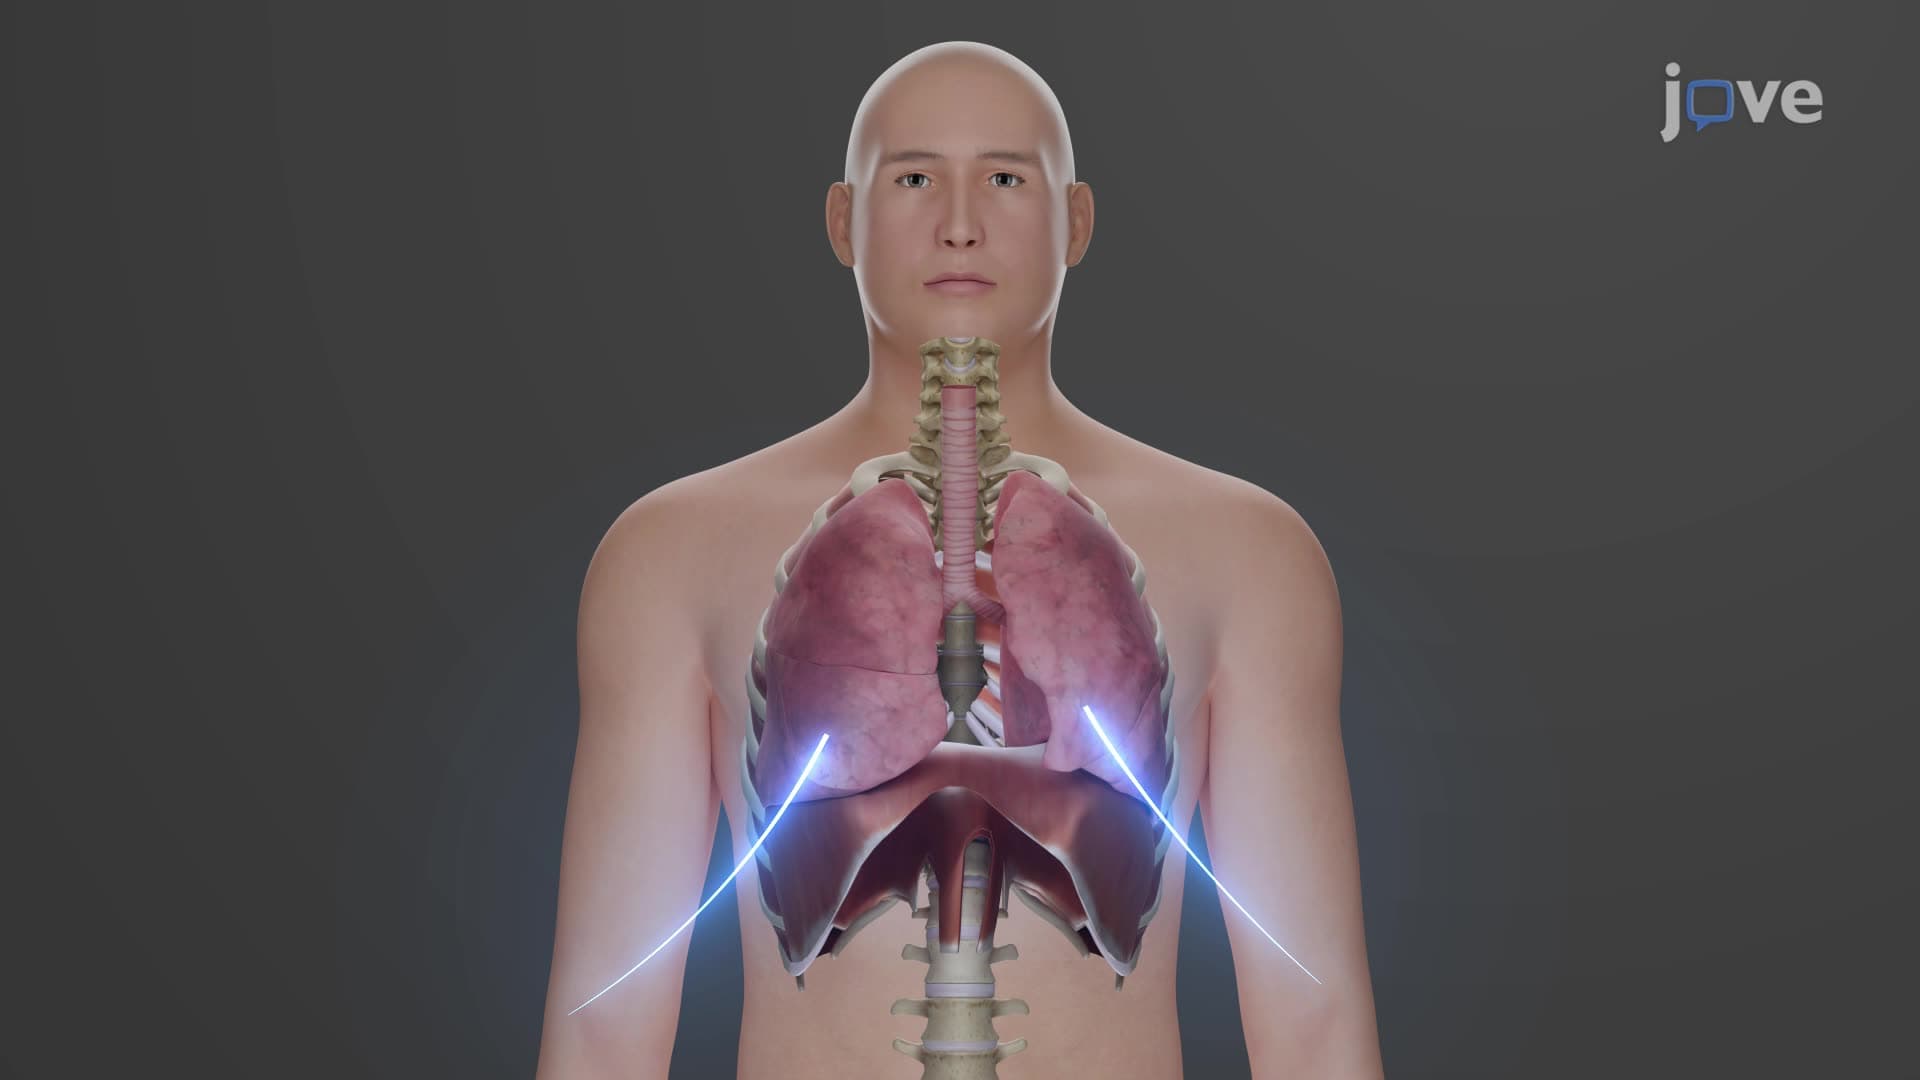
Boyle's law becomes particularly pertinent when examining respiratory...
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...
 01:13
Radiological Investigation III: Pulmonary Angiogram and PET Scan
Pulmonary Angiogram
A Pulmonary Angiogram is an invasive procedure involving injecting a contrast medium through a catheter threaded into the pulmonary artery or the right side of the heart to visualize the pulmonary vasculature. Computed Tomography (CT) scans have mainly replaced this...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...