Related Experiment Video
Updated: Jul 13, 2026


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Intracystic hemorrhage in a mediastinal cystic adenoma causing parathyrotoxic crisis
Andreas Manouras1, Konstantinos G Toutouzas, Haridimos Markogiannakis
1Department of Endocrine Surgery, First Department of Propaedeutic Surgery, Hippokration Hospital, University of Athens, Athens Medical School, Athens, Greece.

Background:
We report a case of intracystic hemorrhage in a mediastinal cystic parathyroid adenoma causing parathyrotoxic crisis.
Methods And Results:
A 30-year-old man presented with a large neck mass, dyspnea, and abdominal pain. The patient's serum calcium and parathormone levels were elevated. Radiography showed a right tracheal deviation, ultrasonography identified a thyroid nodular goiter extending to the mediastinum with a large (4.0 cm x 5.6 cm) cystic mass adjacent to the lower left thyroid pole. After IV fluid, pamidronate, and furosemide were administered, the patient underwent total thyroidectomy, and excision of the cyst and a small mass (2 cm x 2 cm) adjacent to the upper right thyroid lobe. Histopathologic examination revealed a double parathyroid adenoma and identified the mediastinal lesion as a cystic adenoma with intracystic hemorrhage.
Conclusions:
Intracystic hemorrhage in a functional mediastinal cystic parathyroid adenoma is an extremely rare cause of parathyrotoxic crisis. Aggressive medical treatment should be immediately instituted, and surgery should be performed as soon as hypercalcemia is controlled.
Related Concept Videos
 01:21
Acute Pancreatitis II: Pathophysiology
 01:20
Cholecystitis
 01:21
Cytotoxic Edema: Pathophysiology
 01:27
Hyperthyroidism II: Pathophysiology
 01:19
Cushing Syndrome II: Pathophysiology
 00:59
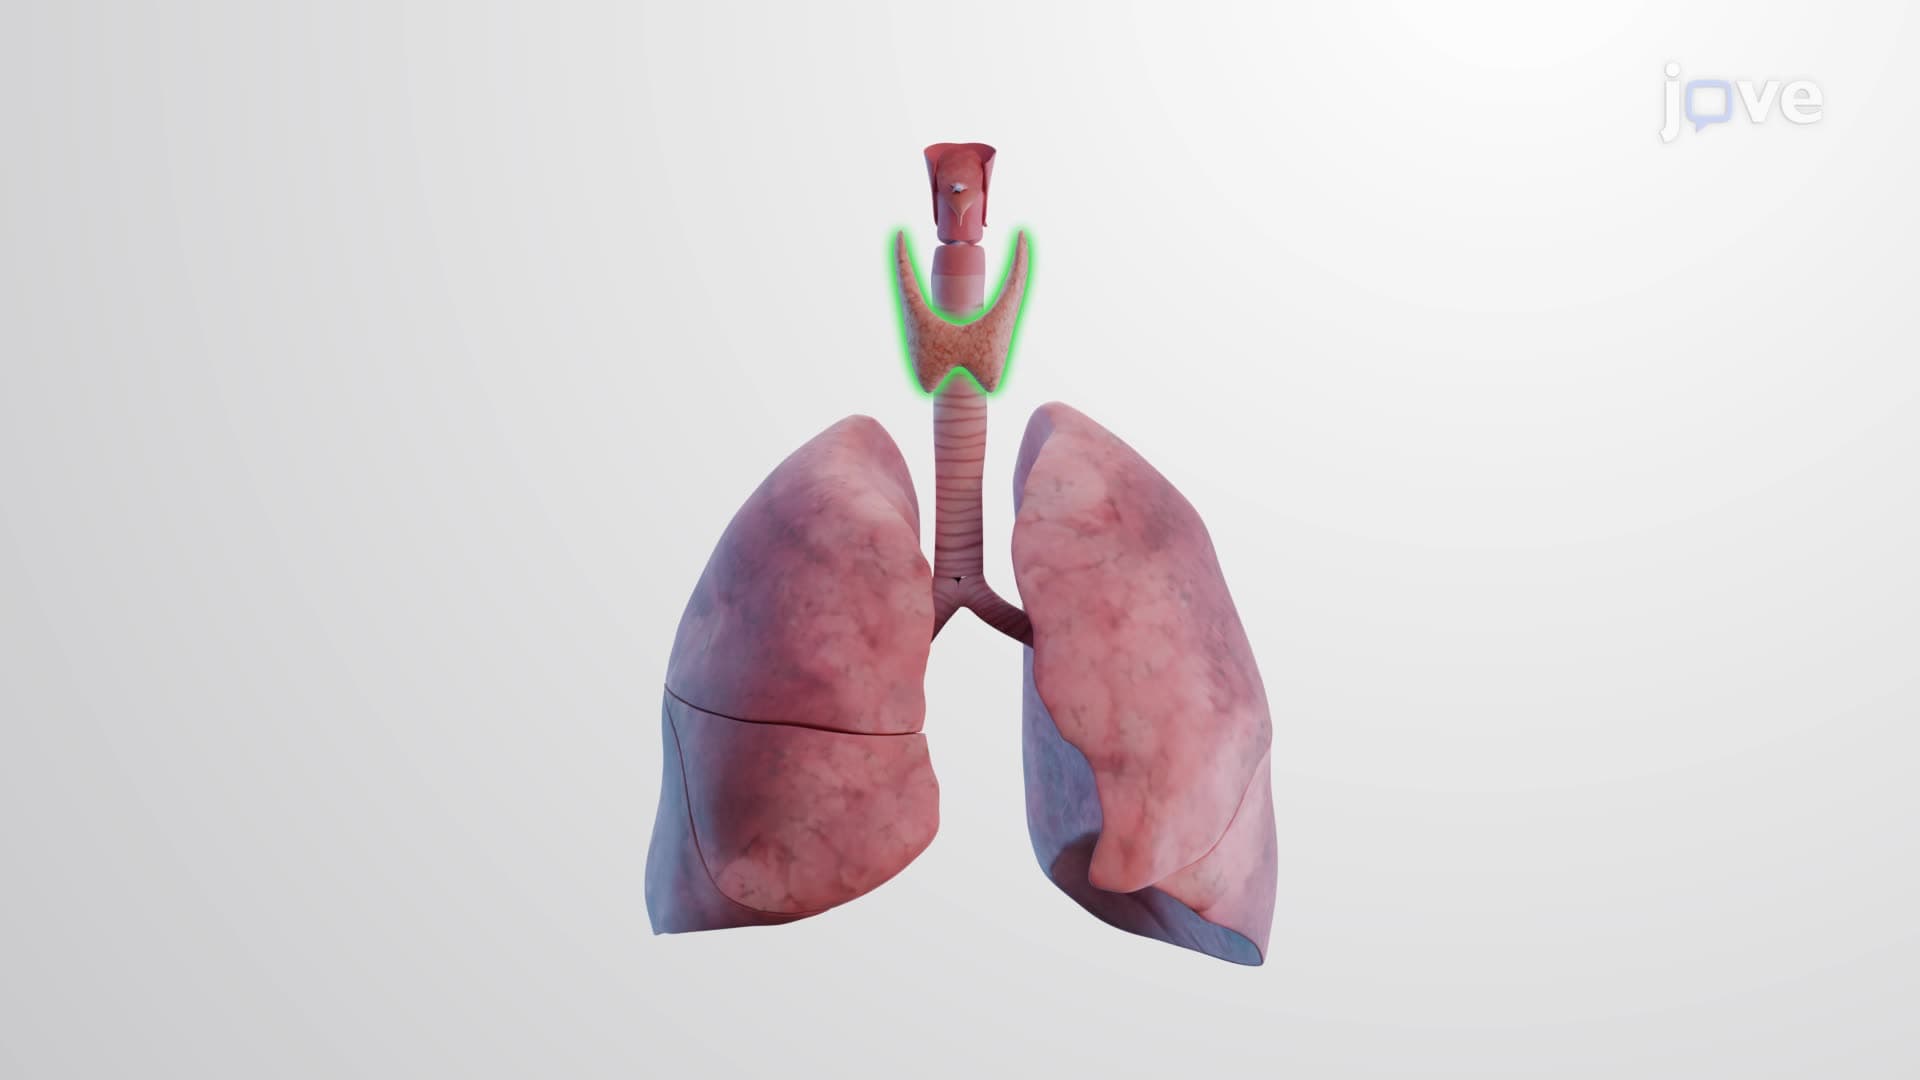
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...