The antithrombotic potential of selective blockade of talin-dependent integrin alpha IIb beta 3 (platelet GPIIb-IIIa) activation
Related Experiment Video
Updated: Jan 9, 2026

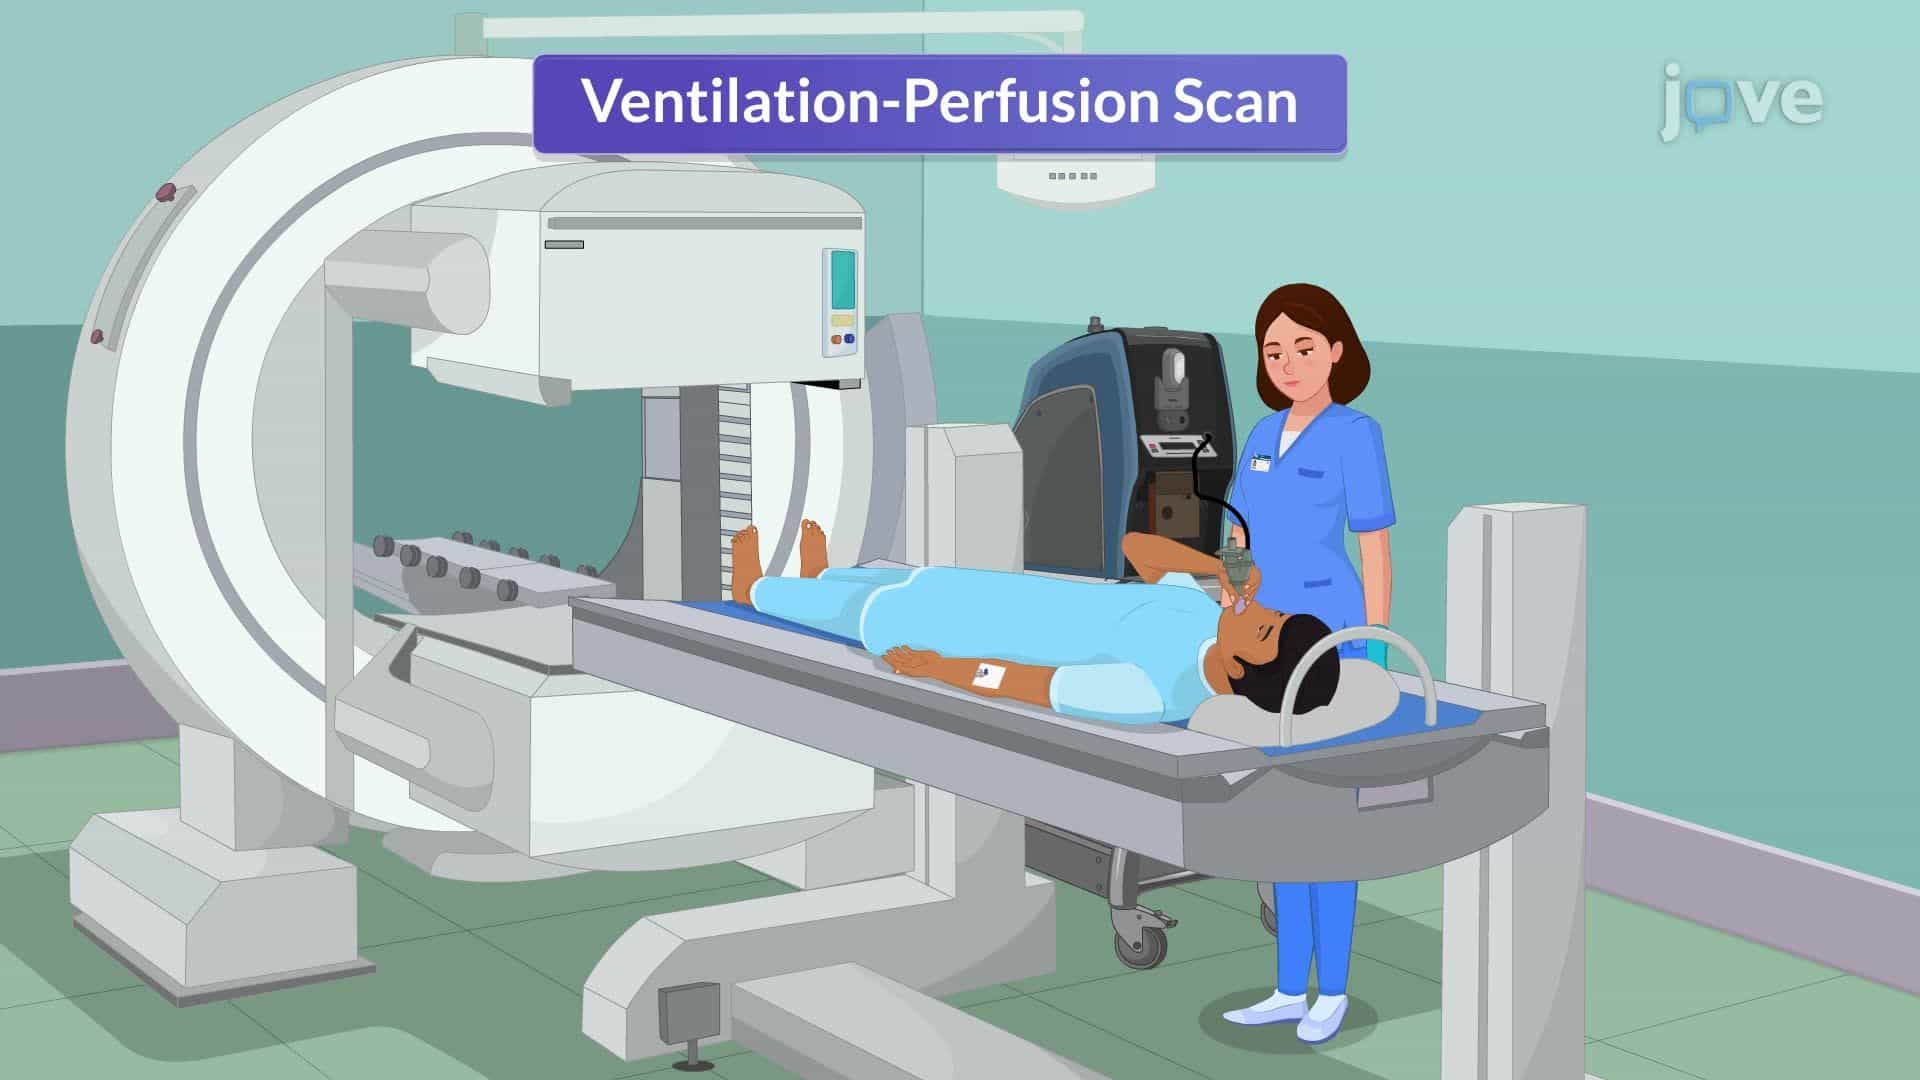
Pulmonary Embolism III: Nursing Management
Published on: June 19, 2025
Brian G Petrich1, Per Fogelstrand, Anthony W Partridge
1Department of Medicine, UCSD School of Medicine, La Jolla, California 92093-0726, USA.

In vitro studies indicate that binding of talin to the beta(3) integrin cytoplasmic domain (tail) results in integrin alpha(IIb)beta(3) (GPIIb-IIIa) activation. Here we tested the importance of talin binding for integrin activation in vivo and its biological significance by generating mice harboring point mutations in the beta(3) tail. We introduced a beta(3)(Y747A) substitution that disrupts the binding of talin, filamin, and other cytoplasmic proteins and a beta(3)(L746A) substitution that selectively disrupts interactions only with talin. Platelets from animals homozygous for each mutation showed impaired agonist-induced fibrinogen binding and platelet aggregation, providing proof that inside-out signals that activate alpha(IIb)beta(3) require binding of talin to the beta(3) tail. beta(3)(L746A) mice were resistant to both pulmonary thromboembolism and to ferric chloride-induced thrombosis of the carotid artery. Pathological bleeding, measured by the presence of fecal blood and development of anemia, occurred in 53% of beta(3)(Y747A) and virtually all beta(3)-null animals examined. Remarkably, less than 5% of beta(3)(L746A) animals exhibited this form of bleeding. These results establish that alpha(IIb)beta(3) activation in vivo is dependent on the interaction of talin with the beta(3) integrin cytoplasmic domain. Furthermore, they suggest that modulation of beta(3) integrin-talin interactions may provide an attractive target for antithrombotics and result in a reduced risk of pathological bleeding.
In vitro studies indicate that binding of talin to the beta(3) integrin cytoplasmic domain (tail) results in integrin alpha(IIb)beta(3) (GPIIb-IIIa) activation. Here we tested the importance of talin binding for integrin activation in vivo and its biological significance by generating mice harboring point mutations in the beta(3) tail. We introduced a beta(3)(Y747A) substitution that disrupts the binding of talin, filamin, and other cytoplasmic proteins and a beta(3)(L746A) substitution that selectively disrupts interactions only with talin. Platelets from animals homozygous for each mutation showed impaired agonist-induced fibrinogen binding and platelet aggregation, providing proof that inside-out signals that activate alpha(IIb)beta(3) require binding of talin to the beta(3) tail. beta(3)(L746A) mice were resistant to both pulmonary thromboembolism and to ferric chloride-induced thrombosis of the carotid artery. Pathological bleeding, measured by the presence of fecal blood and development of anemia, occurred in 53% of beta(3)(Y747A) and virtually all beta(3)-null animals examined. Remarkably, less than 5% of beta(3)(L746A) animals exhibited this form of bleeding. These results establish that alpha(IIb)beta(3) activation in vivo is dependent on the interaction of talin with the beta(3) integrin cytoplasmic domain. Furthermore, they suggest that modulation of beta(3) integrin-talin interactions may provide an attractive target for antithrombotics and result in a reduced risk of pathological bleeding.
Related Concept Videos
 01:27
Pulmonary Embolism III: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
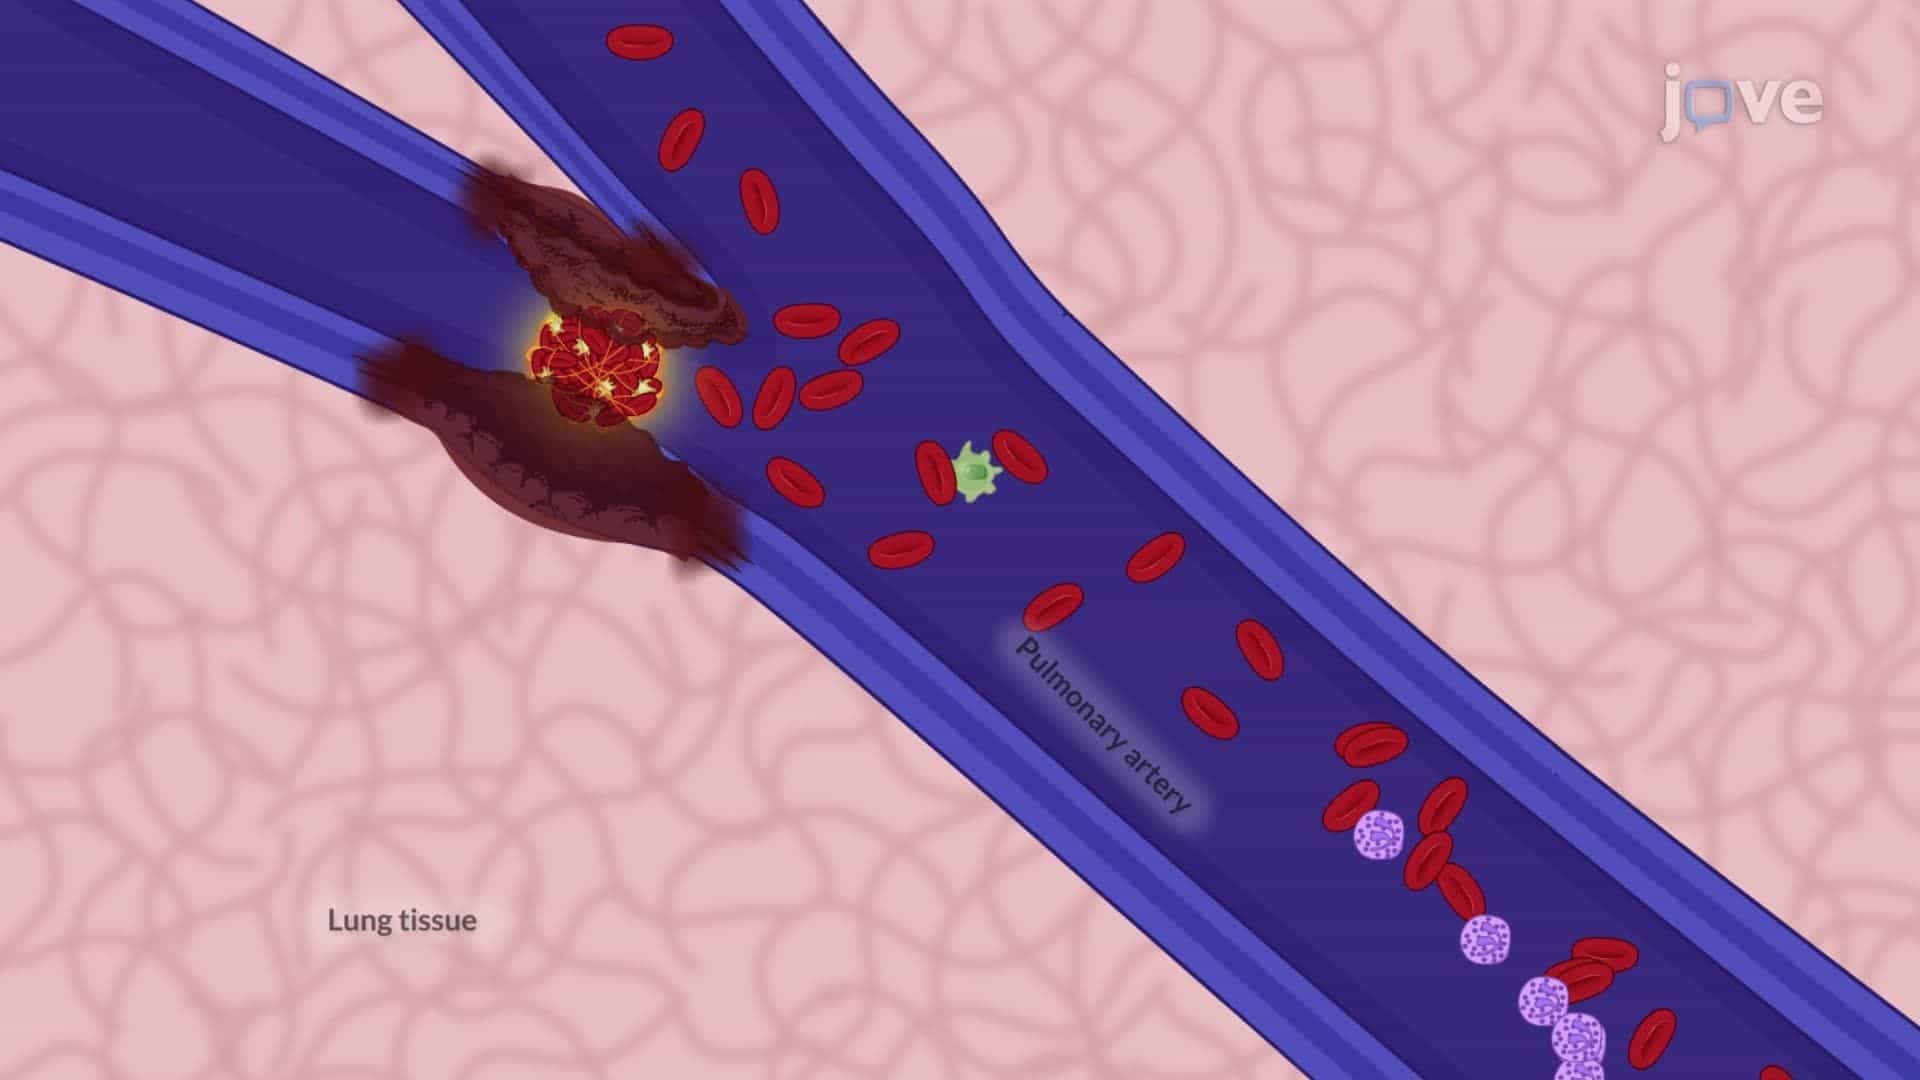
Pulmonary Embolism I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation