Related Experiment Video
Updated: Jul 13, 2026


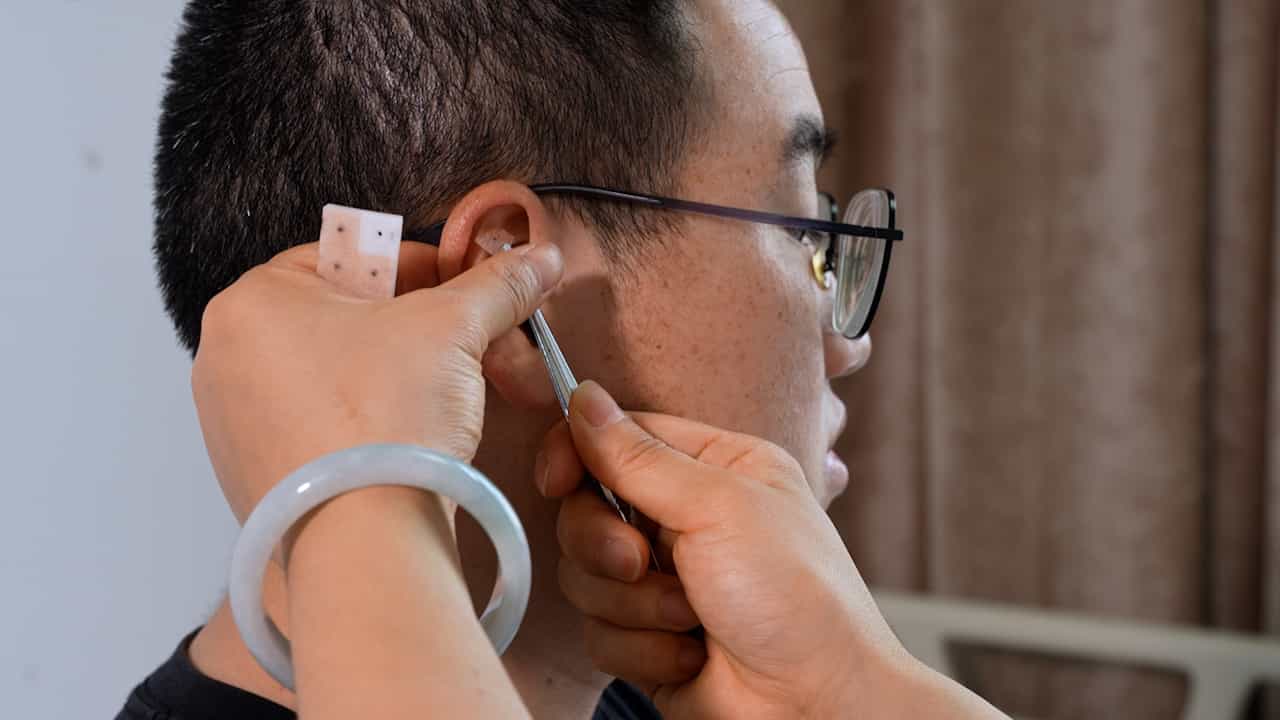
Acupoint Catgut Embedding Therapy in Traditional Chinese Medicine for Managing Allergic Rhinitis
Published on: December 20, 2024
WITHDRAWN: Decongestants and antihistamines for acute otitis media in children
C A Flynn1, G H Griffin, J K Schultz
1Faculty of Health Sciences and Medicine, C/O Cochrane ARI Group, Bond University, Gold Coast, Queensland, Australia, 4229. flynnc@twcny.rr.com

Insights
Decongestant and antihistamine treatments for acute otitis media (AOM) in children offer no significant benefits and increase side effect risks. Combined therapy showed a small, potentially biased, benefit for persistent AOM, but overall, these medications are not recommended.
Area of Science:
- Pediatrics
- Otolaryngology
- Pharmacology
Background:
- Acute otitis media (AOM) is a common childhood illness with significant morbidity.
- Decongestant and antihistamine therapies are frequently recommended for AOM but their efficacy is uncertain.
Purpose of the Study:
- To evaluate the effectiveness of decongestant and antihistamine treatments in children with AOM.
- Assessed outcomes included AOM resolution, symptom relief, medication side effects, and complication rates.
Main Methods:
- Systematic review and meta-analysis of randomized controlled trials (RCTs).
- Searched multiple databases (CENTRAL, MEDLINE, EMBASE) and contacted authors.
- Included trials without quality or language restrictions, focusing on patient-oriented outcomes.
Main Results:
- Fifteen trials with 2695 participants were analyzed.
- Combined decongestant-antihistamine therapy showed a statistically significant reduction in persistent AOM at two weeks (NNT=10).
- No benefits observed for early cure, symptom resolution, or complication prevention; increased risk of side effects (5-8 fold) noted for all decongestant groups. Higher quality studies found no benefit.
Conclusions:
- Current evidence does not support the use of decongestant treatment for AOM in children due to lack of benefit and increased side effects.
- The minimal statistical benefit of combination therapy is likely due to study design biases.
- Routine use of antihistamines for AOM in children is not recommended.
Background:
Acute otitis media (AOM) is a common and important source of morbidity in children, although most cases resolve spontaneously. While frequently recommended, decongestant and antihistamine therapy is of unclear benefit.
Objectives:
To determine the efficacy of decongestant and antihistamine therapy in children with AOM on outcomes of AOM resolution, symptom resolution, medication side effects, and complications of AOM.
Search Strategy:
We searched the Cochrane Central Register of Controlled Trials (CENTRAL) (The Cochrane Library Issue 3, 2003); MEDLINE (January 1966 to December 2003), EMBASE (January 1990 to July 2003) and reference lists of articles for this updated review. We also contacted study authors and pharmaceutical companies.
Selection Criteria:
Randomized controlled trials evaluating decongestant or antihistamine treatment for children with AOM were included. Patient-oriented outcomes were considered most relevant. There were no quality or language restrictions.
Data Collection And Analysis:
Investigators independently evaluated studies for inclusion, performed validity assessments, and completed data extraction. Dichotomous data were pooled to generate relative risks; homogeneity was assessed using approximate chi-square tests.
Main Results:
Fifteen trials involving 2695 people were included. Only the combined decongestant-antihistamine group demonstrated statistically lower rates of persistent AOM at the two week period (fixed relative risk (RR) 0.76; 95% confidence interval (CI) 0.60 to 0.96; number needed to treat (NNT) 10). No benefit was found for early cure rates, symptom resolution, prevention of surgery or other complications. There was a five to eight -fold increased risk of side effects for those receiving an intervention, which reached statistical significance for all decongestant groupings. Validity sub analyses demonstrated that lower quality studies found benefit, while analysis of those studies with higher validity scores found no benefit of treatment.
Authors' Conclusions:
Given lack of benefit and increased risk of side effects, these data do not support the use of decongestant treatment in children with AOM. There was a small statistical benefit from combination medication use but the clinical significance is minimal and study design may be biasing the results. Thus, the routine use of antihistamines for treating AOM in children cannot be recommended.
Related Concept Videos
 01:27
Upper Respiratory Drugs: Decongestants
Most decongestants are readily available over-the-counter in various...
 01:16
Drugs Used in Upper Respiratory Disorders: Overview
Antihistamines (e.g., Benadryl) block histamines from binding. Histamines are chemicals released during an allergic reaction in the body. As a...
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:26
Tonsillitis II: Management
 01:15
Upper Respiratory Drugs: First and Second-Generation Antihistamines
Histamine binds to specific receptor sites, known as H1 receptors, on tissue cells, triggering inflammation and swelling. Antihistamines combat these effects by competing with histamine for these receptor sites. By...
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...