Related Experiment Video
Updated: Jul 13, 2026
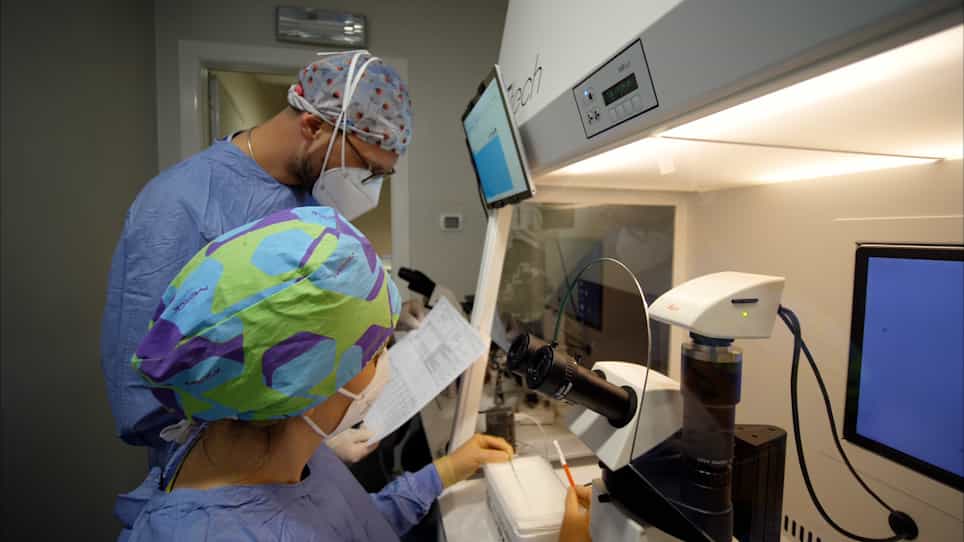

Fertility Preservation Through Oocyte Vitrification: Clinical and Laboratory Perspectives
Published on: September 16, 2021
WITHDRAWN: Recombinant versus urinary follicle stimulating hormone for ovarian stimulation in assisted reproduction
1Department of Obstetrics & Gynecology, Clinical Epidemiology & Biostatistics, 2407 Carrington Place, Oakville, Ontario, Canada, L6J 7R6. dayas@mcmaster.ca

Background:
Until recently, the main source of exogenous follicle stimulating hormone (FSH) for therapeutic use in infertility had been the urine of postmenopausal women. New developments have resulted in the production of FSH in vitro by recombinant DNA technology. The extremely high purity and batch-to-batch consistency of recombinant FSH (rFSH) make it an attractive alternative to urinary FSH (uFSH).
Objectives:
To conduct a systematic review and meta-analysis of randomised trials comparing the effectiveness of rFSH with uFSH in ovarian stimulation protocols in in vitro fertilization (IVF) or intra-cytoplasmic sperm injection (ICSI) treatment cycles.
Search Strategy:
Search strategies included on-line searching of the MEDLINE and EMBASE databases from 1985 to 1999, hand searching of bibliographies of relevant publications and reviews and abstracts of scientific meetings, peer consultation and contacting the pharmaceutical companies that manufacture the gonadotropins under consideration.
Selection Criteria:
Randomised trials comparing rFSH with uFSH for ovarian stimulation in IVF or ICSI treatment for infertility.
Data Collection And Analysis:
The main outcome measure was clinical pregnancy per cycle started. Also considered were clinical pregnancy per cycle reaching oocyte retrieval and per cycle reaching embryo transfer (ET), ongoing pregnancy per cycle started, spontaneous abortion, multiple pregnancy, ovarian hyperstimulation syndrome (OHSS), number of follicles and serum estradiol level on the day of human chorionic gonadotropin administration day, total dose of FSH, and number of oocytes retrieved. Common odds ratios (OR) and risk differences for rFSH relative to uFSH were calculated after testing for homogeneity of treatment effect across all trials. The fixed effects model was used, unless significant heterogeneity was present, in which case the random effects model was used.
Main Results:
The overall odds ratio for clinical pregnancy per cycle started was 1.21 (95% confidence limits (CL) 1.04,1.42) for rFSH compared to uFSH. The risk difference was a 3.7% (0.8,6.7) absolute increase in clinical pregnancy rate with rFSH. The OR for ongoing pregnancy per cycle started was 1.29 (1.08,1.54). There was no significant difference between rFSH and uFSH in the rates of spontaneous abortion, multiple pregnancy or OHSS. The total dose of FSH was lower by 406 (185,627) IU with rFSH, but there was no significant difference in the number of follicles or serum estradiol on hCG day or in the number of oocytes retrieved.
Authors' Conclusions:
This review has demonstrated a statistically significant increase in clinical pregnancy rate with rFSH compared to uFSH, when used for ovarian stimulation in assisted reproduction. This benefit was observed only in standard IVF cycles and not in cycles in which ICSI was used.
More Related Videos

Related Concept Videos
 01:24
In Vitro Fertilization
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
 01:27
Ovarian Cycle
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:20
Folliculogenesis