Related Experiment Video
Updated: Jul 13, 2026
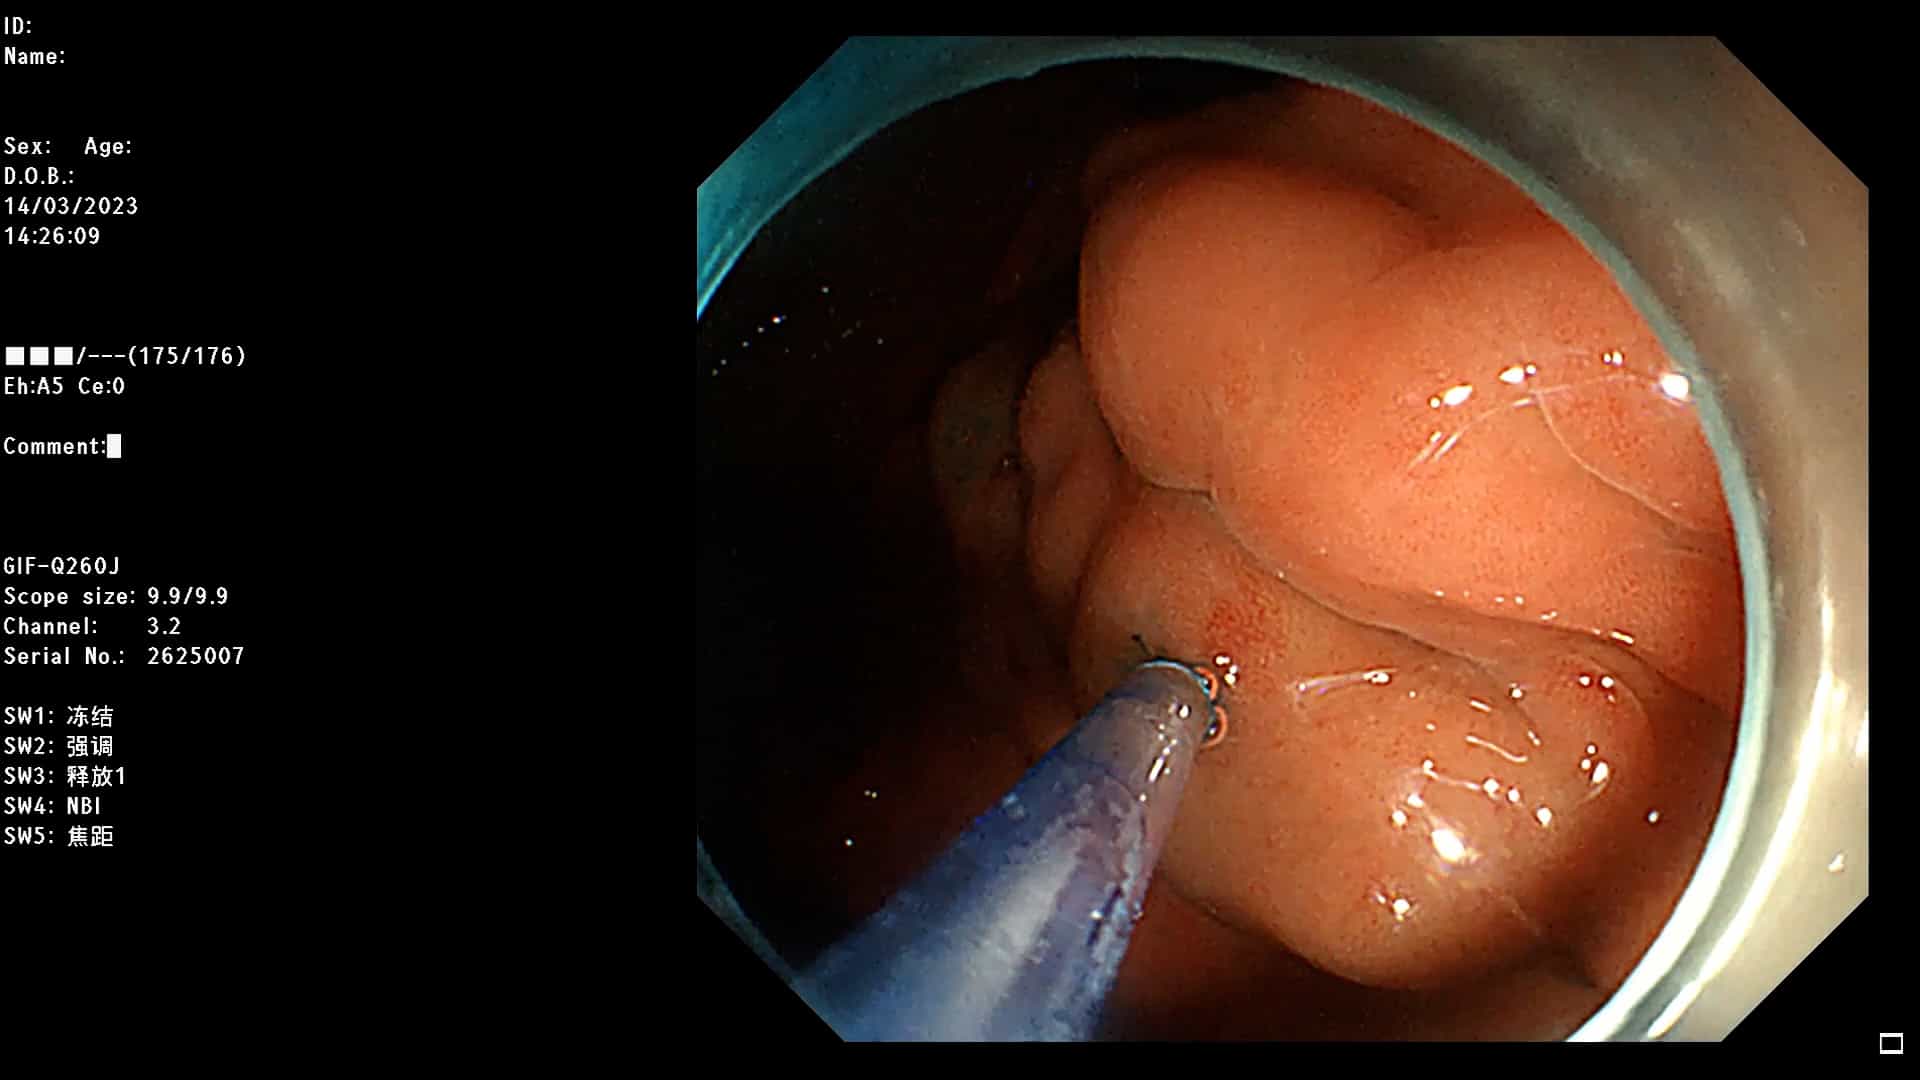
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
The role of rapid endoscopy for high-risk patients with acute nonvariceal upper gastrointestinal bleeding
Laura E Targownik1, Sanjay Murthy, Leila Keyvani
1Section of Gastroenterology, Department of Internal Medicine, Universty of Manitoba, Winnipeg, Canada. targowni@cc.umanitoba.ca

Background:
Performance of endoscopy within 24 h is recommended for patients with acute nonvariceal upper gastrointestinal bleeding (ANVUGIB). It is unknown whether performing endoscopy early within this 24 h window is beneficial for clinically high-risk patients.
Methods:
A retrospective review was performed to identify patients presenting to two tertiary care centres with ANVUGIB and either systolic blood pressure lower than 100 mmHg or heart rate greater than 100 beats/min on presentation between 1999 and 2004. Patients receiving endoscopy within 6 h (rapid endoscopy [RE]) were compared with patients undergoing endoscopy between 6 h and 24 h (early endoscopy [EE]). The primary outcome measure was the development of any adverse bleeding outcome (rebleeding, surgery for control of bleeding, in-hospital mortality or readmission within 30 days for ANVUGIB).
Results:
There were 169 patients who met the entry criteria (77 RE patients and 92 EE patients). There was no significant difference in the development of any adverse bleeding outcomes between RE and EE patients (25% RE versus 23% EE, difference between groups 2%, 95% CI --9% to 13%). Transfusion requirements and length of hospital stay also did not differ between the comparator groups. RE was not associated with fewer adverse outcomes, even after adjusting for confounders.
Conclusion:
For clinically high-risk ANVUGIB patients, performing endoscopy within 6 h of presentation is no more effective than performing endoscopy between 6 h and 24 h after presentation. The role of RE in high-risk ANVUGIB patients requires further delineation in a prospective fashion.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:27
Peptic Ulcer
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.