Related Experiment Video
Updated: Jul 13, 2026

A Test Bed to Examine Helmet Fit and Retention and Biomechanical Measures of Head and Neck Injury in Simulated Impact
Published on: September 21, 2017
Pattern, management and outcome of cervical spine injuries associated with head injuries in paediatric patients
C O Oluigbo1, Y C Gan, S Sgouros
1Department of Paediatric Neurosurgery, Birmingham Children's Hospital, Birmingham, B4 6NH, UK.

Insights
Most pediatric cervical spine injuries in children with head trauma can be managed non-surgically, leading to good outcomes. Surgery is reserved for severe, unstable injuries.
Area of Science:
- Pediatric Traumatology
- Neurosurgery
- Orthopedic Surgery
Background:
- Cervical spine injuries in children with head trauma require careful management.
- Assessing the need for surgical intervention is crucial for optimal outcomes.
Purpose of the Study:
- To examine the management and outcomes of cervical spine injuries in pediatric patients with concurrent head injuries.
- To determine the indications for surgical treatment in this population.
Main Methods:
- Retrospective analysis of 445 children admitted to the intensive care unit with head injuries between 1995 and 2005.
- Evaluation of cervical spine injuries using Frankel grade and head injuries using Glasgow Outcome Scale (GOS).
Main Results:
- Cervical spine injuries were identified in 11 patients (2.5% incidence).
- The majority (10/11) were managed nonoperatively with good spinal outcomes (Frankel Grade E) in 5 patients.
- Three deaths occurred, primarily due to severe head injuries; 2 patients had significant neurological deficits (quadriplegic or functionally disabled).
Conclusions:
- Nonoperative management is effective for most pediatric cervical spine injuries.
- Surgical intervention should be considered for severe, unstable injuries to improve patient outcomes.
Introduction:
This study examines the management and outcome of cervical spine injuries in children with head injuries, to assess the need for surgical treatment.
Material And Methods:
We performed a retrospective analysis (1995-2005) of 445 children admitted intubated and ventilated to the intensive care unit with head injuries.
Outcome Measures:
Frankel grade for spinal injuries and Glasgow Outcome Scale (GOS) for head injuries.
Results:
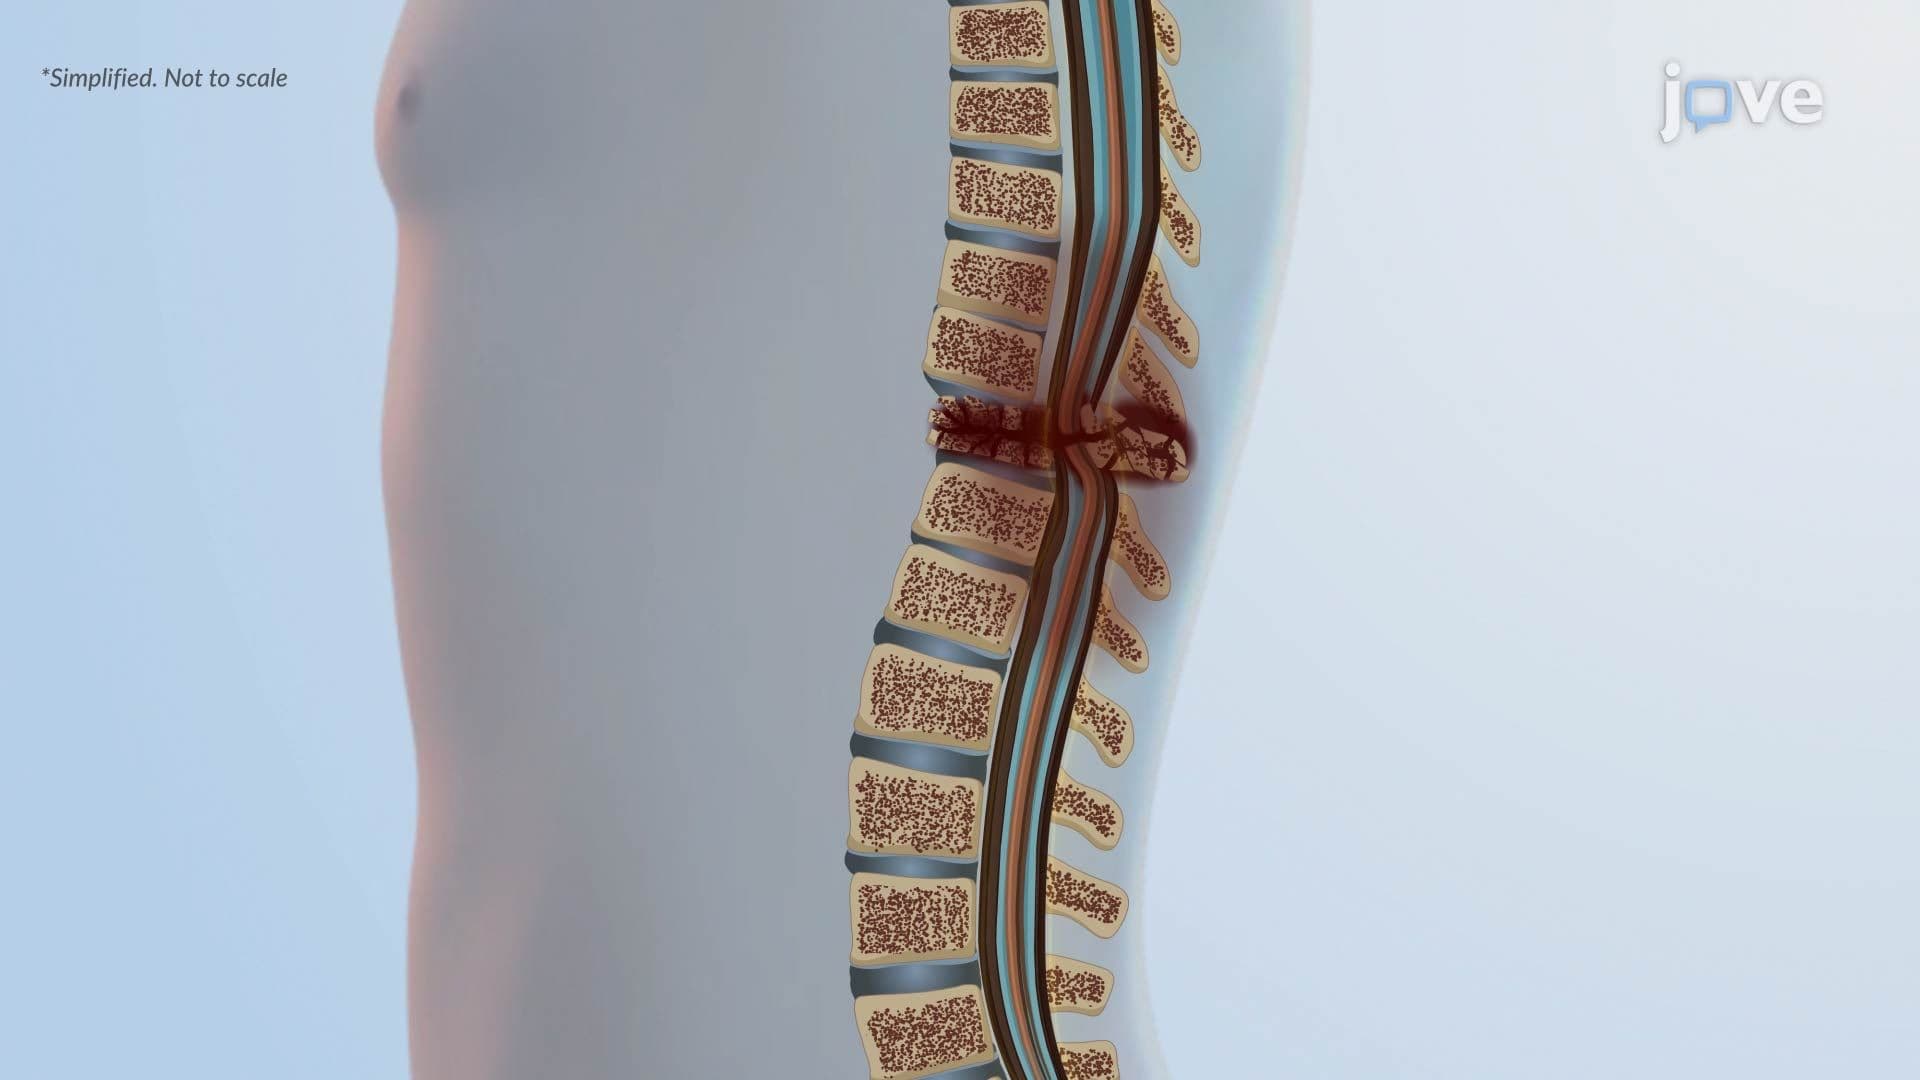
Cervical spine injuries were detected in 11 patients (incidence 2.5%, mean age: 6.3 years, range: 21 months-15 years). The injuries were: C1/2 distraction: 2; C1/2 subluxation: 2; odontoid peg fracture with C1/2 dislocation and cord transection: 1; disruption of posterior longitudinal ligament at C2: 1; odontoid peg fracture with C2/3 distraction: 1; C2/3 subluxation: 1; C3 lamina fracture: 1; C3/4 facet fracture: 1; C6/7 fracture dislocation with cord transection: 1. One patient was managed operatively, ten patients nonoperatively, two with halo vests and eight with hard collars. There were three deaths (mortality 27%) associated with severe head injuries. At 6 months follow-up, two patients remained quadriplegic (Frankel Grade A), one of them ventilator dependent, one had residual motor function but of no practical use (Frankel Grade C), five had good spinal outcome (Frankel Grade E). Seven patients had good head injury outcomes (GOS 5), one remained disabled (GOS 3).
Conclusion:
Most children with cervical injury can be managed nonoperatively with good outcomes. Surgical management may be necessary in severe unstable injuries.