Abnormal spirometry in children with persistent allergic rhinitis due to mite sensitization: the benefit of nasal corticosteroids
Related Experiment Video
Updated: Jul 13, 2026
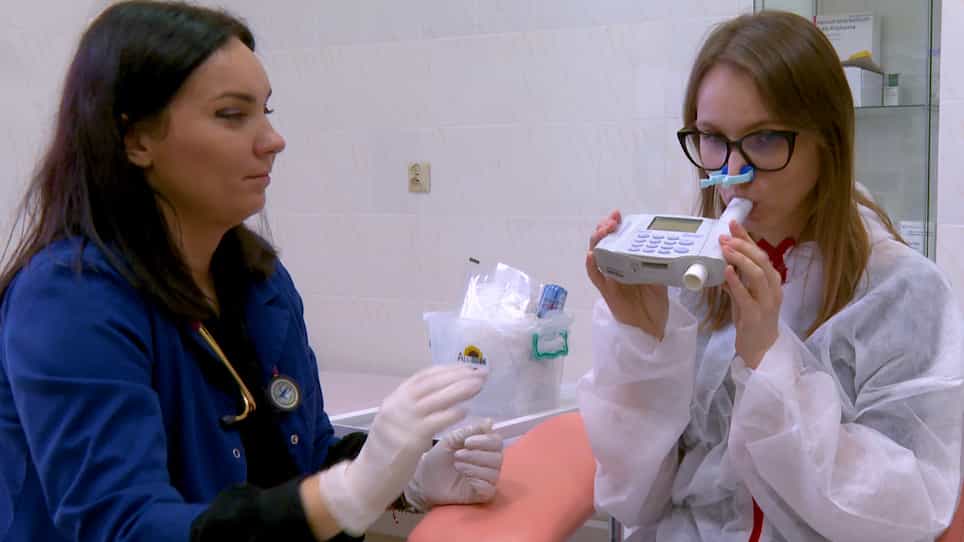
Symptom Assessment of Patients with Allergic Rhinitis Using an Allergen Exposure Chamber
Published on: March 3, 2023
Aharon Kessel1, Hadeel Halloun, Ellen Bamberger
1Division of allergy and clinical Immunology, Department of Clinical Microbiology, Faculty of Medicine Technion, Haifa, Israel. adharon.kessel@b-zion.org.il

Insights
Children with perennial allergic rhinitis often have impaired lung function, specifically reduced forced expiratory flow rates. Nasal corticosteroids significantly improved these pulmonary function tests in affected children.
Area of Science:
- Pediatric Allergy and Immunology
- Pulmonary Medicine
- Respiratory Physiology
Background:
- Inflammatory processes in the nasal and bronchial mucosa share similarities.
- Perennial allergic rhinitis (PAR) in children may impact lower airway function.
- Asthma is often considered in differential diagnoses for pediatric respiratory symptoms.
Purpose of the Study:
- To investigate pulmonary function in children with PAR but without asthma.
- To determine if nasal corticosteroids and loratidine improve lung function in these children.
- To assess the prevalence of impaired pulmonary function in children with PAR.
Main Methods:
- Fifty children with moderate/severe persistent PAR (dust mite-sensitized) and 26 healthy controls were assessed.
- Pulmonary function tests, including forced expiratory volume/1s (FEV1) and forced expiratory flow from 25-75% (FEF(25-75)), were performed.
- Subjects with airway obstruction (<80% predicted FEF(25-75)) received loratidine and nasal budesonide treatment.
Main Results:
- 22% of children with PAR exhibited impaired pulmonary function (FEF(25-75) <80%) compared to 3.8% in controls (p <= 0.05).
- Airway obstruction was reversible in 81.8% of affected children.
- Three months of treatment led to improved FEF(25-75) and significant increases in FEV1 (p=0.04) and FEV1/FVC (p=0.04).
Conclusions:
- A significant portion of children with PAR experience diminished FEF(25-75) values and reversible airway obstruction.
- Nasal corticosteroids effectively improve pulmonary function tests in children with PAR and impaired lung function.
- These findings highlight the importance of assessing lower airway function in pediatric allergic rhinitis.
Abstract:
Inflammatory processes affecting nasal and bronchial mucosa are similar in nature. The purpose of this study was to examine whether children with perennial allergic rhinitis, without underlying asthma, have impaired pulmonary function. We also investigated whether nasal corticosteroids and loratidine would improve the pulmonary function tests of those children with impaired lung function. Fifty subjects with moderate/severe persistent allergic rhinitis due to exclusively dust mite sensitization and no past medical history suggestive of asthma were assessed. The control group consisted of 26 matched healthy subjects. Subjects with airway obstruction, as detected by forced expiratory volume/1 s (FEV1) or forced expiratory flow from 25/% to 75% (FEF(25-75)) values <80% of those predicted, were treated with loratidine, once a day for 10 days, and daily nasal budesonide for 3 months. We found that 11 of 50 patients (22%) with perennial allergic rhinitis had impaired pulmonary function (FEF(25-75) values <80%), compared to 1/26 (3.8%) of the control group (p < or = 0.05). Reversibility was observed in 9/11 (81.8%), mean 24.7% +/- 10.3%. Within 3 months of treatment, 7/10 had FEF(25-75) > 80% of their predicted values as well as significant improvements in their FEV1 (p = 0.04), and FEV1/FVC (p = 0.04). We conclude that a substantial proportion of children with perennial allergic rhinitis have diminished FEF (25-75) values and reversible airway obstruction. Nasal corticosteroids improve the pulmonary function tests of these children with impaired lung function.
Related Concept Videos
 01:28
Asthma I: Introduction
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...