Related Experiment Video
Updated: May 1, 2026

A Microplate Assay to Assess Chemical Effects on RBL-2H3 Mast Cell Degranulation: Effects of Triclosan without Use of an Organic Solvent
Published on: November 2, 2013
Disposition of bromodichloromethane in humans following oral and dermal exposure
Teresa L Leavens1, Benjamin C Blount, David M DeMarini
1U.S. EPA, Office of Research and Development (ORD), National Health and Environmental Effects Research Laboratory (NHEERL), Human Studies Division, Chapel Hill, North Carolina 27599, USA.

Abstract:
Exposure to bromodichloromethane (BDCM), one of the most prevalent disinfection byproducts in drinking water, can occur via ingestion of water and by dermal absorption and inhalation during activities such as bathing and showering. The objectives of this research were to assess BDCM pharmacokinetics in human volunteers exposed percutaneously and orally to (13)C-BDCM and to evaluate factors that could affect disposition of BDCM. Among study subjects, CYP2E1 activity varied fourfold; 20% had the glutathione S-transferase theta 1-1 homozygous null genotype; and body fat ranged from 7 to 22%. Subjects were exposed to (13)C-BDCM in water (target concentration of 36 mug/l) via ingestion and by forearm submersion. Blood was collected for up to 24 h and analyzed for (13)C-BDCM by solid-phase microextraction and high-resolution GC-MS. Urine was collected before and after exposure for mutagenicity determinations in Salmonella. After ingestion (mean dose = 146 ng/kg), blood (13)C-BDCM concentrations peaked and declined rapidly, returning to levels near or below the limit of detection (LOD) within 4 h. The T(max) for the oral exposure ranged from 5 to 30 min, and the C(max) ranged from 0.4 to 4.1 ng/l. After the 1 h dermal exposure (estimated mean dose = 155 ng/kg), blood concentrations of (13)C-BDCM ranged from 39 to 170 ng/l and decreased to levels near or below the LOD by 24 h. Peak postdose urine mutagenicity levels that were at least twice that of the predose mean level occurred in 6 of 10 percutaneously exposed subjects and 3 of 8 orally exposed subjects. These results demonstrate a highly significant contribution of dermal absorption to circulating levels of BDCM and confirm the much lower oral contribution, indicating that water uses involving dermal contact can lead to much greater systemic BDCM doses than water ingestion. These data will facilitate development and validation of physiologically based pharmacokinetic models for BDCM in humans.


Related Concept Videos
 02:46
Halogenation of Alkenes
Consider the bromination of cyclopentene. Molecular bromine is polarized in the proximity of the π electrons of cyclopentene. An electrophilic bromine atom adds across the double bond, forming a cyclic bromonium ion intermediate.
 02:41
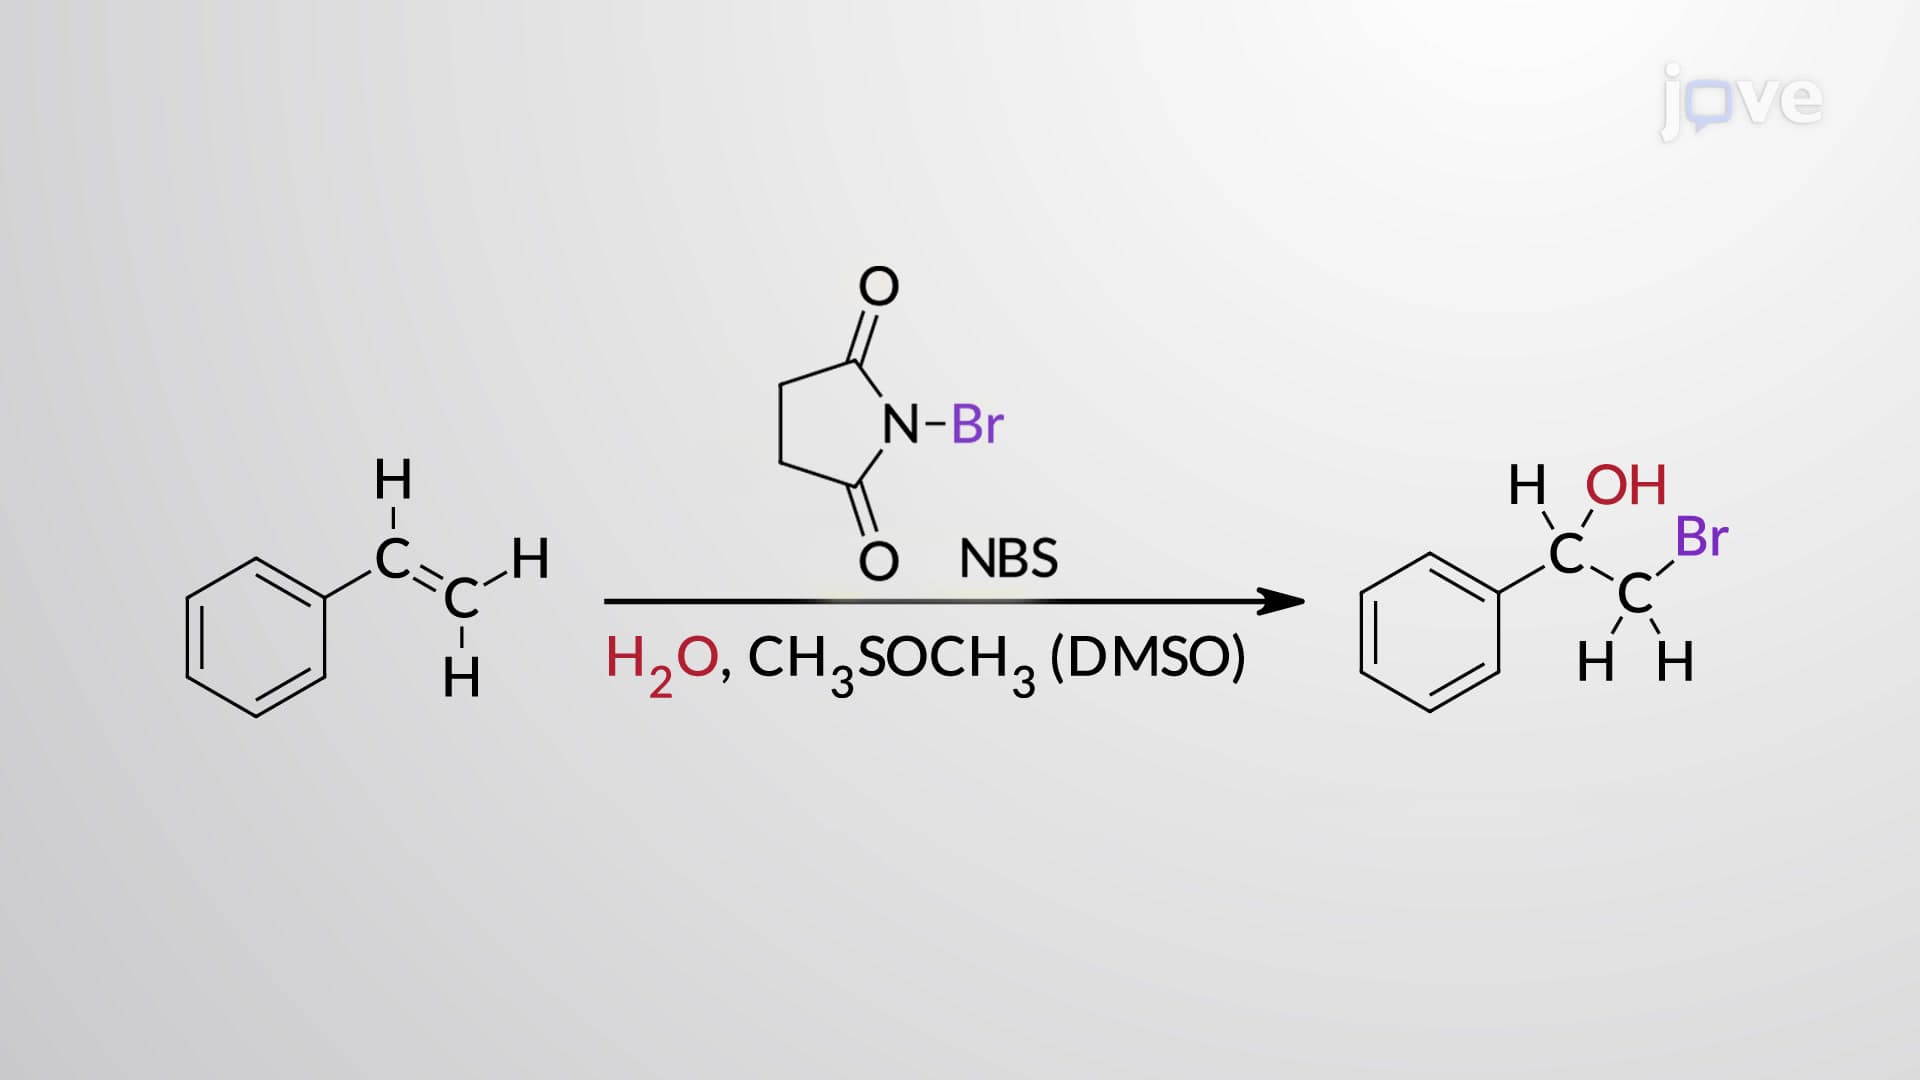
Formation of Halohydrin from Alkenes
 01:15
Electrophilic Aromatic Substitution: Chlorination and Bromination of Benzene
 01:26
Toxic Reactions: Overview
Toxicity falls into two primary categories: local and systemic.
Local toxicity appears at the exposure site, such as protein denaturation caused by caustic substances.
In contrast, systemic toxicity requires the toxic agent's absorption and distribution,...
 01:25
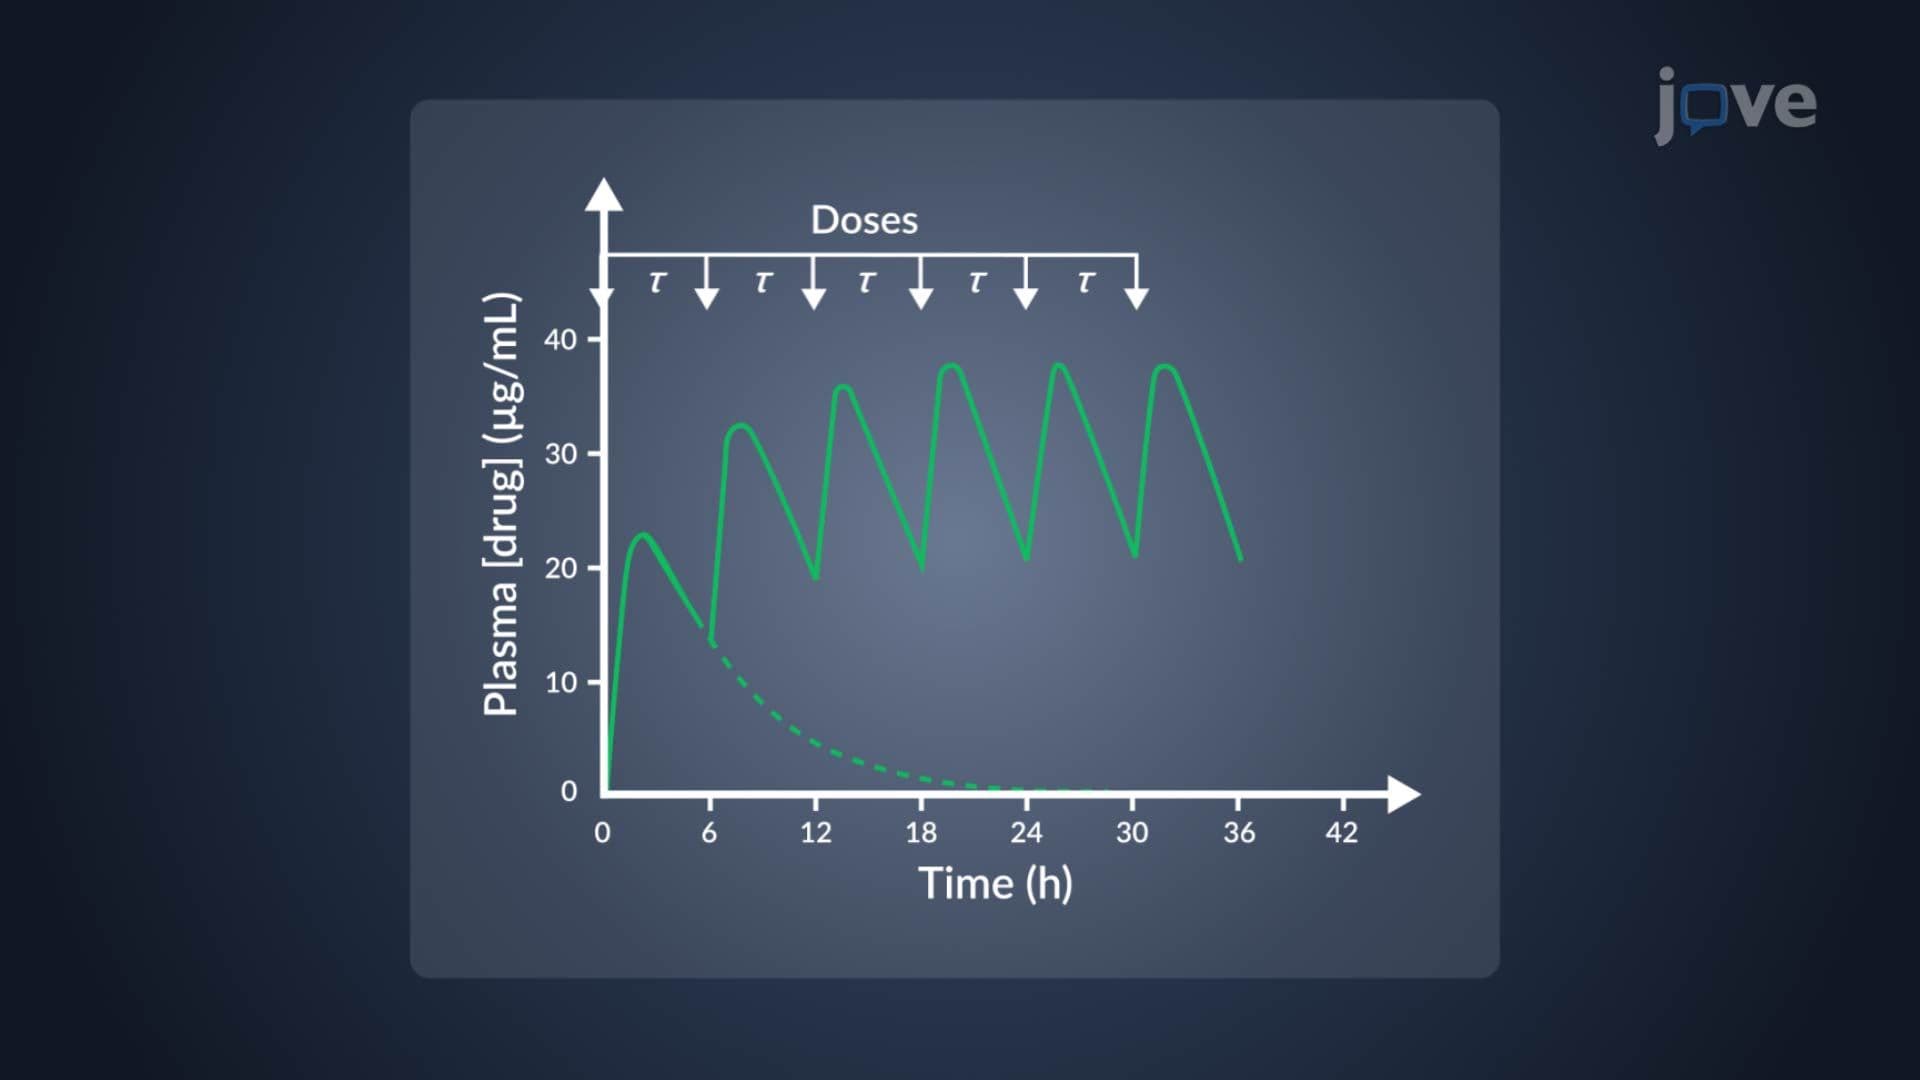
Dosage Regimen: Multiple Oral Dosage
 01:23
Toxicity Testing in Animals