Related Experiment Video
Updated: Jul 13, 2026


Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
Up-to-date information on gastric mucosal lesions from long-term NSAID therapy in orthopedic outpatients: a study
Hiroshi Yajima1, Junichi Yamao, Hiroshi Fukui
1Department of Orthopedic Surgery, Nara Medical University, Kashihara, Nara, Japan.

Background:
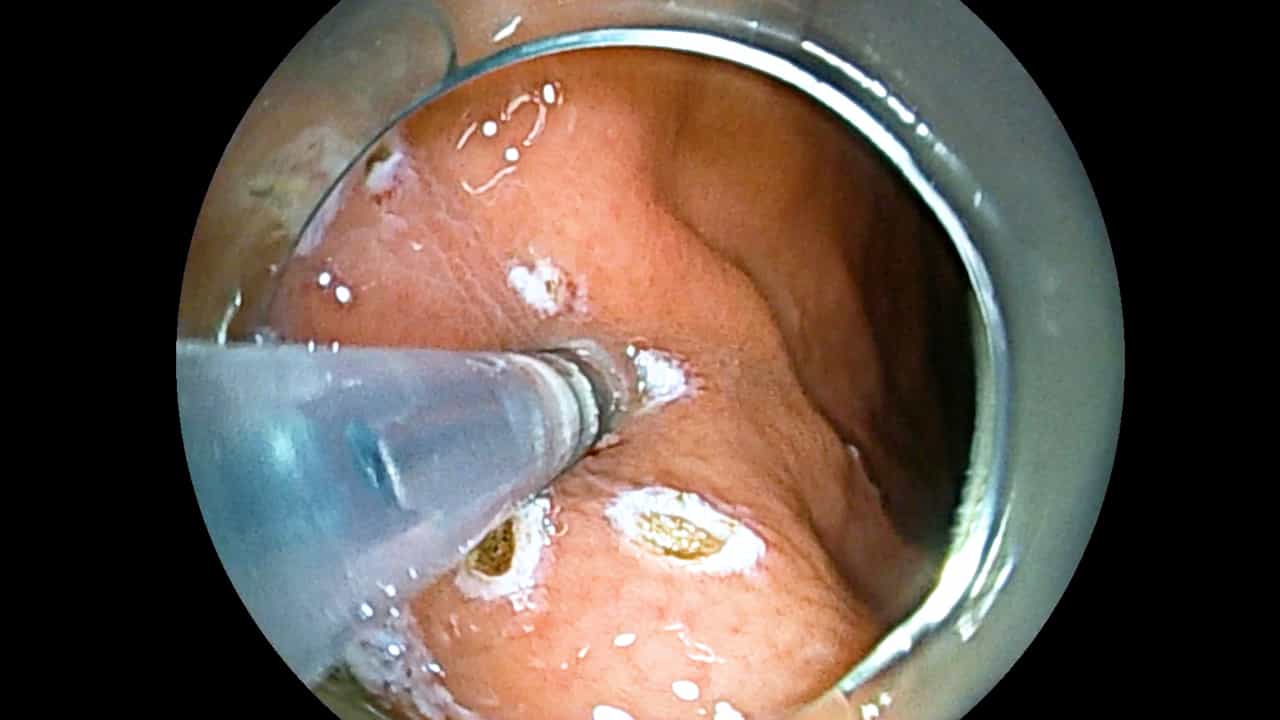
An increase in gastric mucosal lesions due to nonsteroidal antiinflammatory drugs (NSAIDs) has been reported along with the aging of society; even orthopedic surgeons can no longer remain unconcerned about this disease. However, no study has accurately examined the incidence of gastric mucosal lesions; therefore, adequate evidence has not been established. In this study, endoscopic examinations were performed to determine the status of gastric mucosal lesions in patients receiving long-term NSAID therapy.
Methods:
In 261 patients receiving NSAIDs other than aspirin for more than 28 days, excluding external application, upper gastrointestinal endoscopy was performed regardless of any subjective symptoms after obtaining the patient's medical history. The severity of the gastric mucosal lesions was evaluated using the modified Lanza score. Patient factors involved in the development of lesions were examined using a logistic regression analysis with criterion variables of gastric mucosal lesions and ulcers and the factors of sex, age, Helicobacter pylori infection, and type of NSAID as candidates for the explanatory variable.
Results:
Gastric mucosal lesions were observed in 164 patients (62.8%); 27 (10.3%) had ulcers. The use of diclofenac, subjective symptoms, irregular lifestyle, and increased body mass index (BMI) were four factors associated with the development of gastric mucosal lesions; the odds ratios were 2.99, 1.92, 1.80, and 1.09, respectively. Also, the use of diclofenac, presence of H. pylori, irregular lifestyle, alcohol consumption, and aging were five factors associated with the development of ulcers; the odds ratios were 6.40, 6.07, 2.62, 2.06, and 1.05, respectively.
Conclusions:
Diclofenac can cause gastric mucosal lesions, including ulcers, more easily than other NSAIDs. H. pylori infection is a high-risk factor for ulcers in patients receiving long-term NSAIDs therapy. In NSAID-treated patients, subjective symptoms are not grounds for a diagnosis of gastric mucosal lesions, especially ulcers.
Related Concept Videos
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...