Related Experiment Video
Updated: Jul 13, 2026


Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Vaginal birth and de novo stress incontinence: relative contributions of urethral dysfunction and mobility
John O L DeLancey1, Janis M Miller, Rohna Kearney
1Department of Obstetrics and Gynecology, Pelvic Floor Research Group, and School of Nursing, University of Michigan, 1500 East Medical Center Drive, Ann Arbor, MI 48109, USA. DeLancey@umich.edu

Objective:
To evaluate the relative contributions of urethral mobility and urethral function to stress incontinence.
Methods:
This was a case-control study with group matching. Eighty primiparous women with self-reported new stress incontinence 9-12 months postpartum were compared with 80 primiparous continent controls to identify impairments specific to stress incontinence. Eighty nulliparous continent controls were evaluated as a comparison group to allow us to determine birth-related changes not associated with stress incontinence. Urethral function was measured with urethral profilometry, and vesical neck mobility was assessed with ultrasound and cotton swab test. Urethral sphincter anatomy and mobility were evaluated using magnetic resonance imaging. The associations among urethral closure pressure, vesical neck movement, and incontinence were explored using logistic regression.
Results:
Urethral closure pressure (+/-standard deviation) in primiparous incontinent women (62.9+/-25.2 cm H(2)0) was lower than in primiparous continent women (83.9+/-21.0, P<.001; effect size d=0.91) who were similar to nulliparous women (90.3+/-25.0, P=.091). Vesical neck movement measured during cough with ultrasonography was the mobility measure most associated with stress incontinence; 15.6+/-6.2 mm in incontinent women compared with 10.9+/-6.2 in primiparous continent women (P<.001, d=0.76) or nulliparas (9.9+/-5.0, P=.322). Logistic regression disclosed the two-variable model (max-rescaled R(2)=0.37, P<.001) was more strongly associated with stress incontinence than either single-variable model, urethral closure pressure (R(2)=0.25, P<.001) or vesical neck movement (R(2)=0.16 P<.001).
Conclusion:
Lower maximal urethral closure pressure is the measure most associated with de novo stress incontinence after first vaginal birth followed by vesical neck mobility.
Level Of Evidence:
II.

Related Concept Videos
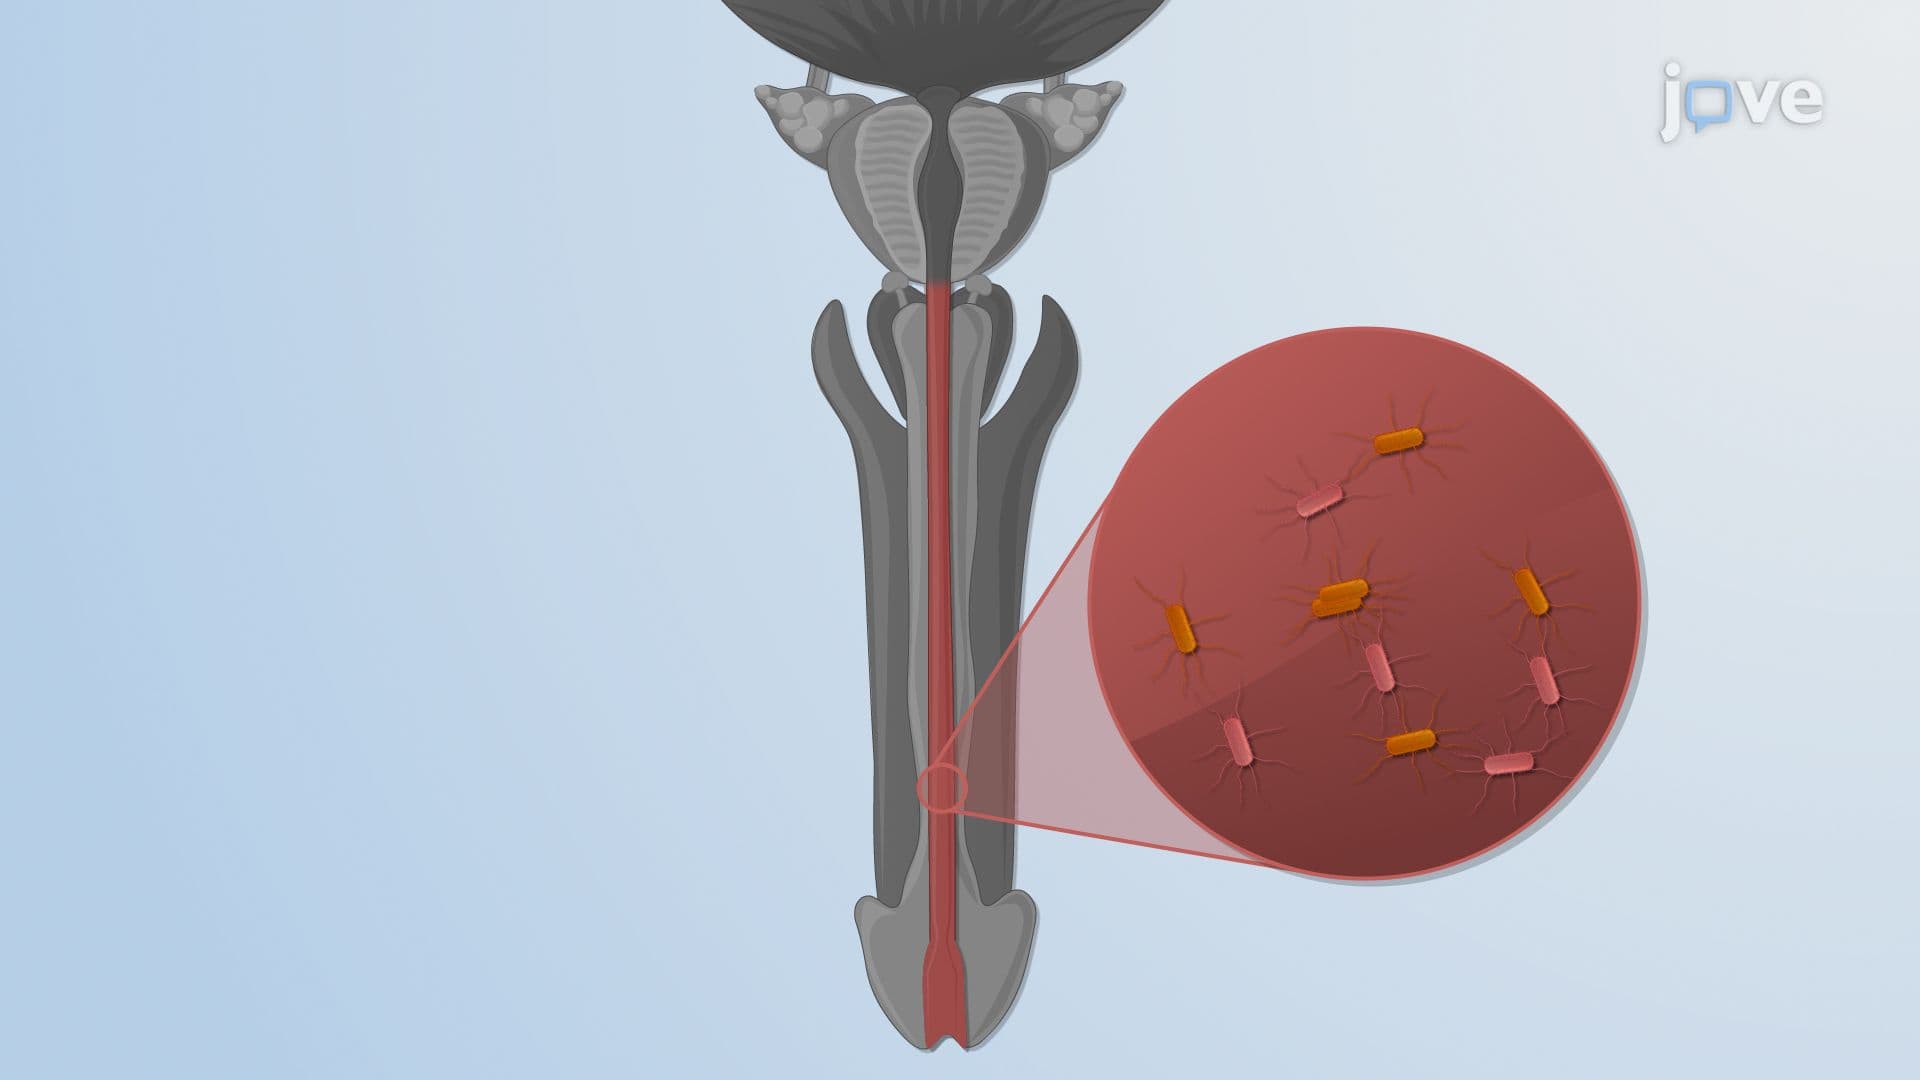 01:28
Microbiota of the Urogenital Tract
 01:20
Disorders of the Urinary System
Urinary tract infections (UTIs) are one of the most common urinary system disorders. They are caused by bacteria that enter the urethra and can spread to the bladder resulting in cystitis. Pyelonephritis is the result of a UTI that has ascended to the level of the...
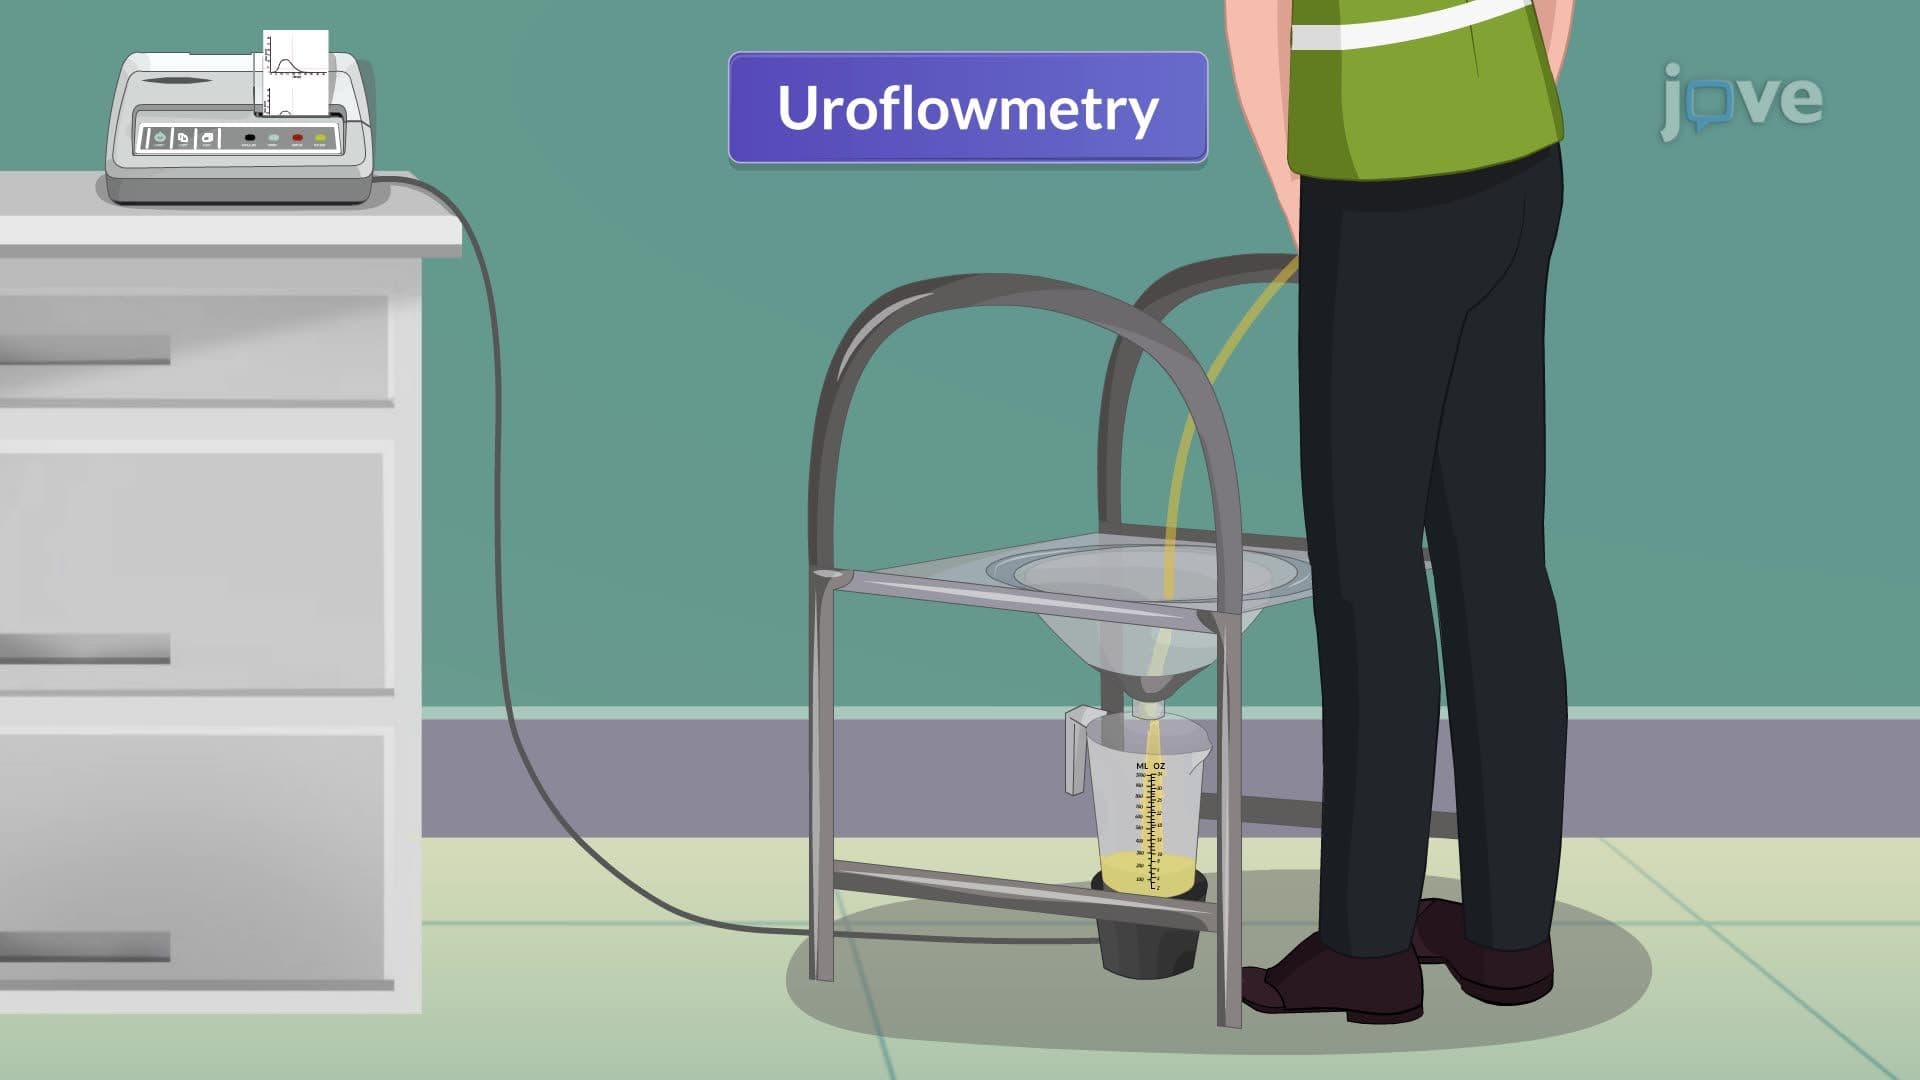 01:19
Urodynamic Studies: Uroflowmetry
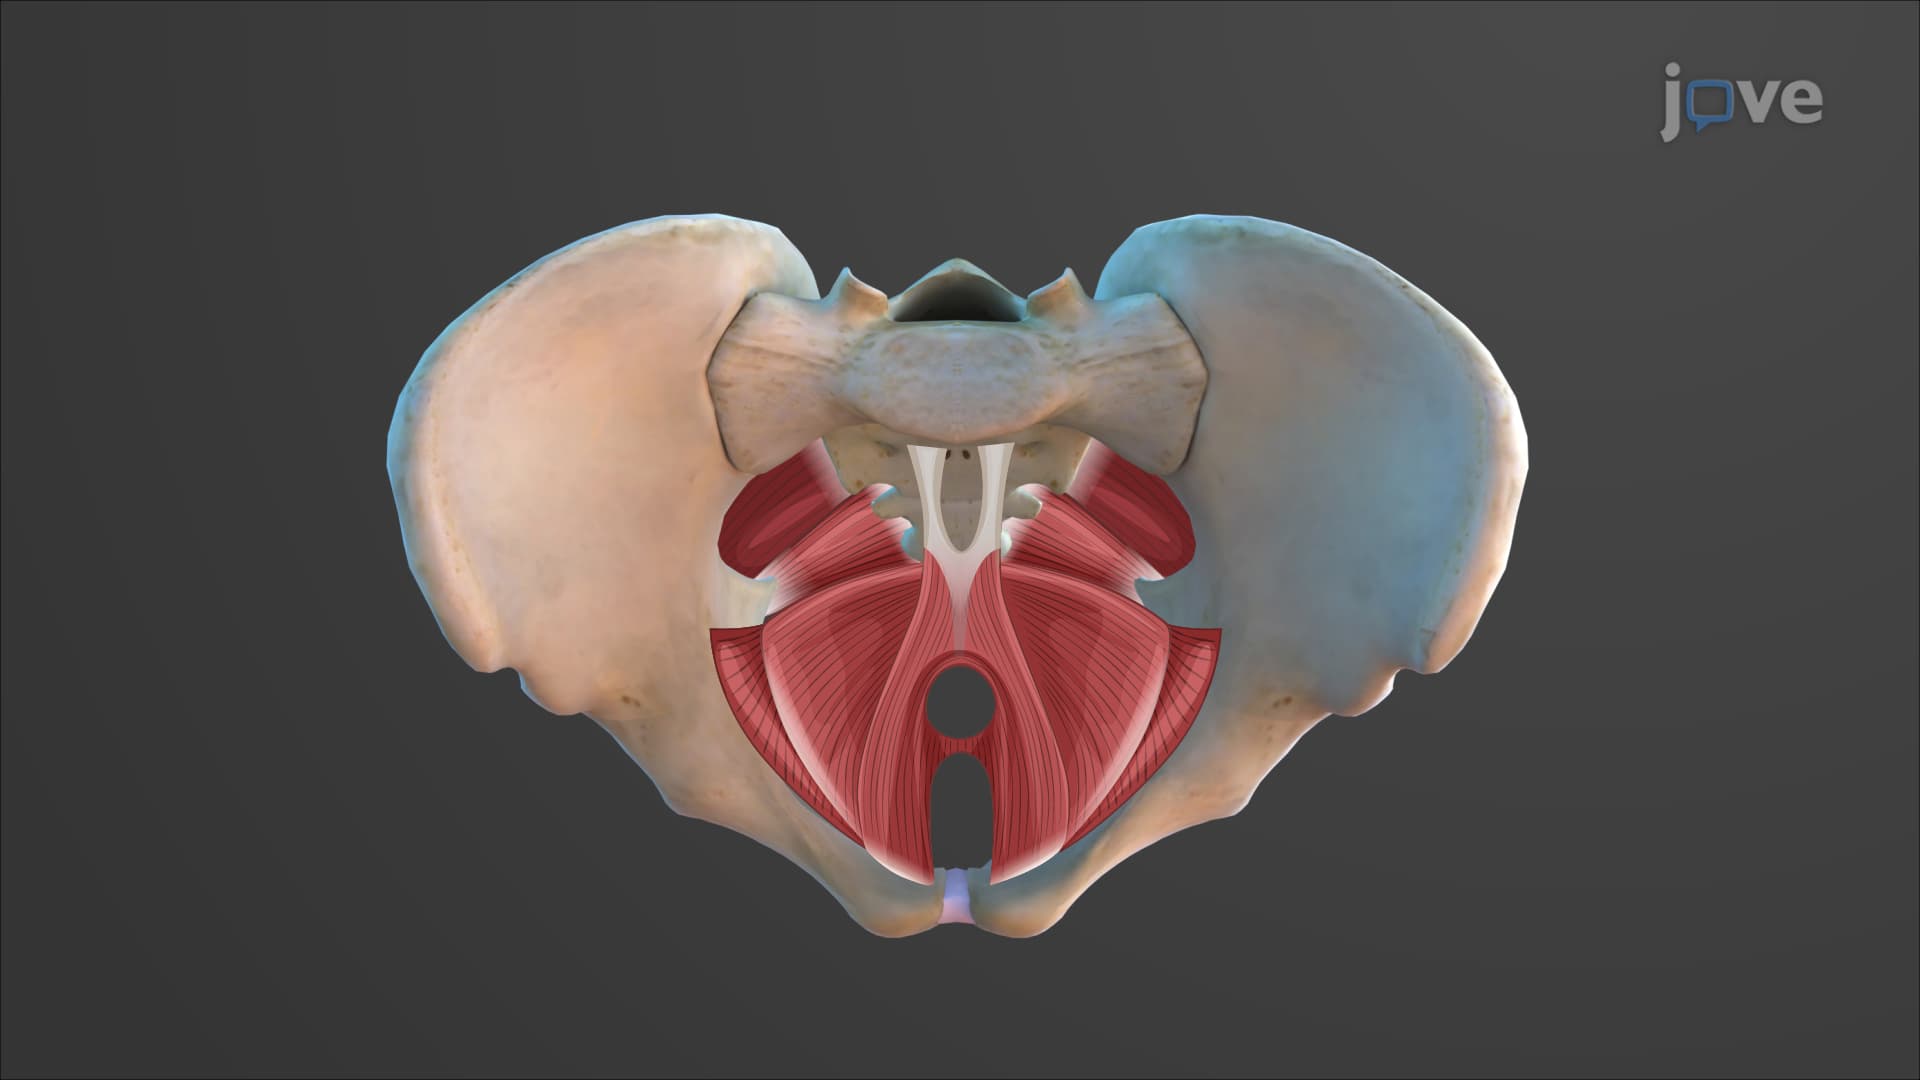 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...