Related Experiment Video
Updated: Jul 13, 2026


Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Regadenoson, a selective A2A adenosine receptor agonist, causes dose-dependent increases in coronary blood flow
Hsiao D Lieu1, John C Shryock, Gregory O von Mering
1Portola Pharmaceuticals, South San Francisco, Calif, USA.

Background:
Regadenoson is a selective A2A adenosine receptor agonist and vasodilator used to increase the heterogeneity of distribution of coronary blood flow during myocardial perfusion imaging. This study characterized the dose dependence of regadenoson-induced coronary hyperemia.
Methods And Results:
An open-label, dose-escalation study of regadenoson (10-500 microg, rapid intravenous bolus) was performed in 34 subjects; in 4 additional subjects, the effect of aminophylline to reverse the response to regadenoson was determined. Intracoronary peak blood flow velocity in either the left anterior descending or left circumflex artery was measured by continuous Doppler signal recording, heart rate, central aortic blood pressure, and adverse effects were recorded. Regadenoson increased peak blood flow velocity by up to 3.4-fold in a dose-dependent manner. The mean duration of the increase in flow velocity of 2.5-fold or greater caused by 400 to 500 microg of regadenoson was 2.3 to 2.4 minutes. Regadenoson (400-500 microg) increased heart rate by up to 21 +/- 6 beats/min and decreased systolic blood pressure (-5 +/- 8 mm Hg to -24 +/- 16 mm Hg) and diastolic blood pressure (-8 +/- 4 mm Hg to -15 +/- 14 mm Hg). Aminophylline (100 mg) attenuated the increase in peak flow velocity but not tachycardia caused by 400 microg of regadenoson.
Conclusion:
The results of this study demonstrate the utility of regadenoson as a coronary vasodilator for myocardial perfusion imaging.


Related Concept Videos
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:26
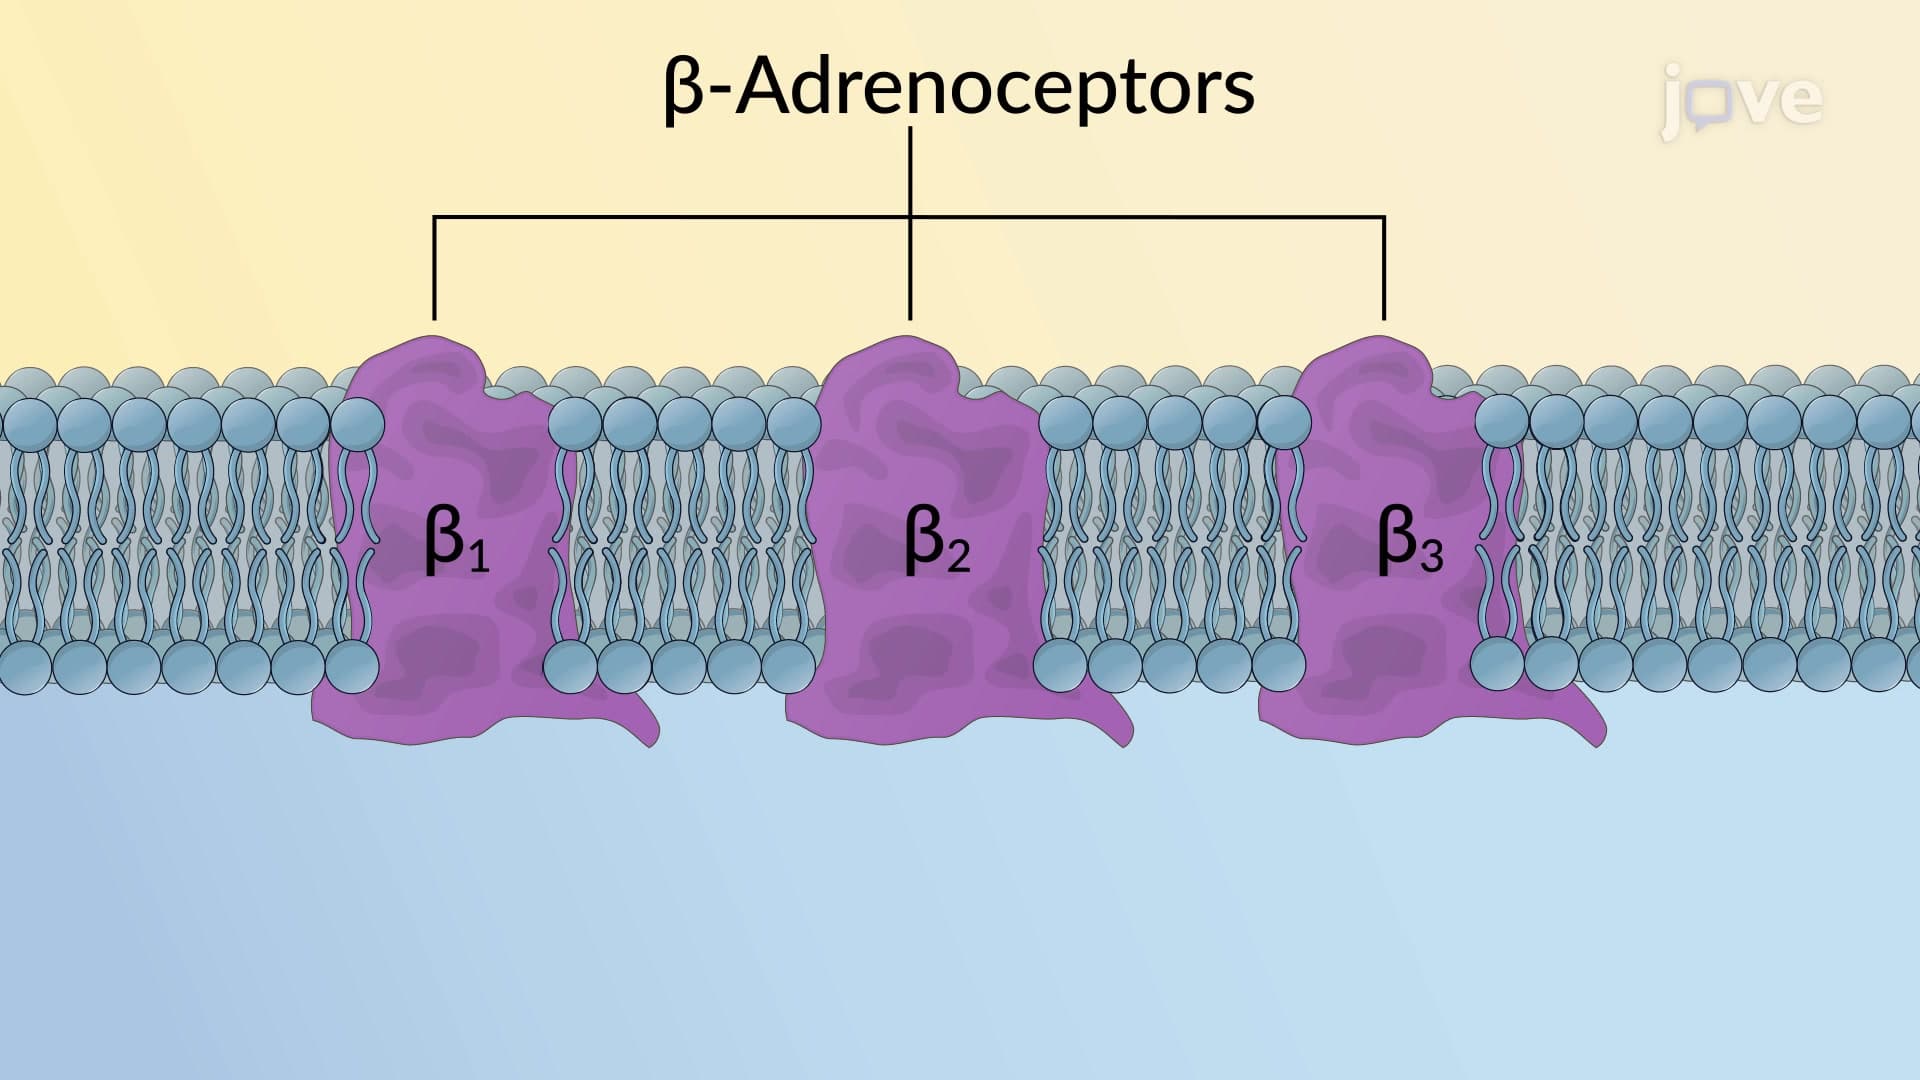
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:31
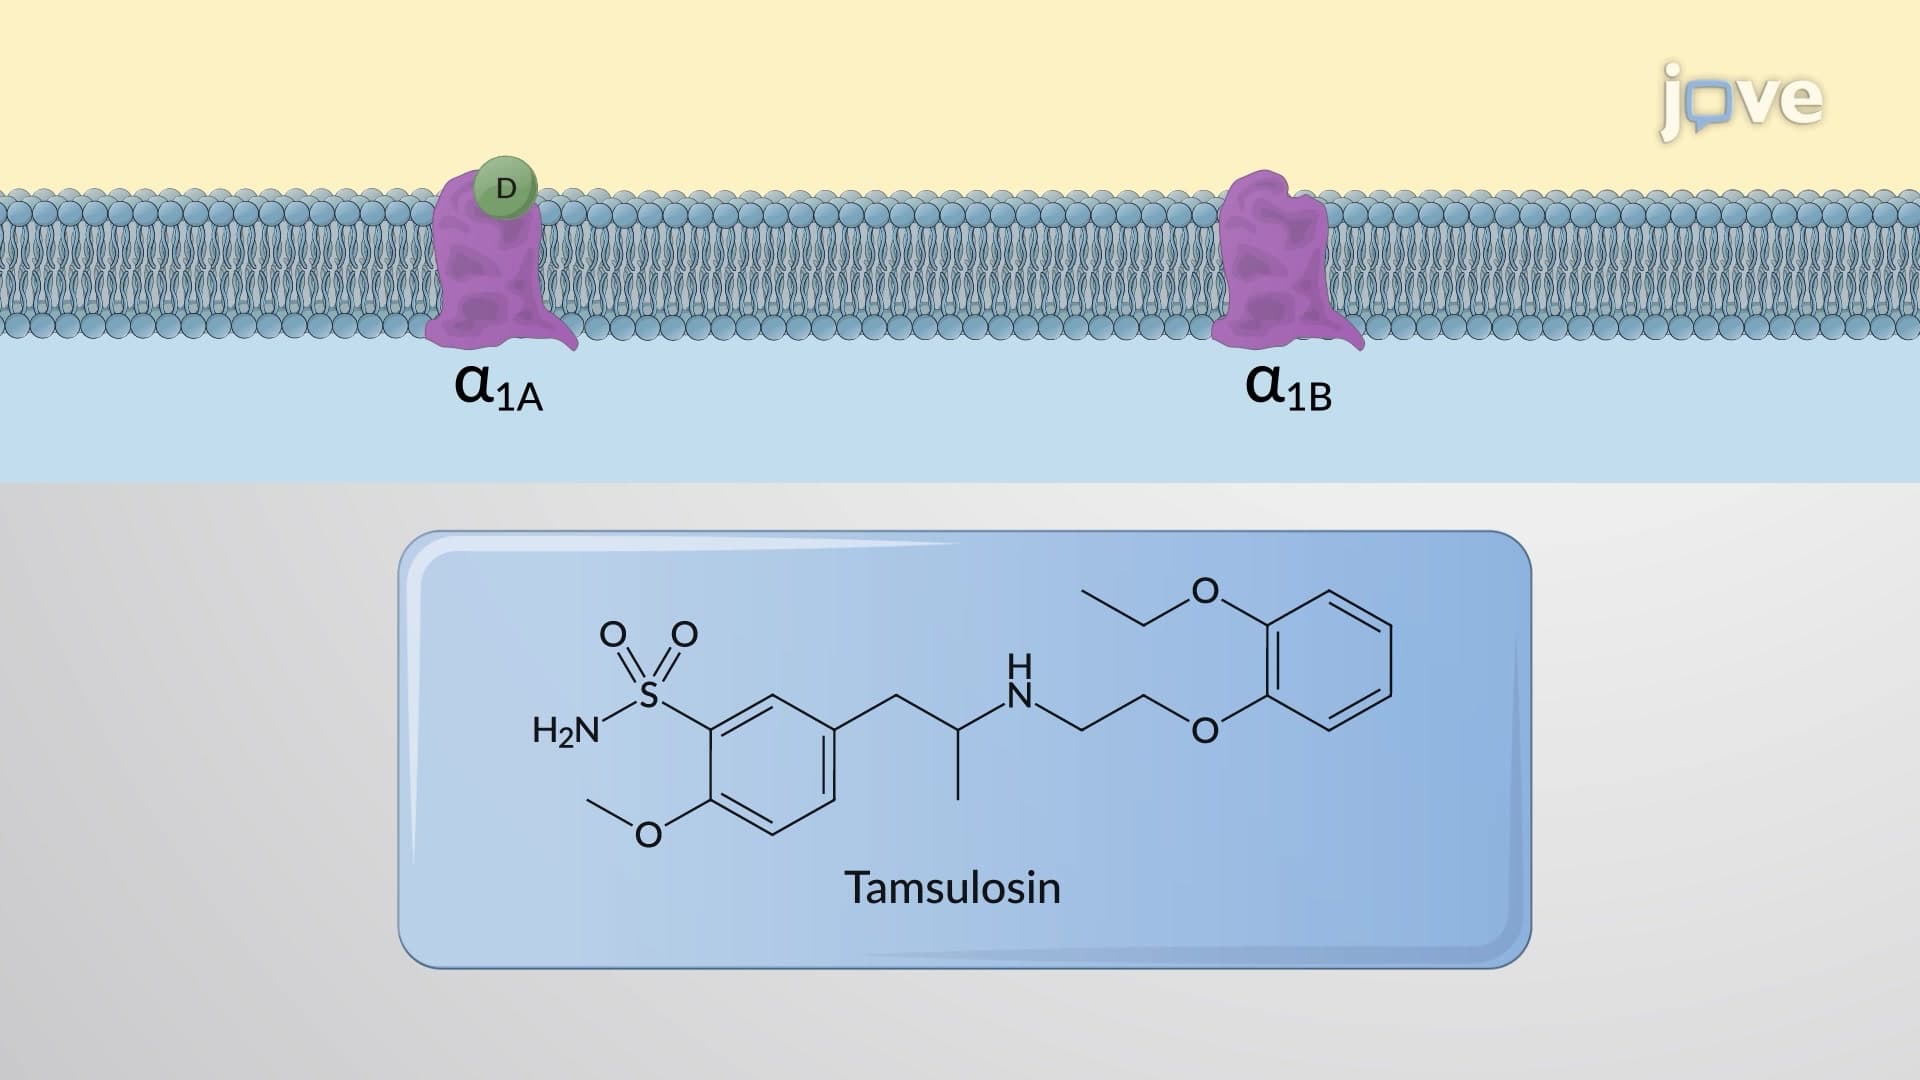
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...