Related Experiment Video
Updated: Jul 13, 2026


Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
Short-term and mid-term outcome of isolated symptomatic muscular calf vein thrombosis
Jean-Luc Gillet1, Michel R Perrin, François A Allaert
1Vascular Medicine Clinic, Bourgoin, France. gilletjeanluc@aol.com

Background:
Although muscular calf vein thrombosis (MCVT) is commonly seen in everyday practice, no treatment guidelines are available. This study evaluated short-term and mid-term outcome of isolated symptomatic MCVT.
Method:
We included prospectively and consecutively all patients referred to an outpatient clinic with isolated MCVT. Clinical signs were pain or edema, or both, of the calf. Diagnosis was established with duplex ultrasound (DUS) examination. Not completely occlusive and asymptomatic MCVTs were excluded. Patients were followed up clinically and with DUS at 1, 3, and 9 months, and up to 36 months. Anticoagulant therapy at curative dosage associated with compression was prescribed for 1 month and was extended for 2 additional months in case of incomplete recanalization at 1 month or if risk factors for venous thromboembolism (VTE) were present.
Results:
Included were 128 patients (78 women, 50 men) presenting with 131 MCVTs. Their mean age was 57.02 +/- 15.36 years (range, 20 to 87 years). Thrombus was present in the soleal veins (SoV) in 73 patients (55.7%) and in the medial gastrocnemius veins (MGV) in 58 (44.3%). Initial symptoms were isolated pain in the calf in 90 patients, isolated edema of the calf in six, and pain plus edema in 32. Anticoagulant therapy was prescribed in 53 patients (41.4%) for 1 month, in 59 (46.1%) for 3 months, and in 13 (10.2%) for >or=6 months. At baseline, nine pulmonary embolisms (7%), complicated with MCVT, were observed in six MGV patients (10.3%) and three SoV patients (4.1%; P = .18). Two nonfatal hemorrhagic events occurred. Three patients died during the follow-up after anticoagulant therapy had been discontinued. Recanalization of MCVT was considered complete at 1, 3, and 9 months in 54.8%, 84.7%, and 96% of cases, respectively, with no significant difference between the MGV and the SoV groups. Twenty-nine VTE symptomatic recurrences (PE, n = 6; DVT including MCVT, n = 23) were observed in 24 patients (18.8%), with similar figures in both thrombosis groups: none at 3 months, 11 between 3 and 9 months and 18 between 9 and 36 months. No extension of the MCVT or a recurrence of VTE was observed in patients treated with anticoagulant therapy. Twelve cases of superficial thrombophlebitis occurred during the follow-up period.
Conclusion:
This study confirms the place of MCVT in VTE disorders. Pulmonary embolism at the MCVT initial diagnosis was not rare, and mid-term follow-up (mean, 26.7 months) revealed that 18.8% of patients had at least one VTE recurrence. The treatment of acute MCVT needs to be standardized because no guidelines currently exist.


Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:15
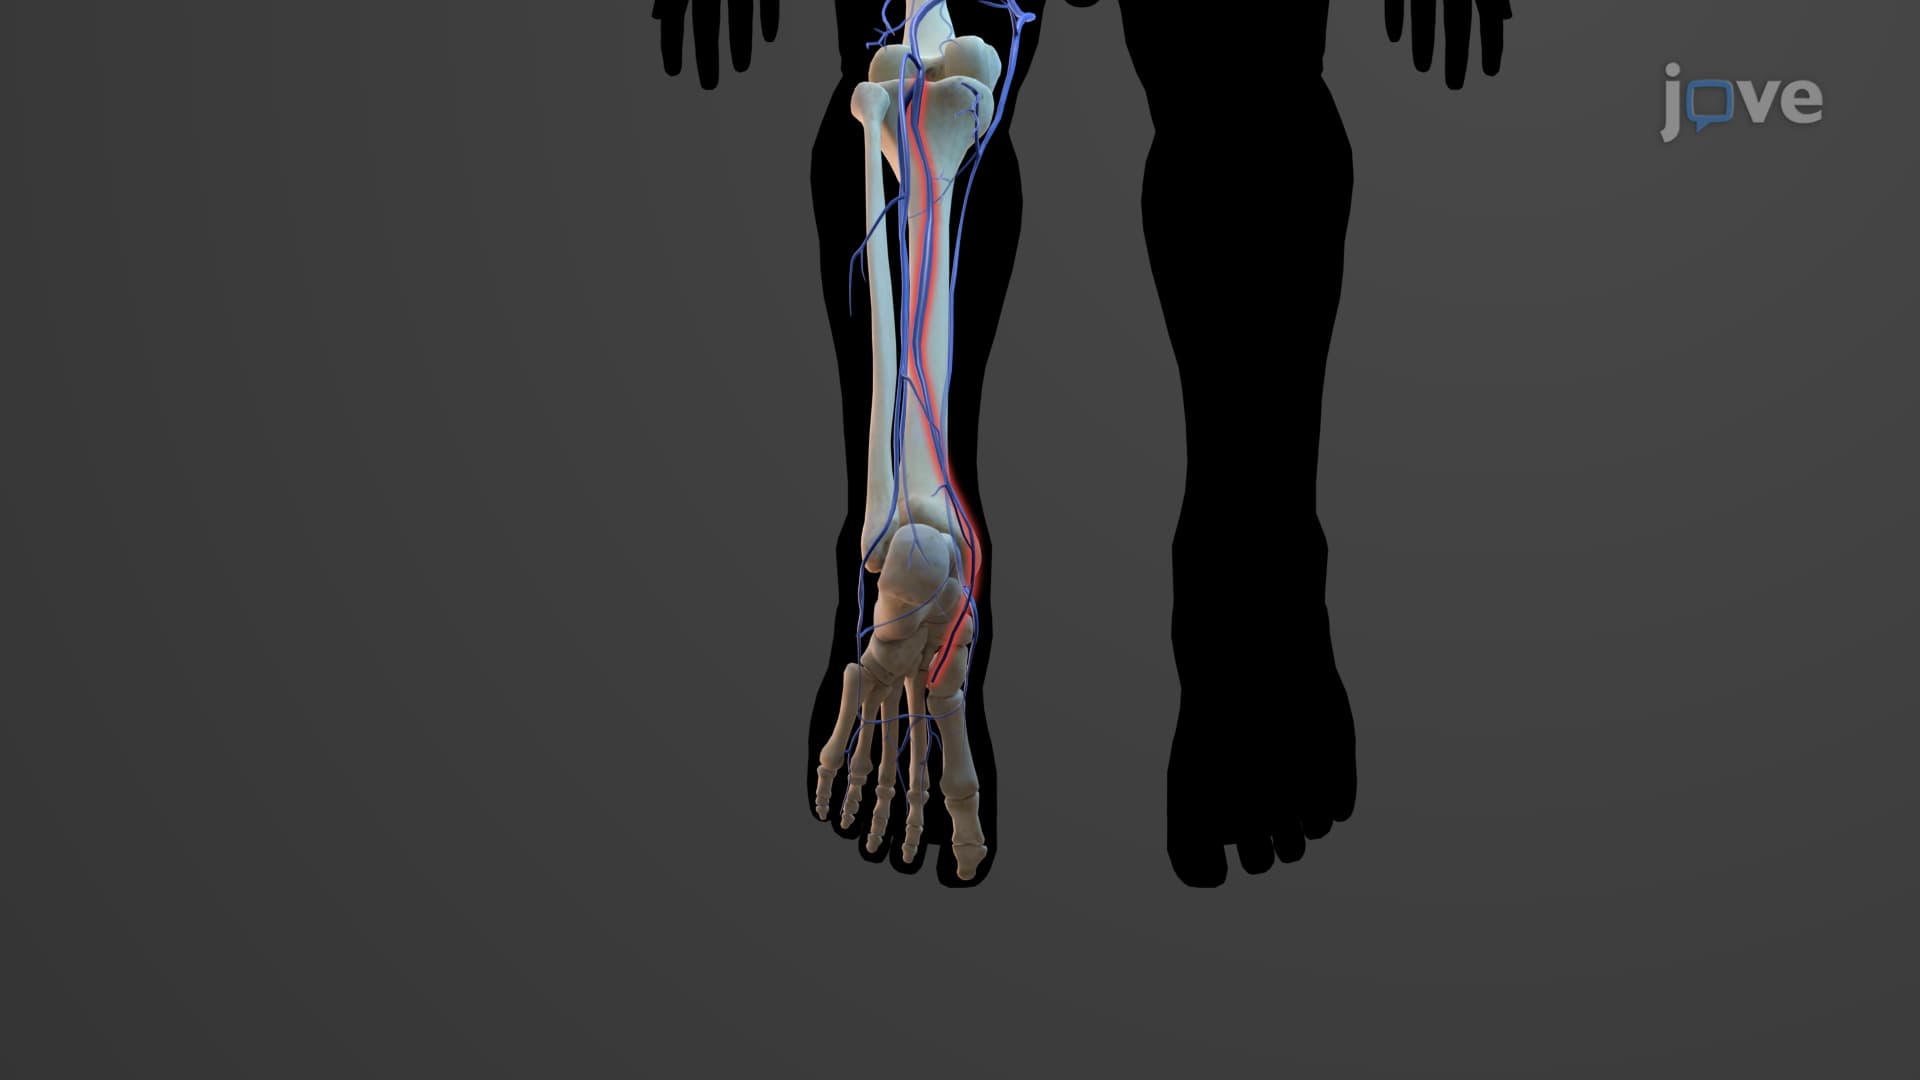
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...
 01:26
Varicose Veins I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...