A rapidly advancing mediastinal mass--overcoming tracheobronchial obstruction
Related Experiment Video
Updated: Jul 13, 2026
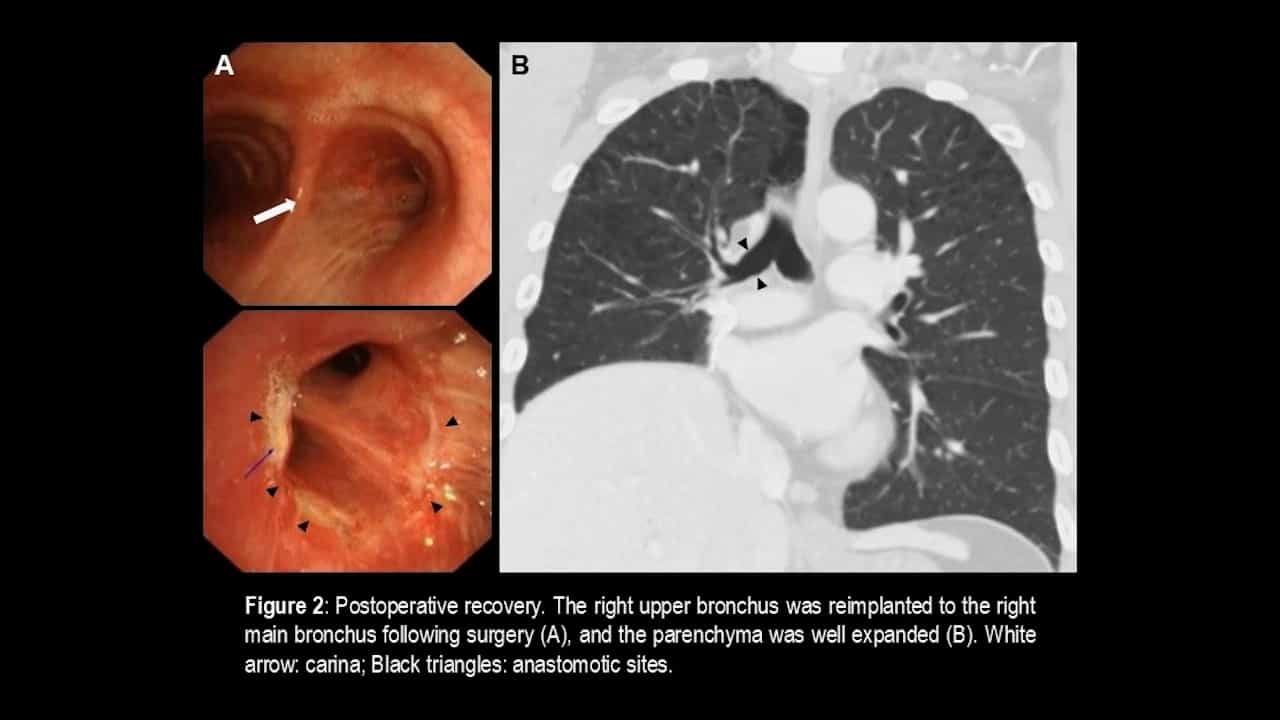
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Ian Frost1, Rob Ross-Russell, Sam Bass
1Department of Anaesthesia, Addenbrooke's Hospital, Cambridge University Hospitals NHS Foundation Trust, Cambridge, UK. ian@ianfrost.wanadoo.co.uk

Insights
A modified endotracheal tube with a proximal
Area of Science:
- Pediatric Oncology
- Thoracic Surgery
- Anesthesiology
Background:
- Mediastinal T-cell non-Hodgkin lymphoma can cause rapid airway obstruction in children.
- Pediatric intensive care unit (PICU) management is crucial for severe cases.
- Tracheal intubation is a primary intervention for airway compromise.
Observation:
- A 7-year-old boy experienced critical airway obstruction due to mediastinal T-cell non-Hodgkin lymphoma.
- Unilateral bronchial involvement caused gas trapping and severe pulmonary hyperinflation.
- Standard intubation techniques were insufficient, necessitating advanced airway management.
Findings:
- Endobronchial advancement of a tracheal tube temporarily relieved hyperinflation.
- One-lung ventilation was poorly tolerated, posing a significant challenge.
- A novel proximal 'Murphy's eye' modification to the endotracheal tube enabled contralateral lung ventilation.
Implications:
- This case highlights a unique solution for managing complex pediatric airway obstruction.
- The modified endotracheal tube technique offers a potential strategy for similar critical scenarios.
- This innovative approach expands the armamentarium for pediatric thoracic and airway management.
Abstract:
We report the case of a 7-year-old boy who presented with rapidly advancing airway obstruction secondary to mediastinal T-cell non-Hodgkins lymphoma. His brisk deterioration required transfer to the pediatric intensive care unit and intubation of the trachea. Unforeseen unilateral bronchial involvement led to gas trapping and critical pulmonary hyperinflation. Endobronchial advancement of the tracheal tube beyond the bronchial obstruction relieved pulmonary hyperinflation but subsequent one lung ventilation was poorly tolerated. We report the manufacture of a proximal 'Murphy's eye' which allowed ventilation of the contralateral lung to proceed. To the best of our knowledge this is the first time that this technique has been described in a pediatric patient.
Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:08
Pneumothorax II: Pathophysiology
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies