Related Experiment Video
Updated: Jul 13, 2026


Determination of Cardiac Output in a Porcine Model for Ex Vivo Pulmonary Perfusion
Published on: June 28, 2024
Lack of agreement between thermodilution and electrical velocimetry cardiac output measurements
Matthias Heringlake1, Ulrich Handke, Thorsten Hanke
1Department of Anesthesiology, University of Luebeck, Ratzeburger Allee 160, 23538 Luebeck, Germany. heringlake@t-online.de

Objective:
The modified algorithm for the non-invasive determination of cardiac output (CO) by electrical bioimpedance-electrical velocimetry (EV)-has been reported to give reliable results in comparison with echocardiography and pulmonary arterial thermodilution (PA-TD) in patients either before or after cardiac surgery. The present study was designed to determine whether EV-CO measurements reflect intraindividual changes in CO during cardiac surgery.
Design:
Prospective, observational study.
Setting:
Operating room (OR) and intensive care unit (ICU) of a university hospital.
Patients:
Twenty-nine patients undergoing elective cardiac surgery.
Interventions:
None.
Measurements:
CO was determined simultaneously by PA-TD and EV after induction of anesthesia (t1) and 4.9+/-3.5 h after ICU admission (t2).
Results:
TD-CO was 3.9+/-1.4 and 5.4+/-1.1 l/min at t1 and t2 (p < 0.0001). EV-CO was 4.3+/-1.1 and 4.9+/-1.5 l/min at t1 and t2 (p = 0.013). Bland-Altman analysis showed a bias of -0.4 l/min and 0.4 l/min and a precision of 3.2 and 3.6 l/min (34.3% and 67.4%) at t1 and t2, respectively. Analysis of the individual pre- to postoperative changes in CO with both methods revealed bidirectional changes in n = 12 patients and unidirectional changes with a difference greater than 50% and less than 50% in n = 9 and n = 8 patients, respectively.
Conclusions:
The disagreement between PA-TD and EV-CO measurements after anesthesia induction and after ICU admission, as well as the fact that thoracic bioimpedance did not adequately reflect pre- to postoperative changes in CO, questions the reliability of EV-CO measurements in cardiac surgery patients and contrasts sharply with previous studies.
Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:19
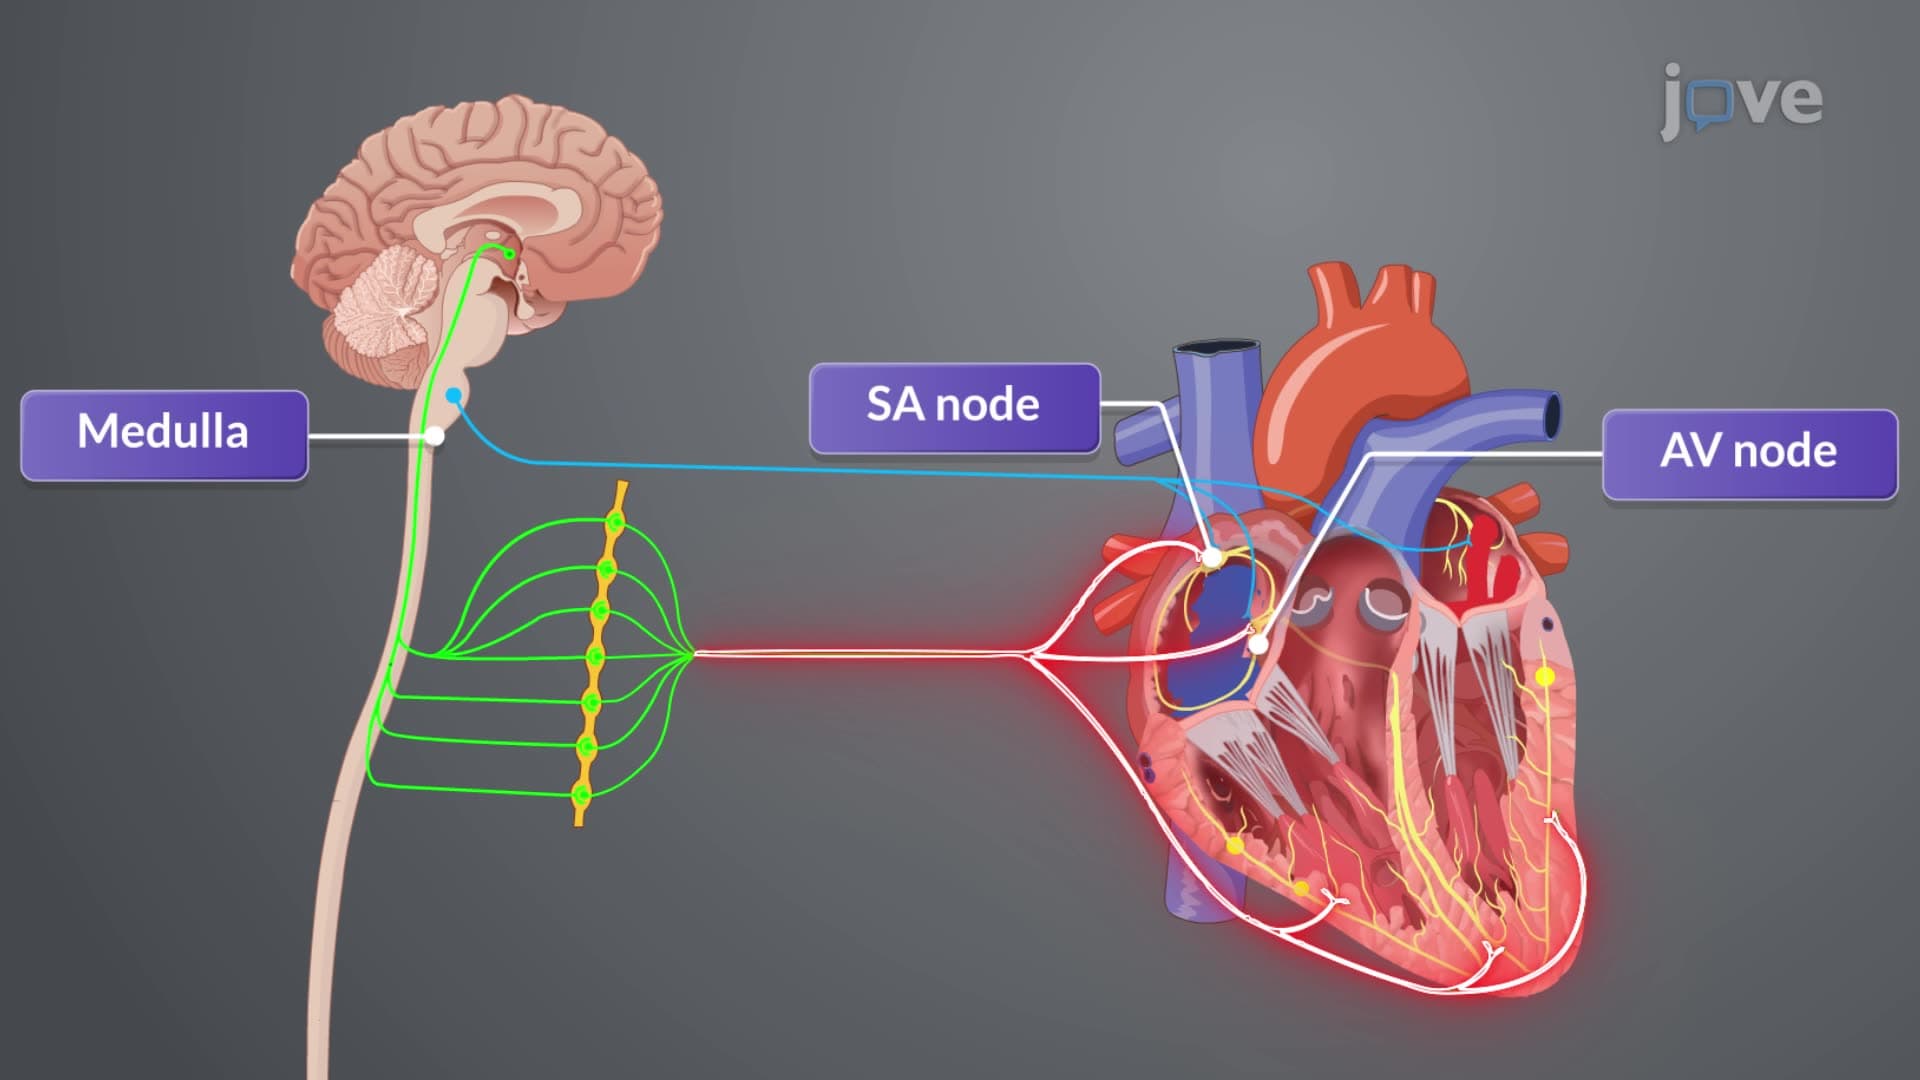
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac output averages...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be met...
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...