Related Experiment Video
Updated: Jul 13, 2026
The Rigid Tube as an Alternative in Controlling the Problematic Airway
Published on: June 6, 2020
Rigid spine syndrome: a radiologic and manometric study of the pharynx and esophagus
1Department of Neurology, University of Pretoria, Pretoria, South Africa. pstuebge@med.cornell.edu

Abstract:
The rigid spine syndrome (RSS) is not a recognized cause of dysphagia. The "vacuolar variant" of RSS causes mild, generalized, and slowly progressive weakness. Respiratory evaluation detected severe restrictive chest wall defect and significant respiratory muscle weakness. We identified nine patients at our Neuromuscular Clinic over a period of years. The aim of this evaluation was to ascertain whether pharyngoesophageal dysfunction caused cough (2/9), intermittent oropharyngeal dysphagia (4/9), and aspiration pneumonia (3/9). Pharyngeal and esophageal functions were evaluated separately by conventional cineradiography and intraluminal esophageal manometry over a one-year study period. An age- and gender-matched volunteer group without swallowing complaints partook in the manometric component of the study. There were seven male and two female patients. The mean age of patients was 19.1 years (17.8 years for controls), and the age range was 11-36 years (13-32 years for controls). The mean disease duration was 17.2 years (range=8-31 years). Patients were commonly underweight (7/9). Cineradiology detected abnormal swallow physiology of pharyngeal striated muscle (1/9) and of esophageal smooth muscle (2/9). Mean manometric pressures in patients were not significantly different from control data. Manometry detected "nonspecific" contractility abnormalities (3/9) that were not reflected in the mean data. The relative lack of instrumental findings suggested minor upper alimentary tract dysmotility in patients with the RSS. The myopathy that underlies this syndrome likely caused dysfunction of the striated muscle of the pharyngeal constrictors and upper esophageal sphincter. The documented abnormalities of esophageal smooth muscle motility were nonspecific and tenuously associated with the muscle disorder. The incongruity between complaints of intermittent dysphagia and study results was perhaps due to transient pharyngoesophageal dysmotility, altered swallowing mechanics of limited cervical spine mobility, altered swallowing perception after previous intubation/tracheostomy, or a "functional" upper intestinal complaint.
Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:16
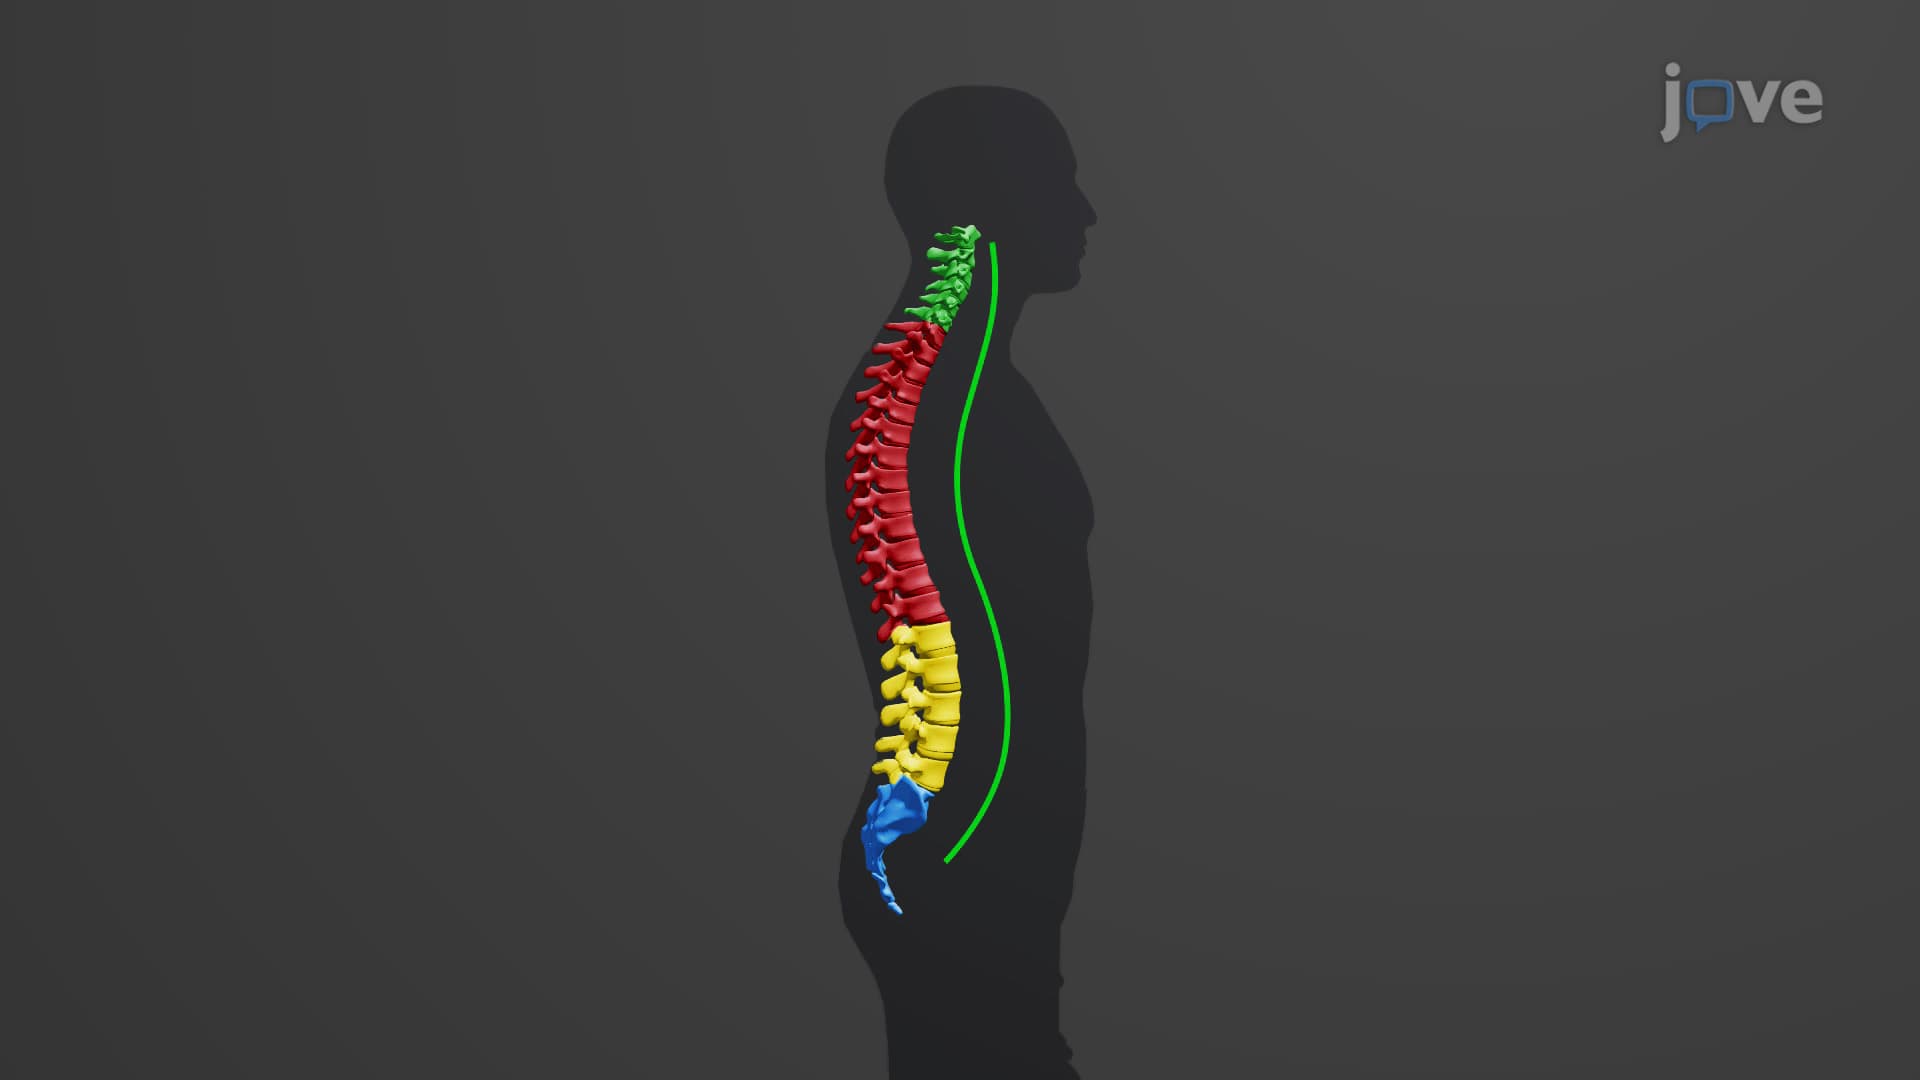
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:25
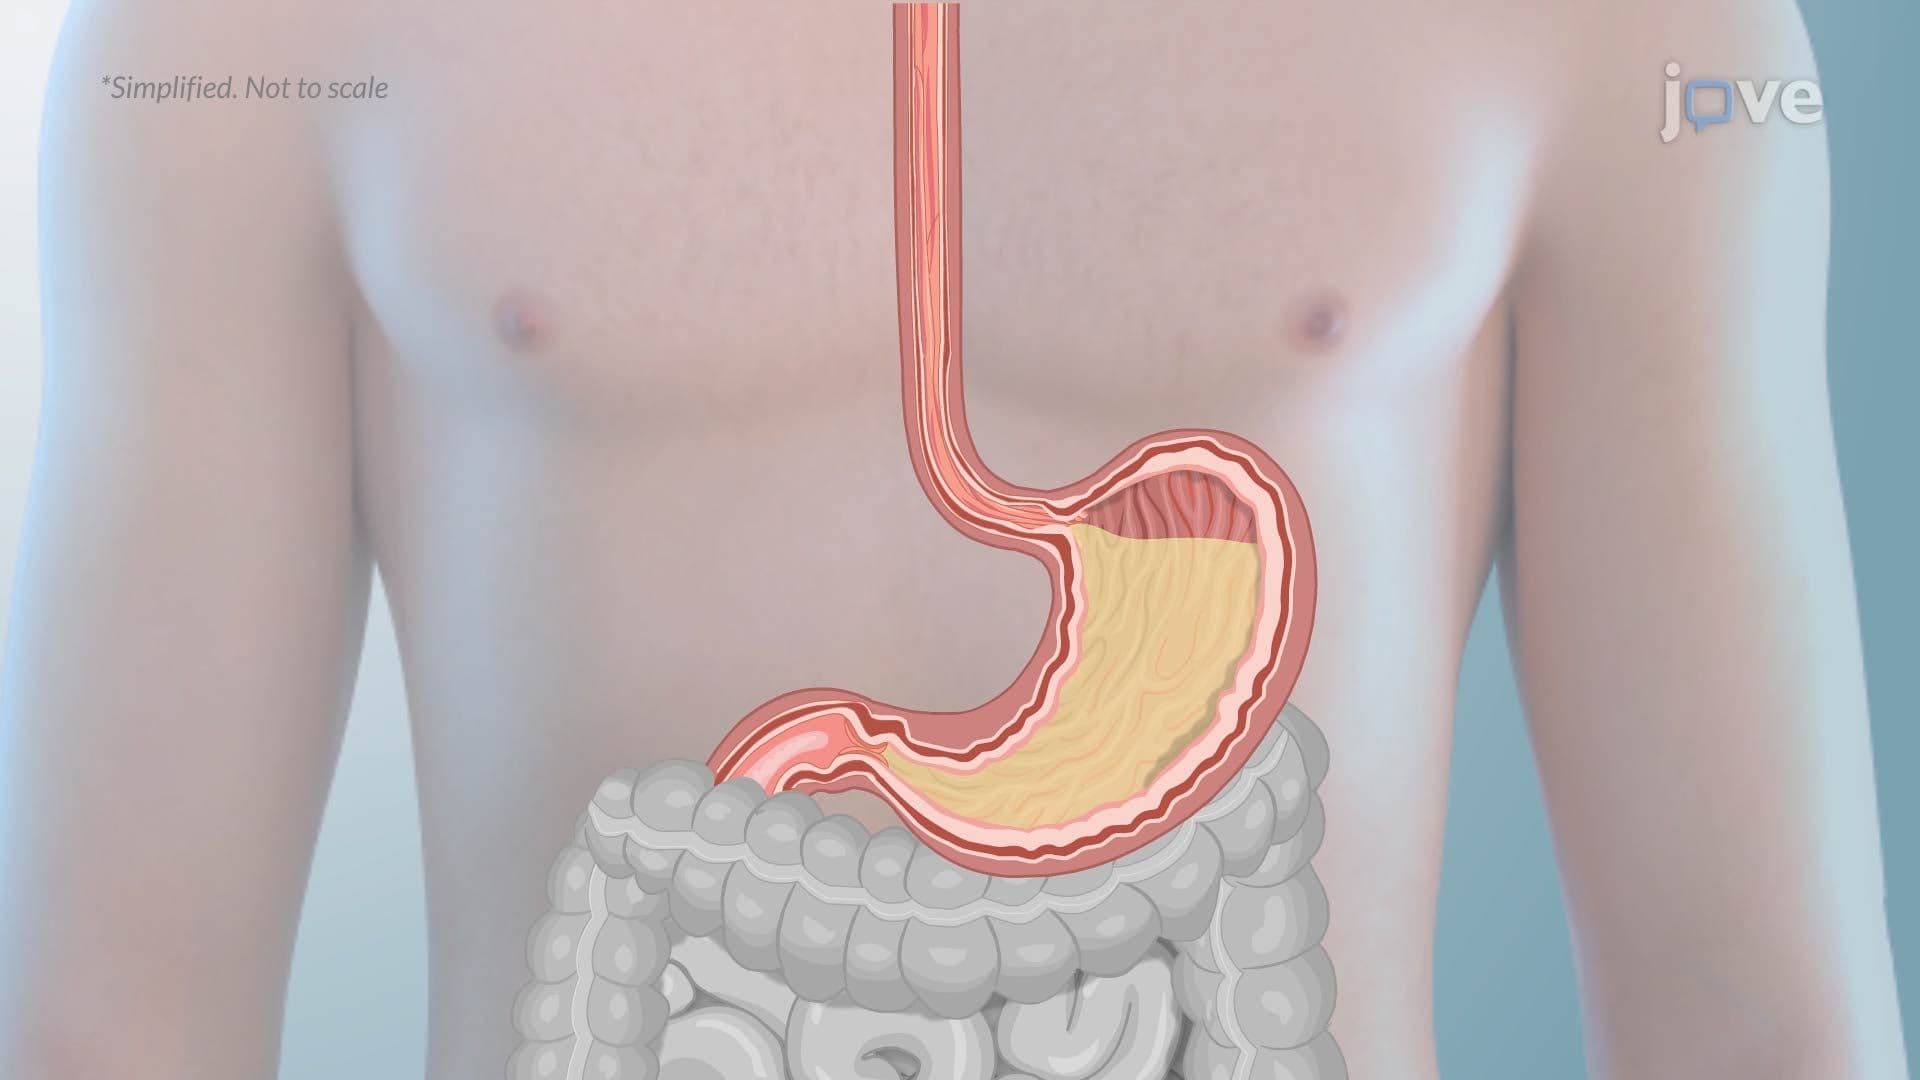
Gastroesophageal Reflux Disease
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...