Related Experiment Video
Updated: Jan 27, 2026
Author Spotlight: Assessing the Feasibility of Using Amplitude-Integrated EEG During Neonatal Transport
Published on: June 21, 2024
[A preliminary study on diagnosis and grading of hypoxic-ischemic brain damage of premature infants]
Li-Wen Chang1, Jing Liu, Wen-Bin Li
1Department of Pediatrics, Tongji Hospital Affilitiated to Tongji Medical College, Huazhong University of Science and Technology, Wuhan 430030, China. changliwen65@hotmail.com

Insights
Hypoxic-ischemic brain damage (HIBD) criteria for premature infants are proposed, as current term infant guidelines are unsuitable. This study establishes new diagnostic standards and a grading system for HIBD in neonates.
Area of Science:
- Neonatal Neurology
- Pediatric Neuroimaging
- Perinatal Medicine
Background:
- Hypoxic-ischemic brain damage (HIBD) is a significant cause of mortality and long-term neurological deficits in premature infants.
- Current diagnostic criteria for HIBD are primarily established for term infants and are not fully applicable to the unique physiology of premature neonates.
- The lack of specific diagnostic criteria hinders timely and accurate management of HIBD in premature infants.
Purpose of the Study:
- To explore and establish specific diagnostic criteria for HIBD in premature infants.
- To develop a principle for grading the severity of HIBD in premature infants.
- To evaluate the efficacy of neuroimaging techniques in diagnosing HIBD in this population.
Main Methods:
- Retrospective analysis of clinical data from 453 premature infants diagnosed with HIBD using term infant criteria.
- Inclusion of medical history, clinical manifestations, laboratory results, and neuroimaging findings (cranial CT and ultrasound).
- Development of preliminary diagnostic criteria based on clinical and pathological features specific to premature infant brain injury.
Main Results:
- A preliminary set of diagnostic criteria for premature infant HIBD was developed, with 76% of the cohort meeting these criteria.
- Evidence of hypoxia (decreased PaO2/SaO2) was noted in 208 infants, and decreased base excess (BE) in 138.
- Cranial ultrasound demonstrated high sensitivity (87.9%) and specificity (100%) for HIBD diagnosis, outperforming cranial CT (100% sensitivity, 17.8% specificity).
Conclusions:
- The diagnostic criteria for HIBD in term infants are not appropriate for premature infants.
- Proposed diagnostic criteria include evidence of hypoxia, neurological symptoms/signs, specific imaging findings (edema, GMH-IVH, PVL, infarction), and exclusion of other causes.
- A grading principle is proposed: Mild HIBD (Grade I-II GMH-IVH/PVL) and Severe HIBD (Grade III-IV GMH-IVH/PVL) based on cranial ultrasound findings.
Objective:
Hypoxic-ischemic brain damage (HIBD) occurs frequently in premature infants, resulting death or neurological sequela in some survivors. Up to now, however, there are no diagnostic criteria for this disease. The aim of this study was to explore the diagnostic criteria and the grading principle for HIBD of premature infants.
Methods:
The clinical data of 453 premature infants who were diagnosed with HIBD based on the diagnostic criteria for HIBD of term infants, including medical history, clinical manifestations, laboratory results and imaging findings, were studied retrospectively.
Results:
A preliminary diagnostic criteria for HIBD of premature infants was propounded based on clinical and pathologic features of brain damage of premature infants. Of the 453 premature infants, 346 (76%) matched the diagnostic criteria. Of the 346 cases, PaO2 (42.21 +/- 8.33 mmHg) and /or SaO2 (68.49 +/- 5.19%) decreased in 208 patients and the BE value (-10.86 +/-3.41 mmol/L) decreased in 138 patients. The sensitivity and specificity of cranial computer tomography for the diagnosis of HIBD in premature infants was 100% and 17.8%, respectively. Cranial ultrasound displayed a sensitivity of 87.9% and specificity of 100% for the diagnosis of HIBD in premature infants.
Conclusions:
The diagnostic criteria used for HIBD for term infants is not suitable for premature infants. This study puts forward the reference diagnostic criteria of premature HIBD as following: 1) evidence of hypoxia; 2) neurological symptoms and signs; 3) imaging findings: severe brain edema, germinal matrix intraventricular hemorrhage (GMH-IVH), periventricular leukomalacia (PVL), or brain infarction, and/or the resistance index (RI) > 0.75 or < 0.55 showed by cranial ultrasound; 4) Brain damage caused by infection, electrolyte disturbance and congenital metabolic disease was excluded. The grading principle of premature HIBD is proposed as follows: MILD HIBD when cranial ultrasound shows grade I-II of GMH-IVH or PVL, and SEVERE HIBD when cranial ultrasound shows grade III-IV of GMH-IVH or PVL.

Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:19
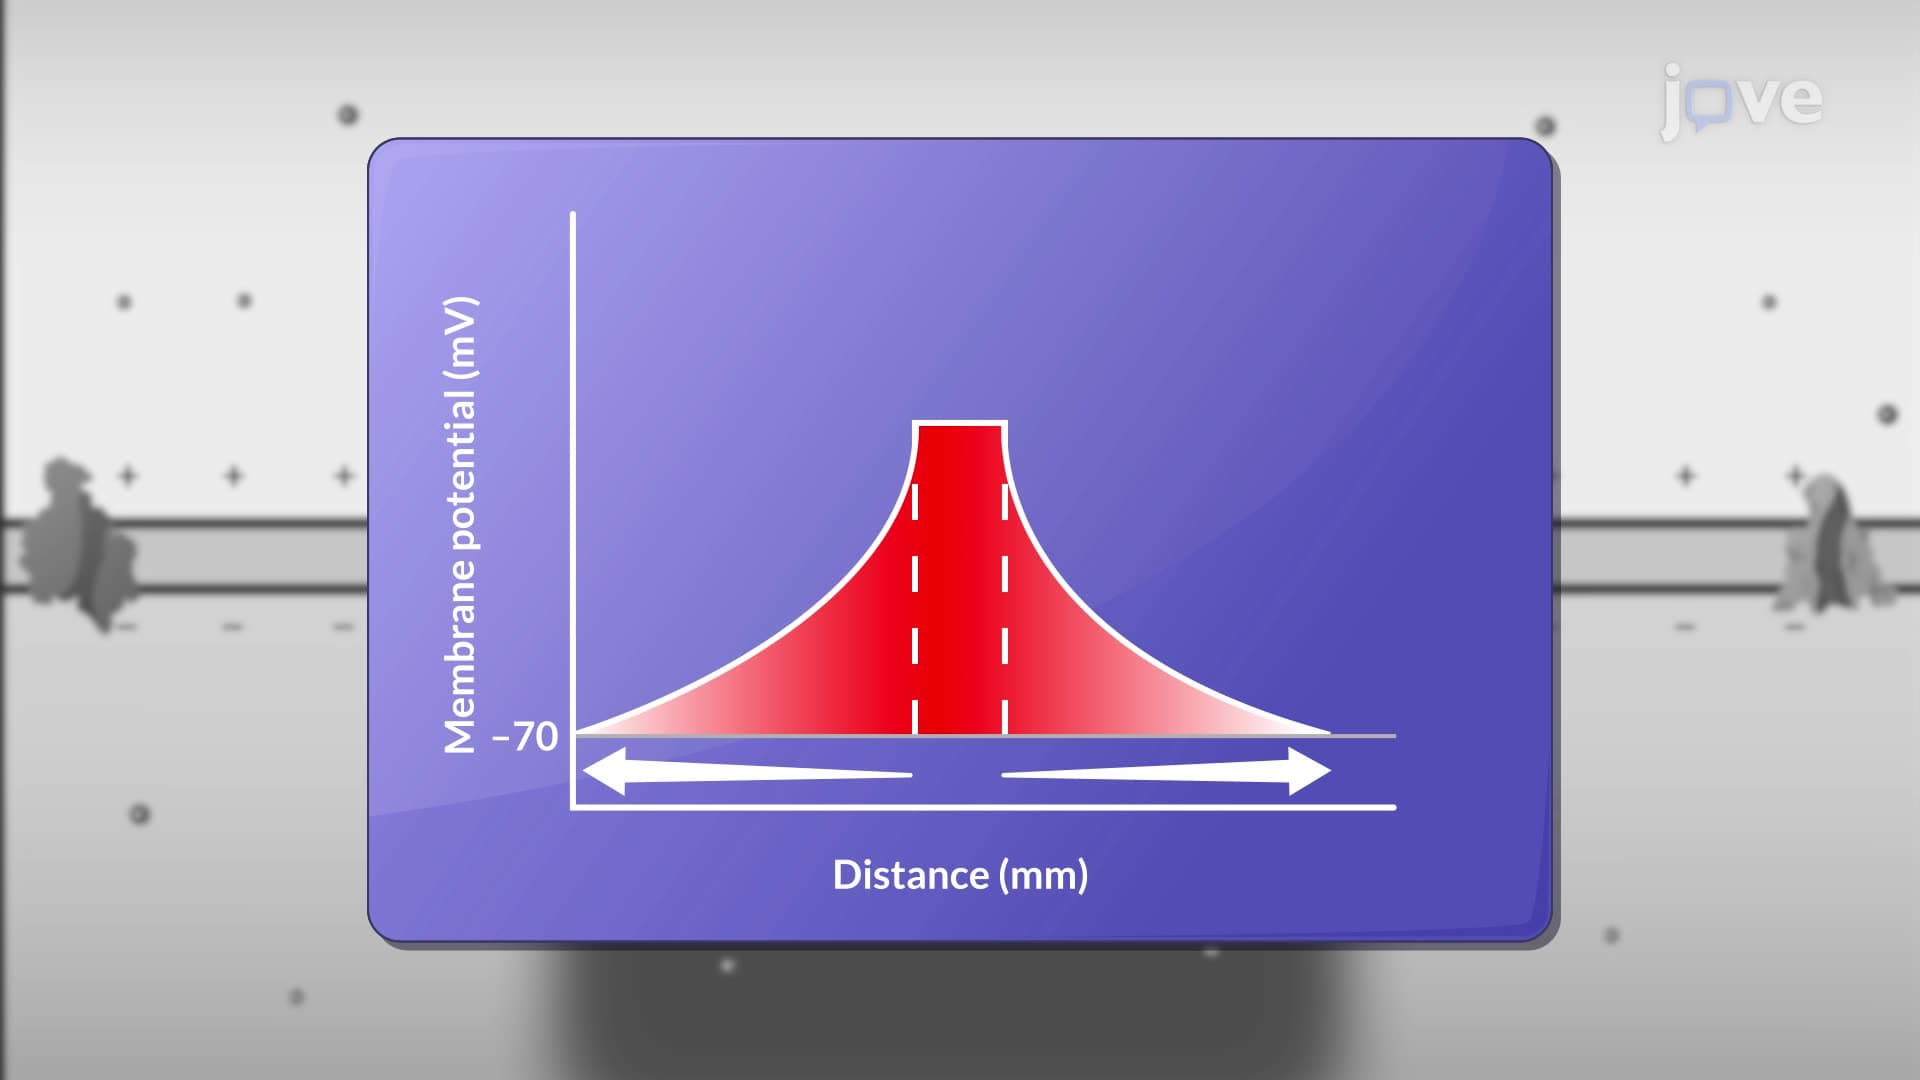
Graded Potential
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 01:15
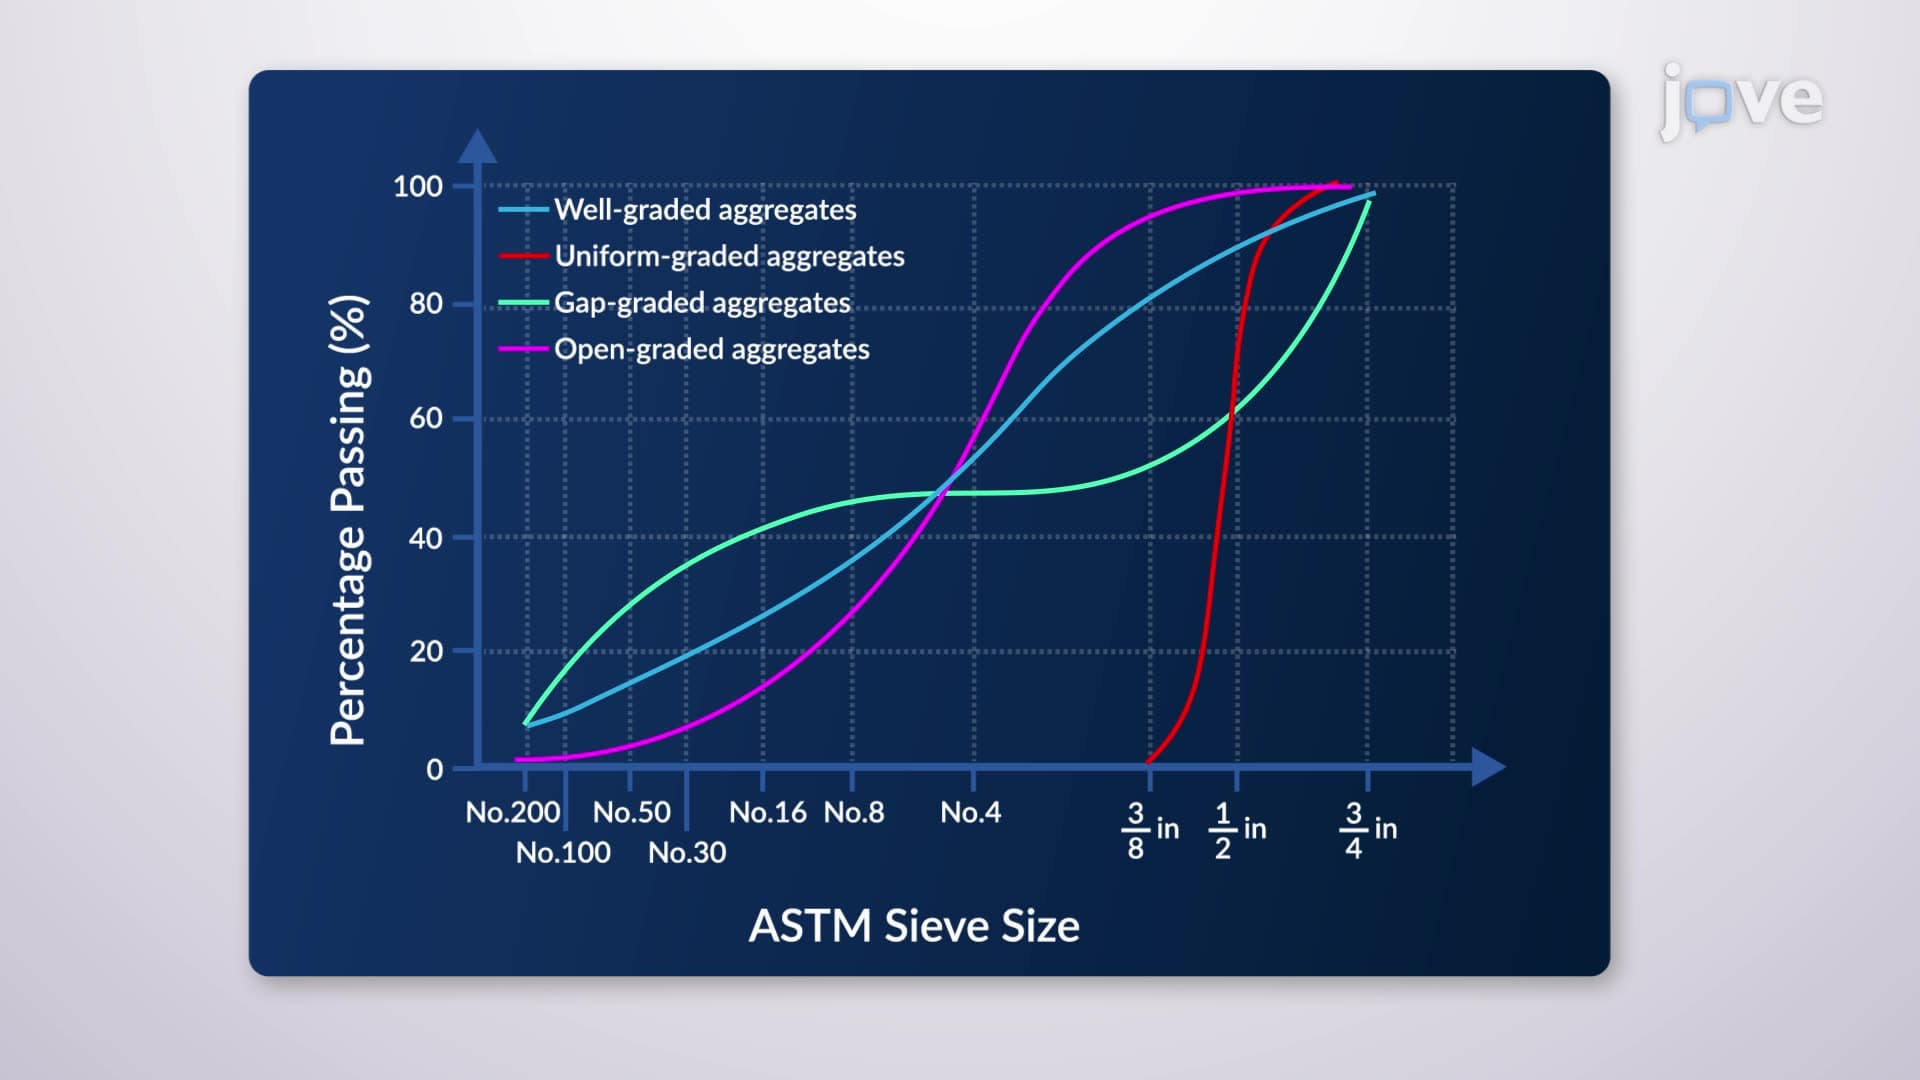
Types of Aggregate Grading
Well-graded aggregates include a complete range of necessary size fractions that fit together to create a dense matrix with minimal voids, represented by a smooth, continuous gradation curve. This type of grading ensures good...
 01:19
Sieve Analysis and Grading Curves
 01:22
Nursing Diagnosis
The nursing diagnosis focuses on evidence-based...
 01:10
Documentation of Nursing Diagnosis
In some settings, data-driven computerized decision support systems are in place, allowing for more accurate nursing diagnoses. The database within one of these systems includes diagnostic labels defining characteristics, activities, and indicators for nursing. A nurse enters...