Related Experiment Video
Updated: Jul 13, 2026
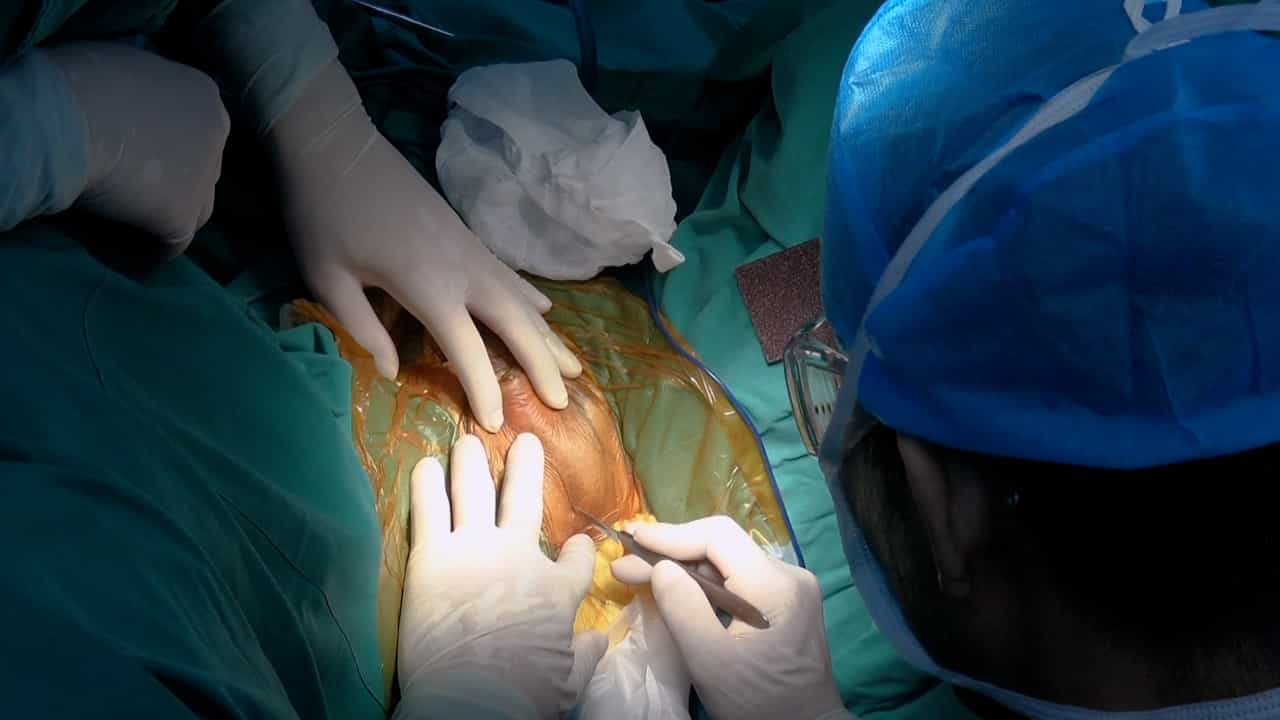
Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Artificial urinary sphincters placed after posterior urethral distraction injuries in children are at risk for
Richard A Ashley1, Douglas A Husmann
1Department of Urology, Mayo Clinic, Rochester, Minnesota 55905, USA.

Insights
Artificial urinary sphincter placement for urethral disruption and bladder neck incompetence is difficult and risks erosion. Urinary diversion with a Mitrofanoff catheterizable stoma may be a better option for these patients.
Area of Science:
- Urology
- Reconstructive Surgery
Background:
- Management of posterior urethral disruption with bladder neck incompetence is challenging.
- Treatment options include Mitrofanoff catheterizable stoma or urethral reconstruction with artificial urinary sphincter (AUS).
Purpose of the Study:
- To evaluate the efficacy and complications of delayed AUS placement for concurrent posterior urethral disruption and bladder neck incompetence.
Main Methods:
- Retrospective review of patients treated with end-to-end urethroplasty followed by delayed bladder neck AUS placement.
- Patient records from 1986 to 2006 were analyzed.
Main Results:
- Five patients with traumatic posterior urethral disruption and bladder neck incompetence underwent the procedure.
- All patients initially achieved continence, but 4 experienced erosion into the bladder neck and 1 into the bladder neck and rectum within 3 years.
- Technical challenges included significant pelvic fibrosis.
Conclusions:
- Delayed AUS placement for this complex injury is technically demanding and carries a high risk of delayed erosion.
- Urinary diversion with a Mitrofanoff catheterizable stoma should be strongly considered for these patients.
Purpose:
Management for posterior urethral disruption and concurrent bladder neck incompetence is controversial. Some groups recommend treatment with a Mitrofanoff catheterizable stoma, while others advocate urethral reconstruction with delayed placement of an artificial urinary sphincter. We report our experience with the latter strategy.
Materials And Methods:
We reviewed the records of all patients with the above injury who were treated with end-to-end urethroplasty followed by delayed bladder neck artificial urinary sphincter placement from 1986 to 2006.
Results:
Five patients had videourodynamic evidence of bladder neck incompetence coexisting with traumatic posterior urethral disruption. The etiology of bladder neck incompetence in all 5 patients was a known longitudinal tear through the bladder neck that occurred at the time of trauma. Each patient underwent end-to-end urethroplasty. Six to 12 months later the patients had persistent incontinence. Bladder function and urethral patency were documented by urodynamic, radiographic and endoscopic studies. A bladder neck artificial urinary sphincter was subsequently placed. Each operation was technically demanding due to fibrosis in the pelvis and around the bladder neck. All patients were initially continent but erosion of the artificial urinary sphincter into the bladder neck in 4, and the bladder neck and rectum in 1 occurred at a mean of 3 years (range 6 months to 8 years).
Conclusions:
Placement of a bladder neck artificial urinary sphincter for managing urinary incontinence due to concurrent posterior urethral disruption and bladder neck incompetence is difficult and it risks delayed erosion. In this patient population we would strongly consider urinary diversion with a Mitrofanoff catheterizable stoma.

Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:28
Microbiota of the Urogenital Tract
 01:20
Disorders of the Urinary System
Urinary tract infections (UTIs) are one of the most common urinary system disorders. They are caused by bacteria that enter the urethra and can spread to the bladder resulting in cystitis. Pyelonephritis is the result of a UTI that has ascended to the level of the...