Related Experiment Video
Updated: Jul 12, 2026

Arteriovenous Metabolomics to Measure In Vivo Metabolite Exchange in Brown Adipose Tissue
Published on: October 6, 2023
Burn size determines the inflammatory and hypermetabolic response
Marc G Jeschke1, Ronald P Mlcak, Celeste C Finnerty
1Shriners Hospitals for Children, 815 Market Street, Galveston, TX 77550, USA. majeschk@utmb.edu

Background:
Increased burn size leads to increased mortality of burned patients. Whether mortality is due to inflammation, hypermetabolism or other pathophysiologic contributing factors is not entirely determined. The purpose of the present study was to determine in a large prospective clinical trial whether different burn sizes are associated with differences in inflammation, body composition, protein synthesis, or organ function.
Methods:
Pediatric burned patients were divided into four burn size groups: <40% total body surface area (TBSA) burn, 40-59% TBSA burn, 60-79% TBSA burn, and >80% TBSA burn. Demographic and clinical data, hypermetabolism, the inflammatory response, body composition, the muscle protein net balance, serum and urine hormones and proteins, and cardiac function and changes in liver size were determined.
Results:
One hundred and eighty-nine pediatric patients of similar age and gender distribution were included in the study (<40% TBSA burn, n = 43; 40-59% TBSA burn, n = 79; 60-79% TBSA burn, n = 46; >80% TBSA burn, n = 21). Patients with larger burns had more operations, a greater incidence of infections and sepsis, and higher mortality rates compared with the other groups (P < 0.05). The percentage predicted resting energy expenditure was highest in the >80% TBSA group, followed by the 60-79% TBSA burn group (P < 0.05). Children with >80% burns lost the most body weight, lean body mass, muscle protein and bone mineral content (P < 0.05). The urine cortisol concentration was highest in the 80-99% and 60-79% TBSA burn groups, associated with significant myocardial depression and increased change in liver size (P < 0.05). The cytokine profile showed distinct differences in expression of IL-8, TNF, IL-6, IL-12p70, monocyte chemoattractant protein-1 and granulocyte-macrophage colony-stimulating factor (P < 0.05).
Conclusion:
Morbidity and mortality in burned patients is burn size dependent, starts at a 60% TBSA burn and is due to an increased hypermetabolic and inflammatory reaction, along with impaired cardiac function.
More Related Videos
 04:54
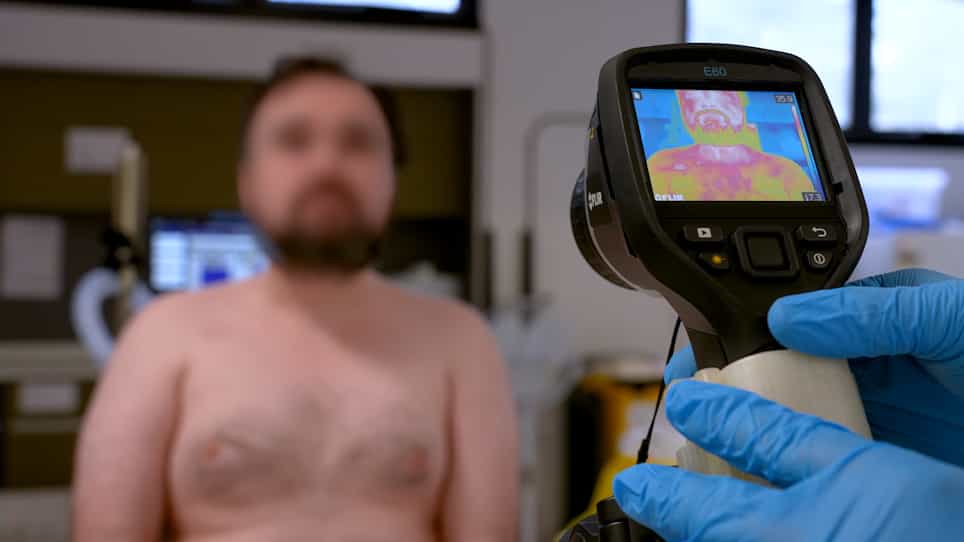
Using a Combination of Indirect Calorimetry, Infrared Thermography, and Blood Glucose Levels to Measure Brown Adipose Tissue Thermogenesis in Humans
Published on: June 2, 2023
 06:57
Determining Basal Energy Expenditure and the Capacity of Thermogenic Adipocytes to Expend Energy in Obese Mice
Published on: November 11, 2021
Related Concept Videos
 01:28
Inflammatory Response
Inflammation can be triggered by various stimuli, such as impact, abrasion, chemical irritation, infections, and extreme hot or cold temperatures. These can damage cells and connective tissue fibers,...
 01:19
Regulation of Metabolism
 01:30
Inflammatory Response I: Vascular and Cellular
 01:25
Metabolic Rate
The Basal Metabolic Rate (BMR) measures the energy expended at rest.
Several factors influence the...
 01:26
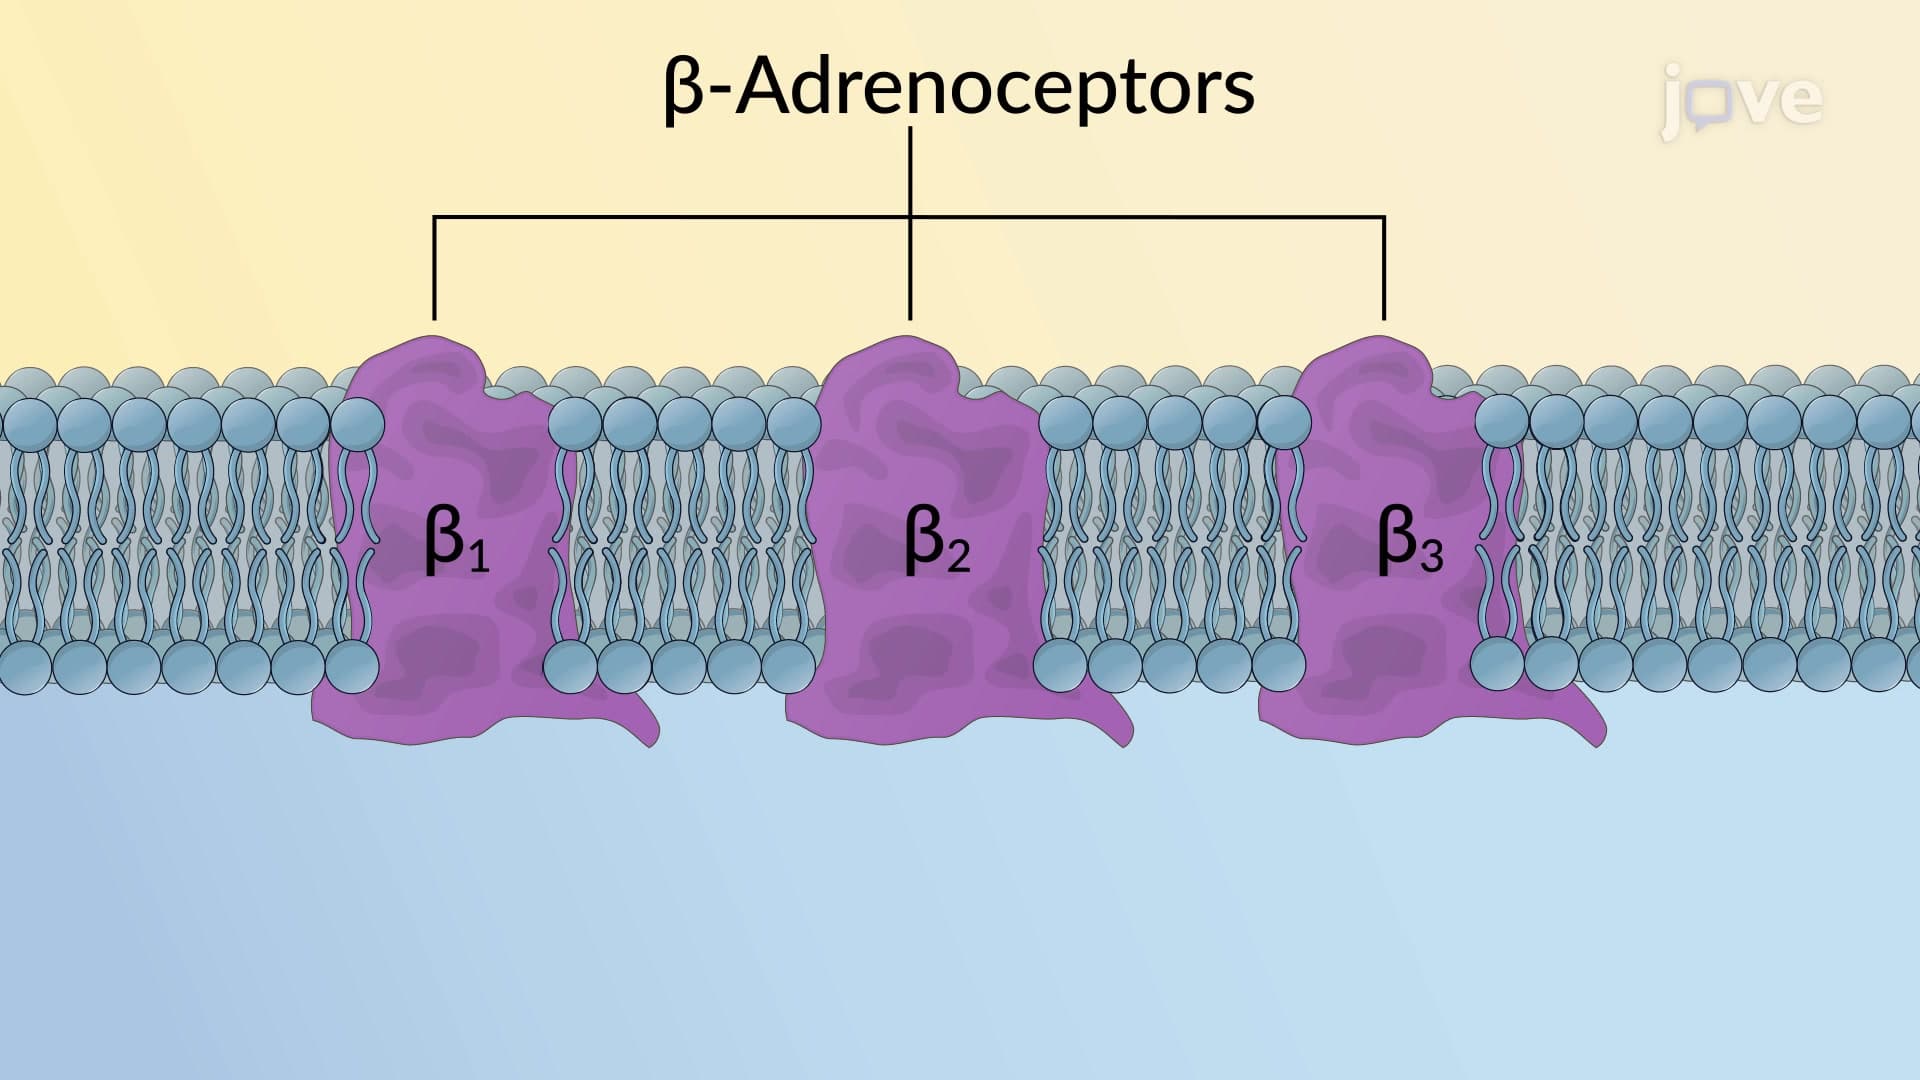
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:16
Sympathetic Activation