Related Experiment Video
Updated: Jul 12, 2026
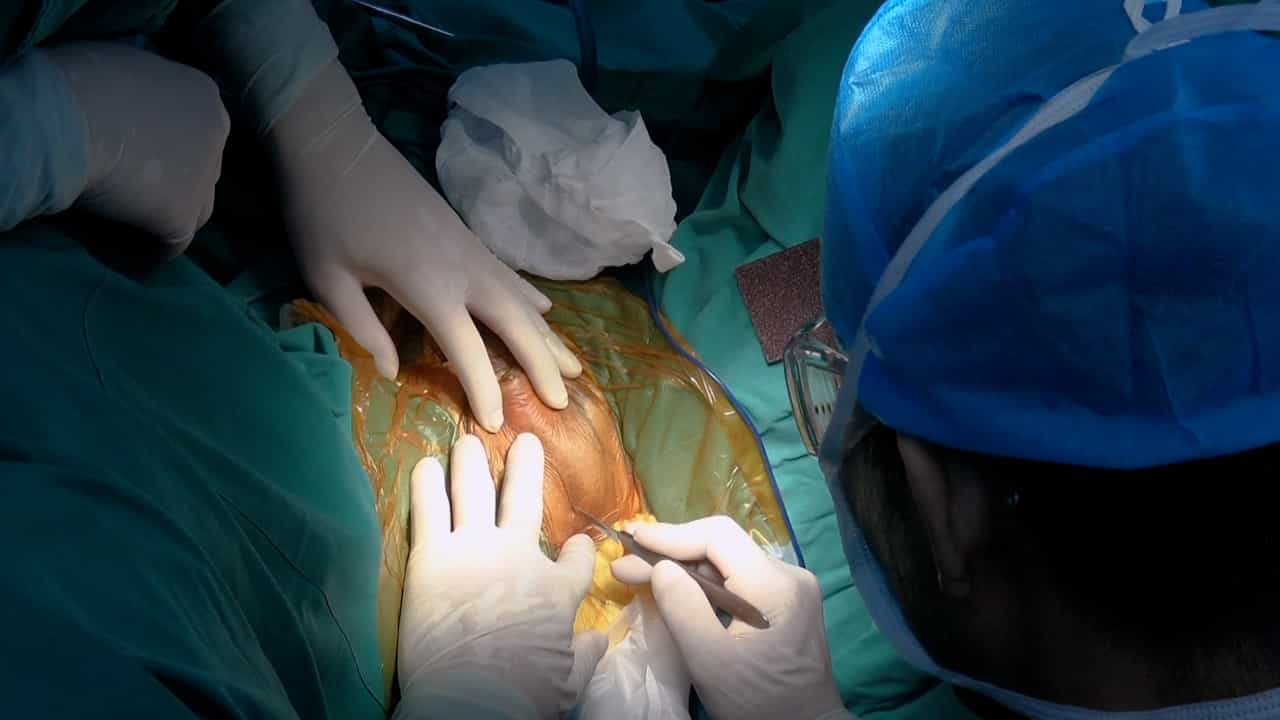

Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
[Cystocele and stress urinary incontinence associated with lower urinary tract obstruction]
Jesús Salinas1, Sara Prieto, José María Adot
1Servicio de Urología, Hospital Clínico San Carlos, Universidad Complutense, Madrid, España. salinascasado@yahoo.es

Objectives:
The association of stress urinary incontinence secondary to urethral hypermobility and lower urinary tract obstruction in the same patient with cystocele is rare, and even represents a contradiction. The objective of our work is to treat to define the characteristics that identify this entity, in comparison with isolated stress urinary incontinence or lower urinary tract obstruction in patients with cystocele.
Methods:
We performed a retrospective study in 1168 cases of cystocele in which urodynamic studies were performed. All patients underwent history and neurological and uro-gynecologycal physical examination. The urodynamic study included uroflowmetry, cystomanometry, voiding pressure/flow tests and voiding cystourethrograms. All data were collected in an Excel 2000 database and statistical analysis was performed with the SPSS software.
Results:
A- General data: 25 cases qualified for the study in group I (isolated stress urinary incontinence with urethral hypermobility); 24 cases in group II (lower urinary tract obstruction); and 14 cases in group III (astress urinary incontinence associated with lower urinary tract obstruction). The proportion of each group in the whole group of cystoceles corresponded to a 4/1/0.05 ratio respectively. Mean age was 58.4 years for group I, 68.2 for group II and 71.2 for group III. A Statistically significant lower age was demonstrated for group I (p < 0.0005). B- The symptom "sensation of vaginal lump" was less frequent in group I (32%). A significant difference was demonstrated (p = 0.02). C- Group I showed a lower increase of daily voiding frequency (32%), p = 0.02. D- Group I showed less night-time voiding frequency (1 episode)(p < 0.04). E- Urinary incontinence with cough was less frequent in group 1 (84%) (p = 0.0004). F- Group I had more bladder capacity (243.6 ml) (p < 0.05).G- Group I showed less urethral resistances (URA = 37.9 cm H2O) (p = 0.01). H- W80-W20 was higher in group I: 1.3 W/m2 (p < 0.05). I- The symptom "sensation of vaginal lump appeared more often in group II (70.8%) (p = 0.02). J- Radiological degree of cystocele was greater in group II1 (1.7) (p < 0.05). K- Detrusor hyperactivity was more frequent in group III (64.3%) (p = 0.00009). L- No significant differences were found between groups II-III when comparing type of obstruction.
Conclusions:
The group of isolated stress urinary incontinence (group I) is characterized by a younger age, less frequency of sensation of vaginal lump, less daily frequency and nocturia, and urodynamic data of greater bladder capacity, lower urethral resistance and normal detrusor contractility. The group of isolated lower urinary tract obstruction (group II) could be characterized by a more frequent sensation of vaginal lump and increase of the radiological cystocele. The group of stress urinary incontinence associated with lower urinary tract obstruction had a higher percentage of cases of detrusor hyperactivity. All these data might enable a proper identification of different risk elements in the groups.
Related Concept Videos
 01:20
Disorders of the Urinary System
Urinary tract infections (UTIs) are one of the most common urinary system disorders. They are caused by bacteria that enter the urethra and can spread to the bladder resulting in cystitis. Pyelonephritis is the result of a UTI that has ascended to the level of the...
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:25
Urinary Tract Calculi VI: Surgical Management