Related Experiment Video
Updated: Jul 12, 2026


Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Hyperammonemia in distal renal tubular acidosis: is it more common than we think?
1Department of Pediatrics, Pediatric Nephrology, University of Florence, Italy. ivana.pela@unifi.it

Abstract:
The hyperammonemia in distal renal tubular acidosis, previously only described in two cases, is considered an unusual occurrence. After the report published in 2005, we observed plasma ammonia levels above normal range during metabolic decompensation in two other consecutive pediatric patients suffering from distal renal tubular acidosis. The ammonia plasma levels returned to normal range after treatment with sodium bicarbonate and potassium salt. In distal renal tubular acidosis, hyperammonemia is probably the result of an imbalance between the increased ammonia synthesis, in response to metabolic acidosis, and the impaired ammonia excretion, typical of distal renal tubular acidosis. According to this physiopathological mechanism, our observation shows that hyperammonemia is not an uncommon finding in distal renal tubular acidosis, and should be included among differential diagnosis of hyperammonemia in infants and children.
Related Concept Videos
 01:29
Renal Regulation of Acid-Base Balance
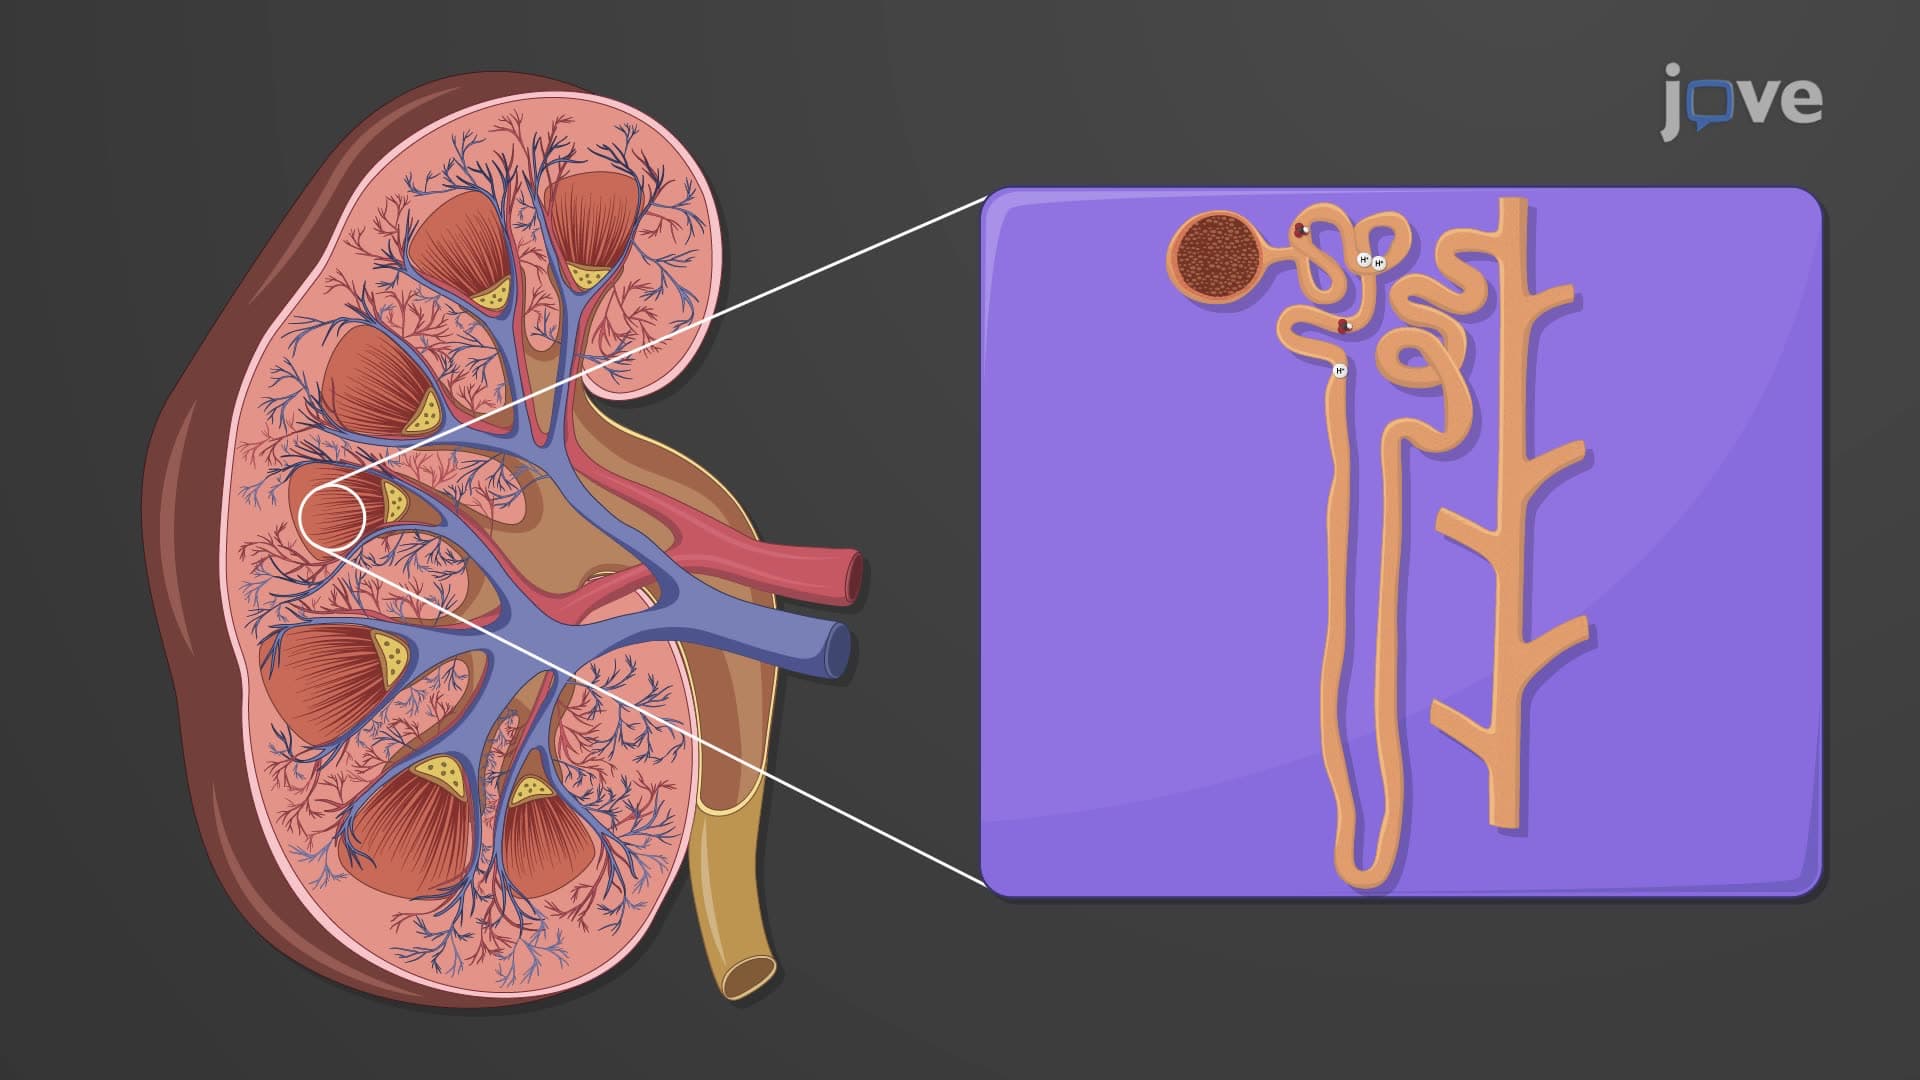
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:25
Diabetic Ketoacidosis l: Introduction
 01:29
Acute Kidney Injury III: Clinical Manifestations