Immune intervention at diagnosis--should we treat children to preserve beta-cell function?
Related Experiment Video
Updated: Jul 12, 2026
Methods to Assess Beta Cell Death Mediated by Cytotoxic T Lymphocytes
Published on: June 16, 2011
1Department of Molecular and Clinical Science, Division of Pediatrics and Diabetes Research Centre, Faculty of Health Sciences, Linköping, Sweden. johnny.ludvigsson@lio.se

Type 1 diabetes (T1D) is characterized by loss of beta-cell function. If beta-cell function can be preserved, it will lead to improved metabolic balance with improved quality of life and fewer acute and late complications, and if residual insulin secretion improves well enough, then that could lead to complete remission and even cure of the disease. Several efforts to save residual beta-cell function have been made for more than three decades without success. Proof of principle has been possible, and it seems clear that immune suppression or immune modulation, in fact, can stop the destructive process and thereby preserve beta-cell function. However, the effect seen in adult patients with T1D have been minimal or absent in diabetic children who seem to have another or at least more aggressive disease process. Furthermore, the immune interventions have had too serious and common adverse events in comparison to the scarce-positive effect. Recent more specific immune modulation with anti-CD3 monoclonal antibodies seems more encouraging with at least postponement of the C-peptide decline, but unfortunately still with common and quite threatening adverse effects. Even more promising are the autoantigen therapies, of which glutamic acid decarboxylase (GAD) vaccination has shown good results with impressive preservation of residual insulin secretion in 10- to 18-year-old type 1 diabetic patients with recent onset. In patients with short diabetes duration at intervention the effect was remarkable. Furthermore, these effects were achieved with no adverse events. Future studies will show whether the good effect seen so far can be confirmed. If so there is hope that GAD vaccination will cause remission and even cure and prevention of T1D will then no longer be just a dream.
Type 1 diabetes (T1D) is characterized by loss of beta-cell function. If beta-cell function can be preserved, it will lead to improved metabolic balance with improved quality of life and fewer acute and late complications, and if residual insulin secretion improves well enough, then that could lead to complete remission and even cure of the disease. Several efforts to save residual beta-cell function have been made for more than three decades without success. Proof of principle has been possible, and it seems clear that immune suppression or immune modulation, in fact, can stop the destructive process and thereby preserve beta-cell function. However, the effect seen in adult patients with T1D have been minimal or absent in diabetic children who seem to have another or at least more aggressive disease process. Furthermore, the immune interventions have had too serious and common adverse events in comparison to the scarce-positive effect. Recent more specific immune modulation with anti-CD3 monoclonal antibodies seems more encouraging with at least postponement of the C-peptide decline, but unfortunately still with common and quite threatening adverse effects. Even more promising are the autoantigen therapies, of which glutamic acid decarboxylase (GAD) vaccination has shown good results with impressive preservation of residual insulin secretion in 10- to 18-year-old type 1 diabetic patients with recent onset. In patients with short diabetes duration at intervention the effect was remarkable. Furthermore, these effects were achieved with no adverse events. Future studies will show whether the good effect seen so far can be confirmed. If so there is hope that GAD vaccination will cause remission and even cure and prevention of T1D will then no longer be just a dream.

Related Concept Videos
 01:12
Type I Diabetes I: Introduction
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
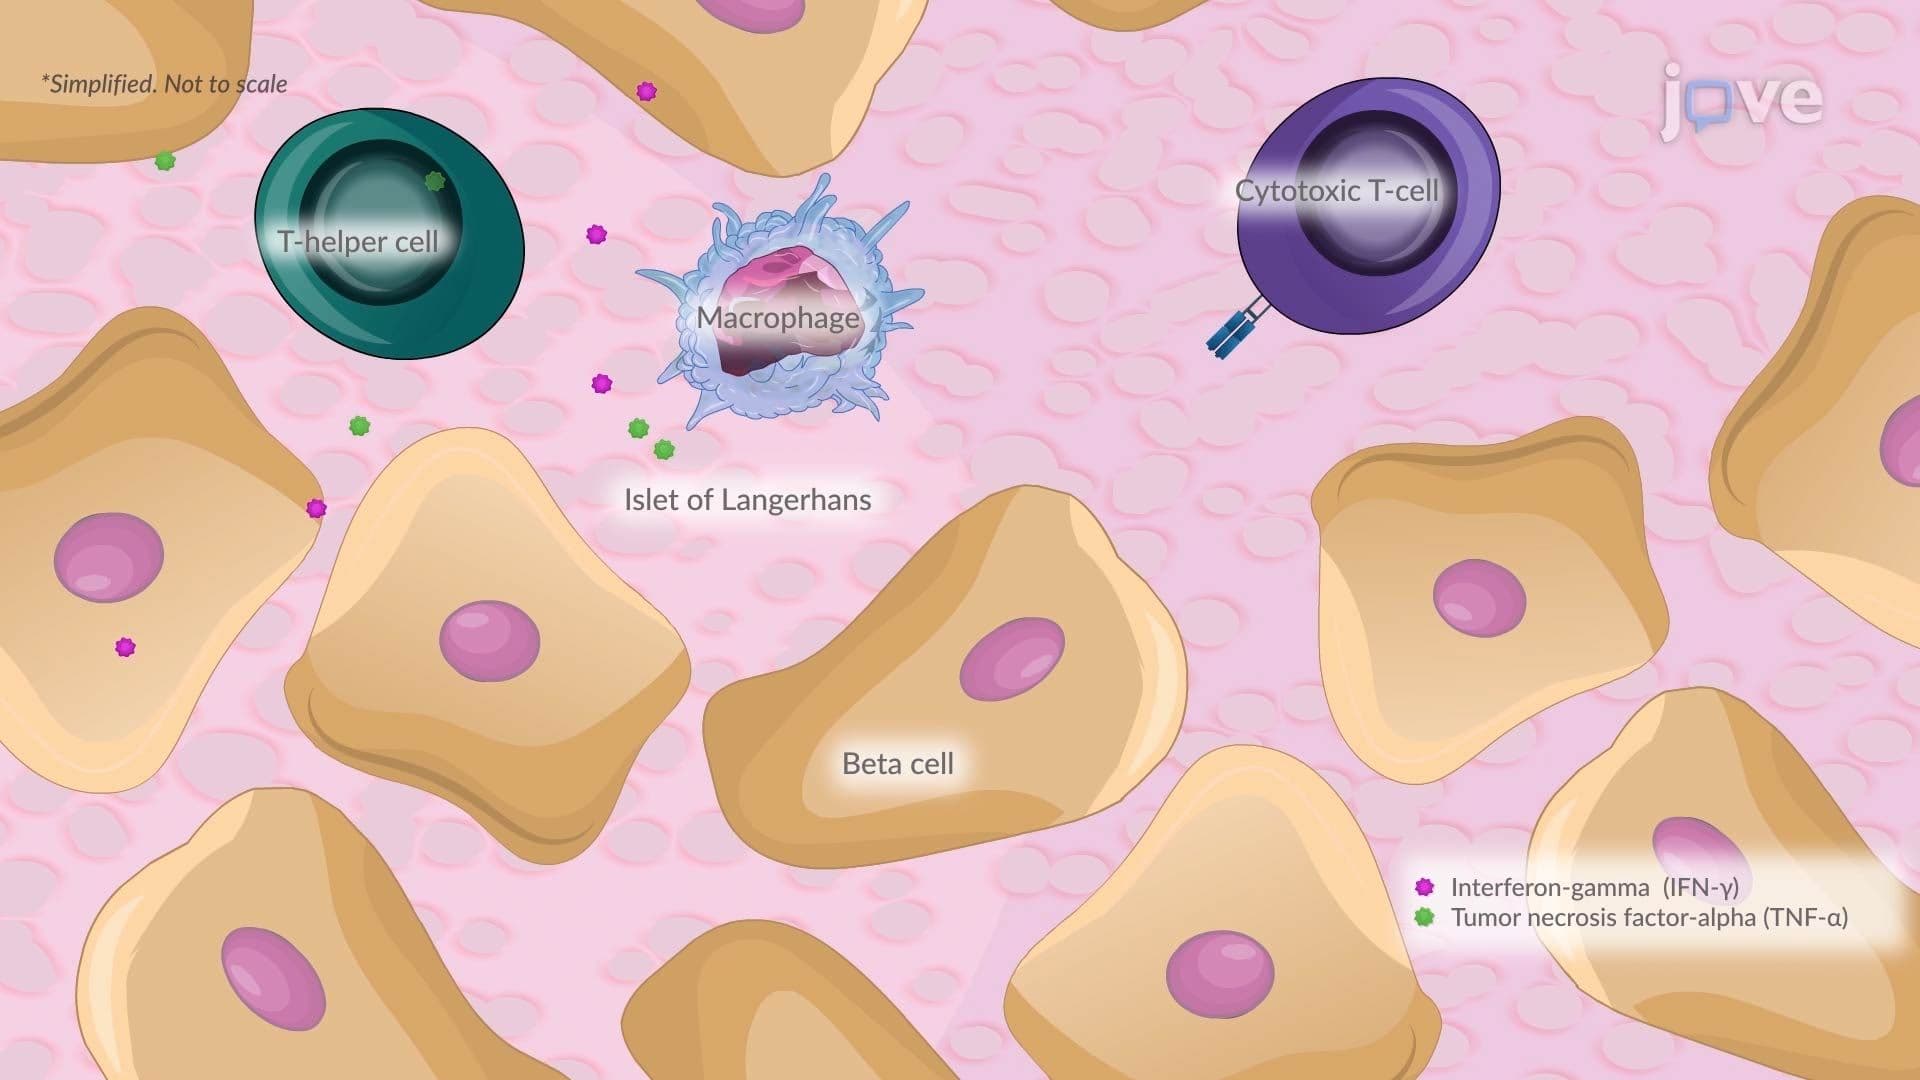 01:26
Type I Diabetes II: Pathophysiology
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...